Psoriasis Reset
 Facebook ad: “Real Reason Your Plaques Keep Spreading”
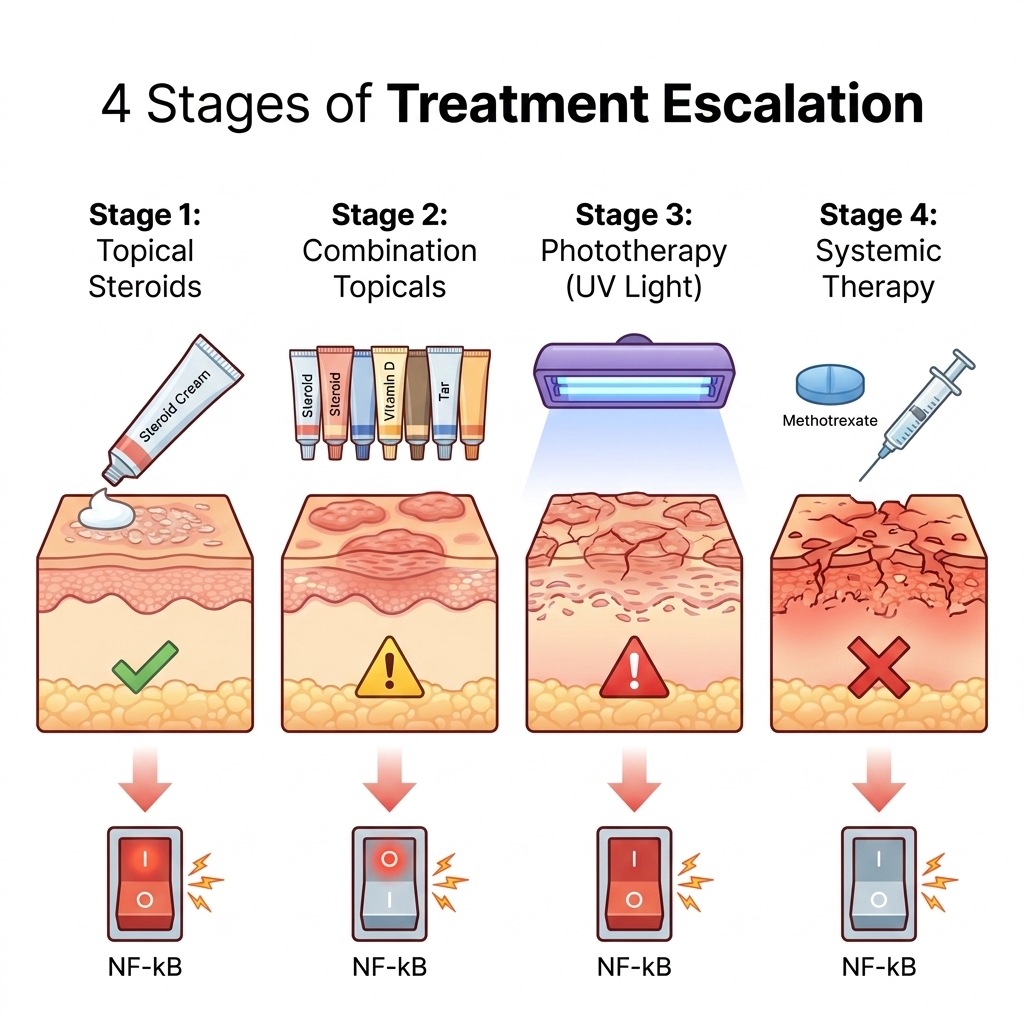
Ran for 17 days, from September 19 to October 6, 2026, the last day Crush saw it.
Run by Psoriasis Reset on Facebook. Crush is not the advertiser and does not verify its claims. See this ad in Meta's Ad Library(opens in a new tab)
Make your own version of this ad
Crush makes it, launches it in your own Meta ad account, scales the winners and pauses the losers.
About this ad
- Meta Ad Library ID
- 1023872747375028
- Platforms
- Facebook, Instagram, Audience Network and Threads
- Relaunches
- 0
- Niche
- Fashion & Apparel
Ad text
Psoriasis has four stages. The first three are addressable without immune suppression. Most dermatologists won't tell you that — because they're only trained to manage stage four. I've been an immunodermatologist for 25 years. The first 20, I practiced in a research hospital that studied NF-kB inflammatory pathways. I moved into private dermatology practice two years ago. And in my first three months, I saw something I couldn't stop thinking about. Women in their 50s and 60s sitting in my chair. Thick cracking plaques. Barrier destroyed. Skin thinned from years of steroid cream. Every one of them said the same thing. "My dermatologist has been managing it for years." In immunology, we don't manage the surface of psoriasis. We address the switch. Because by the time plaques are severe enough to "manage" with escalating prescriptions, something has already been failing structurally from the bloodstream for years. Here's what no one has told you about where psoriasis actually leads. Your skin barrier is made of ceramides and filaggrin. The structural proteins that keep skin smooth, flexible, and intact. They're the scaffolding — the architecture that holds everything together. When an inflammatory switch called NF-kB locks into the permanent ON position in your bloodstream, it sends IL-17 and TNF-alpha to every skin site. Those signals force skin cells to mature in 3 to 5 days instead of 30. The immature cells pile up as thick brittle plaques. And the same signal destroys the ceramide and filaggrin barrier underneath. That is stage one. The plaques appear first because the immature cells pile up visibly. The barrier collapse takes longer to show. But it is already happening. This is the moment most dermatologists prescribe steroid cream. I understand why. The plaques are visible. The cream smooths them. The patient leaves feeling like something was done. But steroid cream suppresses the local immune response at each plaque. It smooths what's already built up. It does not touch the NF-kB switch firing from the bloodstream. It does not rebuild the barrier. And every application thins the collagen further. Depletes the remaining ceramides. Builds tolerance — tachyphylaxis — so each rotation works for a shorter window. The switch is still firing. The barrier is still collapsing. The cream is thinning what's left — in the surrounding tissue, at adjacent sites, in the structural foundation beneath. I have seen beautiful surface results followed 6 weeks later by a rebound flare worse than what started the rotation. Because nothing changed structurally. The cream was smoothing the surface of a building whose framework was being demolished from inside. Stage two is what happens underneath while the surface looks managed. The NF-kB switch fires all night. The scales build while you sleep. The barrier collapses further each night. By morning your pillow is covered and your elbows have cracked. The cream you apply in the morning starts the thinning cycle again. Your chart says "well-managed on current protocol." Your pillow tells a different story every morning. Stage three: spreading. New plaques appear in places you've never had them. Scalp. Knuckles. Behind the ears. Jawline. The NF-kB switch doesn't fire at one site — it fires systemically from the bloodstream to every skin site simultaneously. The cream suppresses one plaque. The switch opens another. The barrier is now too depleted to contain the spreading. Black gaps appear between what used to be clear skin — patches opening on your forearms, your shins, your face. This isn't cosmetic. It's your skin losing its structural foundation. Stage four: the dermatologist says the word you've been dreading. Methotrexate. Or biologics. The steroid rotations have failed. The barrier is too depleted for topical recovery. I have had more of these conversations than I should have. With women who did everything right. Who never missed an application. Who had their creams rotated correctly. Who still, over time, watched their skin deteriorate beyond what cream could reach. Because the cream addressed the symptom. The NF-kB switch kept advancing. Silently, systemically — until the damage wasn't patchable anymore. When the barrier is gone, you face a choice between Methotrexate — with liver monitoring, blood draws, fatigue, and immune suppression — or biologic injections at $40,000 to $70,000 a year. For the rest of your life. I am not describing a worst-case scenario. I am describing what I watch happen, step by step, in patients who were told for years that their psoriasis was "well-managed." Your psoriasis is not a compliance problem. It is an NF-kB activation that starts in the bloodstream and progresses to the barrier underneath. No amount of cream addresses the switch. A steroid rotation smooths the surface. Neither stops the NF-kB signal. Think of it this way. You can smooth a building perfectly — every plaque on the surface suppressed, every wall patched, every visible crack covered. But if the steel framework inside is being dissolved by an inflammatory signal running from the foundation, the building still falls. Surface management doesn't fix the framework. Your skin works the same way. Steroid cream suppresses each plaque locally. That's what it's designed to do. It does not switch off NF-kB. It does not rebuild ceramides. Your skin isn't breaking down from poor compliance — it's breaking down because the NF-kB switch firing from the bloodstream is destroying the structural barrier from the inside while the cream thins it from the outside. The fix isn't stronger cream. It's switching off the signal and rebuilding the barrier — delivered systemically to where the destruction is happening. The immunology literature on NF-kB constitutive activation in psoriasis confirms that the switch — not compliance — drives plaque formation, barrier collapse, and steroid resistance across thousands of patients. In immunology, we address this with two specific compounds delivered systemically. Carvacrol from wild Mediterranean oregano oil — standardized to 70%+ concentration — travels through the bloodstream and inhibits the NF-kB transcription factor at the source. Thymoquinone from cold-pressed black seed oil signals the body to produce ceramides and filaggrin — rebuilding the barrier from the inside. Both delivered in a lipid softgel that survives stomach acid and reaches the bloodstream where NF-kB operates. Your compliance doesn't determine this outcome. Your NF-kB switch does. And whether the barrier gets the compounds it needs to rebuild. I want to tell you about one patient. She was 57. Had been on steroid rotations since she was 48. Nine years. Plaques spreading to scalp, knuckles, jawline. Her previous dermatologist had recommended starting Methotrexate. She came to me for a second opinion. Her compliance was excellent. The progression was real. I recommended 12 weeks of systemic NF-kB inhibition and barrier support before making any Methotrexate decisions. She was skeptical. Nine years of perfect compliance hadn't stopped anything. She didn't believe something taken as a softgel could change what nine years of cream hadn't. I explained it simply. Steroid cream suppresses each plaque on the surface. It does not switch off NF-kB firing from the bloodstream. Your skin isn't breaking down from non-compliance — it's breaking down because the switch is producing plaques faster than the cream can suppress them, and the cream is destroying the barrier faster than your body can rebuild it. You can smooth a building perfectly. If the framework is being dissolved from the inside, the building still falls. She agreed to try. Week 2: pillow cleaner in the morning. Itch quieter. Week 4: elbows bending without cracking. Full range, no blood, for the first time in years. Week 8: dark sweater wearable without lint-rolling. Knuckle fissures closed. Scalp clear. Week 12: I measured each plaque site. Then measured again. Plaque thickness — reduced by more than half across every site. NF-kB inflammatory markers — approaching baseline. Ceramide levels — climbing toward the normal range for the first time since diagnosis. She didn't need the Methotrexate. In immunology, this is where we start. Not with immune suppression. With the switch. Orgatics Oregano & Black Seed Oil Softgels. Wild Mediterranean oregano oil standardized to 70%+ carvacrol. Cold-pressed black seed oil with thymoquinone. Lipid softgel delivery. 6,000mg equivalent per serving. Third-party tested. 👉 tryorgatics.com/pages/adv-pso 90-day money-back guarantee. I have no financial relationship with this company. I recommend it because the mechanism is sound, the research is published, and I've seen what happens when patients finally address the right problem. Your skin is failing on the surface because the NF-kB switch is firing from the bloodstream. Your barrier is next. You just can't see it yet.
Where the ad sends people
tryorgatics.com
Real Reason Your Plaques Keep Spreading 👆
Orgatics
Learn more: tryorgatics.com(opens in a new tab)