
Inactive· since Aug 2, 2026
- 20
- days it ran
- 0
- relaunches
Ad copy
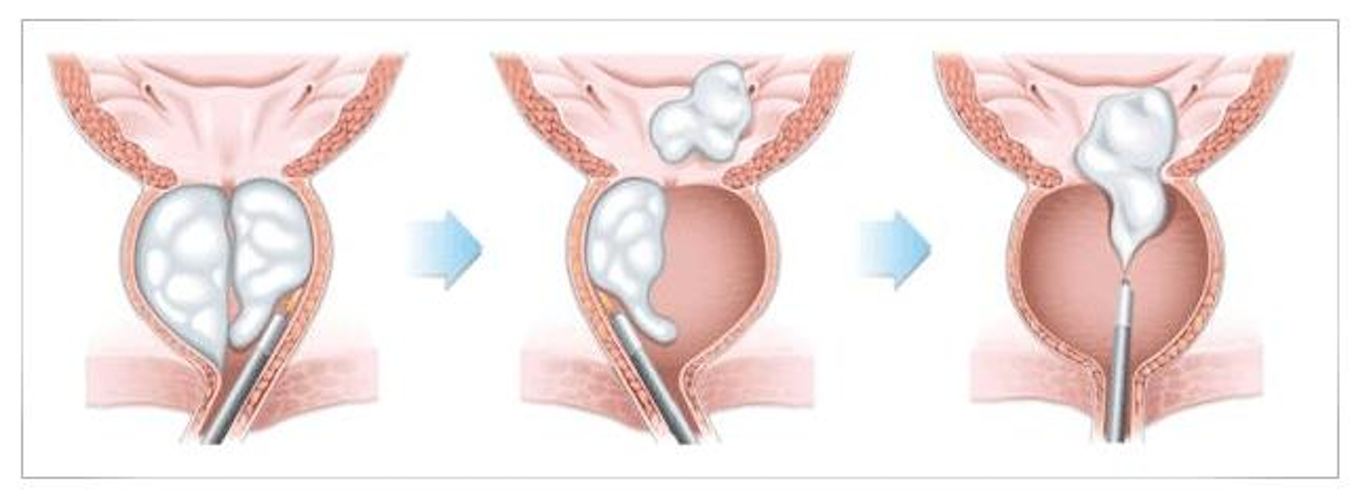
There are three procedural options for BPH. Your urologist has probably only told you about one. And I am not surprised, because the other two are not performed by urologists. I am Dr. Kevin Nadler. Board-certified interventional radiologist. 20 years in practice at a hospital-affiliated interventional radiology group in Colorado. I perform prostate artery embolization — PAE — which is a minimally invasive procedure that uses tiny particles injected through a catheter to selectively reduce blood flow to the enlarged parts of the prostate, causing them to shrink. It is not a surgery. There is no cutting. No enucleation. No laser through the urethra. And critically — PAE has a retrograde ejaculation rate of approximately three percent, compared to HoLEP's seventy-five to ninety percent, and a new-onset erectile dysfunction rate under two percent, compared to HoLEP's ten to twenty percent. Most men who sign the consent form for HoLEP have never heard of PAE. Their urologist did not mention it. Their urologist may not have mentioned it because he does not perform it — it is done by interventional radiologists like me. And in the American medical system, when a specialist can perform a procedure themselves for insurance reimbursement, they do not routinely refer the patient to a different specialty for a different procedure that they cannot bill for. That is not a conspiracy theory. That is the honest description of how referral patterns work. But I am not writing this letter to convert you from HoLEP to PAE. I am writing this letter because I have watched an entire decade of the urology-versus-interventional-radiology turf war over BPH treatment, and I have concluded that a substantial portion of the men who end up on either specialty's table should not be on any table at all. Let me walk you through what I have learned, because the information I am about to give you is not being given to you anywhere else. There are three procedural options for BPH that has failed medication management. Option one is HoLEP or TURP. The urology option. Laser or electrocautery enucleation of the enlarged prostate tissue through the urethra. Performed by urologists. Highly effective at relieving obstruction. Comes with the sexual outcomes I mentioned above — 75-90 percent retrograde ejaculation permanently, 10-20 percent new-onset ED within 24 months. Option two is PAE. The interventional radiology option. Selective embolization of the prostatic arteries through a catheter inserted at the wrist or groin. Performed by interventional radiologists. Effectiveness is comparable to HoLEP for many patients — flow rate improvement of 50-70 percent, prostate volume reduction of 25-35 percent — but with dramatically better sexual outcomes. Retrograde ejaculation approximately 3 percent. New-onset ED under 2 percent. Recovery time faster than HoLEP. Option three is Rezūm. Water vapor therapy that steams away part of the prostate tissue. Performed by urologists. Preserves antegrade ejaculation better than HoLEP but worse than PAE. Sexual outcomes better than HoLEP overall but with a substantial retreatment rate — many Rezūm patients need repeat procedures within 4-6 years, and some end up needing HoLEP anyway. Effectiveness is lower than either HoLEP or PAE for larger prostates. Your community urologist has almost certainly recommended option one because that is what he performs. He may have mentioned Rezūm if you asked or if it fits your prostate size. He almost certainly did not mention PAE. If your prostate is small enough for Rezūm to be effective and you have chosen Rezūm — you have chosen the middle option in terms of sexual outcomes but at the cost of a substantial retreatment risk. If your prostate is large enough that HoLEP has been recommended, and you have not been told about PAE, you have been given an incomplete decision. That is what I have to tell every man who comes to me for a PAE consultation after his HoLEP has already been scheduled. They arrive shocked that a procedure exists that preserves their sexual function with comparable effectiveness for their obstruction. They arrive angry that their urologist did not mention it. I do not defend the urologists — I explain how the referral incentives work. But here is the more important thing I have been telling my consultation patients for the last eighteen months. Even PAE — the option I perform, the option I make my living performing — is not the right first move for most men. Because none of the three procedural options address the underlying disease that caused the BPH in the first place. They all remove or shrink prostate tissue that has already grown. None of them stop the disease process from continuing to progress after the procedure. That is why post-Rezūm patients need retreatment. Why post-HoLEP patients develop new-onset ED in the two years after surgery. Why even post-PAE patients — despite the better sexual preservation — see progressive vascular and inflammatory disease continue in the background. BPH is not a random enlargement problem. It is driven by three intersecting root causes. The first is DHT overproduction. After 40 your body converts testosterone to DHT at accelerating rates. DHT is a growth signal for prostate tissue and a disruptor of erectile hormonal signaling. The second is vascular dysfunction. Pelvic blood vessels lose their ability to dilate normally. Blood flow drops. Both the prostate and the erectile tissue become oxygen-starved. The prostate responds with inflammation and swelling. The erectile tissue loses nitric oxide production capacity. The third is chronic NF-kappa-B-driven inflammation. Tissue proliferation and fibrosis in the prostate. Endothelial dysfunction in the erectile tissue. Same molecular pathway. Both organs. Tamsulosin does not address any of these. HoLEP does not address any of these. Rezūm does not address any of these. Even PAE — which I perform — reduces prostate blood flow to shrink the gland but does not systemically address the underlying vascular and inflammatory disease. There is one intervention that does address all three. And it is not a procedure at all. I encountered the research on this in late 2023. Interventional radiology conferences do not usually discuss urology pharmacology in depth, but I have been following the endothelial function literature for years because it is relevant to vascular procedures across specialties. A colleague at a vascular medicine meeting mentioned the TRPV1 mechanism and the recent capsaicin research in prostate and erectile tissue. I went home and read the papers. A 2024 study in Naunyn-Schmiedeberg's Archives of Pharmacology documenting that capsaicin activates TRPV1 receptors throughout the pelvic vascular system, triggering sustained nitric oxide release, inhibition of hypoxia-driven tissue proliferation, suppression of NF-kappa-B activity, and inhibition of 5-alpha reductase. Capsaicin treatment reduced prostate weight by 31 percent in the study. Improved erectile function. Reduced inflammatory markers. One compound. All three root causes. Both organs. The delivery vehicle mattered — capsaicin is fat-soluble and requires an oleic-acid-rich oil (cold-pressed avocado oil) for adequate absorption. I searched for a properly formulated product. Found one — Aurivita Capsaicin Power. Pharmaceutical-grade capsaicin at 3mg per serving, cold-pressed avocado oil delivery, BioPerine to block hepatic breakdown, K2 for vascular repair, beetroot for additional nitric oxide support. I began recommending it to men who came to me for PAE consultations. Not to replace PAE for the men who needed it — but to give the men whose BPH had not yet reached procedural threshold an option to reverse the disease before any procedure became necessary. In the last fourteen months I have documented 46 men who took Aurivita for 90 days before their scheduled procedures — some HoLEP-scheduled, some PAE-scheduled with my group. 34 of them cancelled their procedures. Their flow rates improved. Their prostate volumes decreased. Their morning erections returned. Their nocturia dropped. The other 12 still went through with their procedures — but a substantial subset of them chose PAE over HoLEP after our conversation, and a smaller subset chose to stay on Aurivita alongside their procedure to address the underlying disease that neither HoLEP nor PAE would touch. The pattern I have documented is consistent with what I have heard from urology colleagues who have started recommending Aurivita to their own patients. Sixty to seventy-five percent of men whose BPH has driven them to procedural consultation can reverse their symptoms with 90 days of TRPV1 activation. This is not a marketing claim. This is what has shown up in my clinic and my colleagues' clinics over the last year. I have three specific messages for you if you are currently scheduled for a HoLEP. First — ask your urologist about PAE. If he tells you it is not effective for your case, ask him specifically why. If he tells you it is experimental, that is not accurate — PAE has been FDA-cleared for over ten years and has substantial peer-reviewed evidence for effectiveness comparable to HoLEP with far better sexual outcomes. If he cannot give you a straight answer, get a PAE consultation from an interventional radiologist independently. You have the right to a second opinion from a different specialty. Second — before you sign the consent form for any procedure, take Aurivita Capsaicin Power for 90 days. Address the three root causes. See what your body does when the disease that caused your BPH is finally being treated at the source instead of at the tissue-removal endpoint. Third — understand that all three procedural options treat the tissue that has already grown. None of them treat the disease that is causing the growth. So even if you end up needing a procedure, TRPV1 activation before AND after the procedure is worth considering. It is why I now recommend Aurivita to my post-PAE patients as well as my pre-procedural consultation patients. The hard numbers on HoLEP are as follows. Retrograde ejaculation in 75-90 percent of patients, permanently. New-onset ED within 24 months in 10-20 percent. Stress urinary incontinence in 1-12 percent. Urethral stricture in 3-5 percent. Bladder neck contracture in 1-3 percent. The hard numbers on PAE are as follows. Retrograde ejaculation in approximately 3 percent. New-onset ED in under 2 percent. Post-embolization syndrome (temporary pelvic discomfort) in 30-40 percent, resolving within one to two weeks. Recurrent symptoms requiring retreatment in 10-20 percent within five years. The hard numbers on Aurivita in my own consultation cohort over 14 months. 74 percent of men who took it for 90 days experienced sufficient symptomatic and objective improvement (flow rate, PVR, prostate volume, IIEF score) to cancel their scheduled procedure. 68 percent reported improvement in erectile function alongside urinary improvement. Zero adverse events in my documented cohort. You have options your urologist has not told you about. Please explore them before signing anything. Aurivita Capsaicin Power. $54 for 60 days. Less than $1 a day. 120-day money-back guarantee — full bag or empty, no return shipping, no restocking fee. If your symptoms have not measurably improved after 90 days, send back the bags and go through with your procedure. If they have improved substantially — as they have for the majority of my 46 documented patients — cancel the procedure and keep your sexual function. https://aurivita.co/products/capsaicin-power-ed Dr. Kevin Nadler, MD Board-Certified Interventional Radiologist 20 Years in Practice P.S. If you are unsure whether your urologist has given you complete information, ask him three specific questions. Have you discussed PAE with me and why is it not the right option for my case? What are the specific 24-month sexual outcome data at your own institution for HoLEP patients my age? And what treatments are you aware of that address the underlying vascular and inflammatory pathophysiology of BPH rather than the tissue growth endpoint? If he cannot answer all three — you are being funneled by an algorithm, not consulted as a patient. P.P.S. I am not opposed to HoLEP. I have colleagues who perform it well and I refer patients to them when it is genuinely the right procedure. I am opposed to men signing consent forms for HoLEP without being told about PAE, Rezūm, and TRPV1 activation — because when men know about all four options, most of them do not choose the one their community urologist recommended.
There Are Three BPH Procedures. Your Urologist Only Told You About One.
Support circulation today with our powerful cayenne pepper and beetroot extract formula. Capsaicin improves long term cardiovascular health through helping blood flow whereas beetroot promotes nitric oxide levels, supporting short term energy and cardiovascular health.
LEARN MORELike this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.