
Active· since Aug 5, 2026
- 40
- days running
- 0
- relaunches
Ad copy
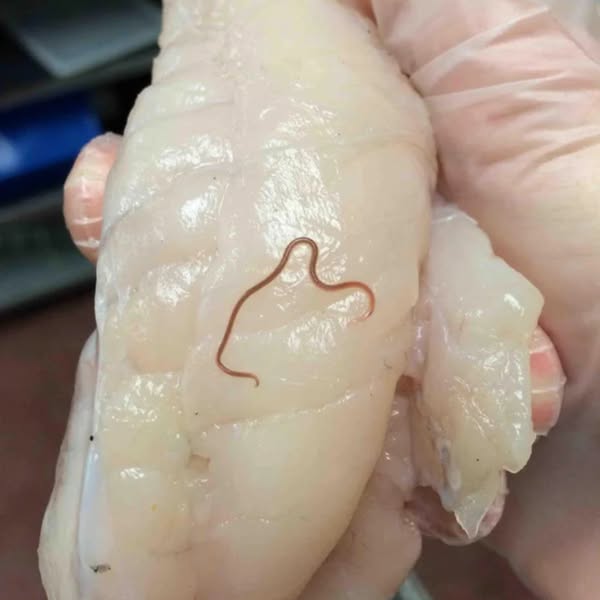
I saw a statistic that made me sick. According to the CDC, more than 60 million people in the United States are chronically infected with at least one parasite. The CDC also notes these infections "often go unnoticed, with few symptoms." Not a few thousand people. Not a million. Sixty million. Chronically infected. Right now. I didn't believe it when I read it. I've been an epidemiologist for 15 years — my entire career is tracking infectious disease patterns across US populations — and not once had anyone in my field treated this number like it mattered. But here's the truth. Your doctor sees your bloating and calls it IBS. Your sleep specialist sees your 3am wake-ups and calls it stress. Your primary care runs a blood panel, says everything looks normal, and writes a prescription. The problem sits underneath all of it — and nobody is trained to look there. That's why most of us never heard this statistic. That's why I almost missed it too. Sitting in a CDC surveillance report I'd read a dozen times. Buried in a paragraph nobody highlights. Sixty million chronic infections, dismissed in a single phrase. "Often go unnoticed, with few symptoms." Few symptoms. I need you to understand what that phrase means in my field. Because it doesn't mean what you think it means. — In epidemiology, "few symptoms" is a classification. It means the infection doesn't produce acute, immediately life-threatening outcomes in immunocompetent adults. It means people don't show up in emergency rooms. It means the infection doesn't generate the kind of dramatic, obvious illness that triggers a public health response. That's all it means. It doesn't mean nothing is happening. It doesn't mean the infected person feels fine. It doesn't mean the parasite is sitting quietly inside 60 million people doing absolutely nothing. It means nobody looked closely enough to connect the damage to the cause. I know this because connecting damage to cause is literally my job. And when I finally did it — when I pulled the thread on what "few symptoms" actually looks like across a population of 60 million — I found something that should have triggered a national public health emergency decades ago. Instead it triggered the end of my funding. — Let me back up. I work — worked — at a university research center focused on chronic disease epidemiology. My team analyzed large-scale health data. Insurance claims. Hospital records. Prescription databases. Diagnostic codes. We looked for patterns in populations of millions. Most of my career was spent on the diseases everyone cares about. Cardiovascular. Metabolic. Autoimmune. The big ones. The funded ones. But 18 months ago I was reviewing parasitic infection data for a graduate student's thesis. Routine. Low priority. The kind of work you do on a Friday afternoon. That's when the 60 million number caught me differently. Not because it was new. Because of what I'd been looking at all morning. I'd spent the first half of that day reviewing nationwide diagnostic trends for irritable bowel syndrome. IBS diagnoses in the US have increased 34% over the past 15 years. Chronic fatigue diagnoses are up even higher. Sleep disorder diagnoses have nearly doubled. Brain fog and cognitive complaints are now one of the fastest-growing categories in primary care documentation. Tens of millions of Americans. Bloated. Exhausted. Unable to sleep through the night. Unable to think clearly. Gaining weight despite doing everything their doctors tell them. Being diagnosed with conditions that are really just descriptions of symptoms repackaged as explanations. IBS isn't a disease. It's a billing code. It means "your gut doesn't work and we don't know why." Chronic fatigue syndrome means "you're exhausted and we don't know why." These aren't diagnoses. They're admissions of ignorance dressed up in medical terminology. And I'd been staring at those numbers all morning when I flipped to the parasitology data and saw 60 million chronic infections with "few symptoms." The overlap hit me like a truck. — I did what any epidemiologist would do. I started cross-referencing. Pulled the symptom profiles associated with chronic Toxoplasma infection from every study published in the last 20 years. Cognitive impairment. Fatigue. Mood disruption. Sleep disturbance. Altered appetite patterns. Inflammatory markers. Then I pulled the symptom profiles from the IBS diagnostic criteria. The chronic fatigue criteria. The sleep disorder criteria. The "brain fog" complaints filling primary care charts across the country. The overlap wasn't partial. It was almost total. The symptoms that 60 million parasitically infected Americans experience — the ones the CDC calls "few" — are identical to the symptoms driving the fastest-growing diagnostic categories in American medicine. And that's just one species. Toxoplasma gondii is one parasite. One out of more than 120 species known to infect the human gut. The 60 million number covers a single organism. The CDC's own data on other species — Giardia, Cryptosporidium, Blastocystis, the helminths — adds tens of millions more. And those are only the ones with reliable surveillance data, which eliminates most of them because the standard testing is worthless. The O&P exam — the ova and parasite test your doctor orders — has a published sensitivity between 10 and 30 percent for most intestinal species. It checks a single stool sample for a handful of organisms. Published sensitivity of 10 to 30 percent means it misses the vast majority of infections even when they're present. I've spent 15 years analyzing health data. I understand what a 10 to 30 percent detection rate means at scale. It means the 60 million number isn't the ceiling. It's the floor. The lowest possible estimate, based on the least sensitive tools, for a single species. The actual number of Americans carrying chronic parasitic infections — across all species, including the ones that burrow deep enough to evade every test — is a figure that would reshape American medicine if anyone published it. Nobody will publish it. I tried. That's why I lost my funding. — I submitted a preliminary analysis to my department head in March of last year. Forty pages. Cross-referenced symptom prevalence data across six national databases. Showed the statistical overlap between chronic parasitic infection symptom profiles and the diagnostic categories generating the most pharmaceutical revenue in the country. IBS medications alone generate over $1.5 billion annually in the United States. Sleep aids. Antidepressants. Acid reflux prescriptions. Cognitive support supplements. Add them up and you're looking at a market that depends entirely on those symptoms remaining unexplained. My analysis didn't claim parasites caused all IBS. I'm a scientist. I presented the correlation. The symptom overlap. The testing gaps. And I proposed a study: take 5,000 patients currently diagnosed with IBS, chronic fatigue, or unexplained sleep disruption, and run comprehensive parasitological screening — not the standard O&P, but multi-sample PCR-based detection with biofilm disruption protocols. My department head read it over the weekend. Called me Monday morning. "This is interesting work, Rachel. But I can't approve this study." "Why?" "Because if you find what you think you're going to find, we have a problem. A big one. A 'how did we miss this for 30 years' problem. The kind of problem that generates congressional hearings and class action lawsuits, not grant renewals." He told me to shelve it. I didn't. I presented the preliminary data at a conference three months later. Small room. Maybe 40 people. Within a week my department had received calls from two pharmaceutical companies that fund our research center. My grant renewal — which had been approved in principle — was suddenly "under additional review." The review is still ongoing. It will be ongoing forever. — None of this surprised me. Not really. Because the deeper I dug into why the medical system ignores parasitic infection, the clearer the architecture of that ignorance became. The average American medical school devotes approximately four hours to parasitology. Four hours across four years of training. Out of thousands of hours of clinical education. Four hours. To cover organisms that the CDC admits are chronically infecting 60 million Americans from a single species alone. And who funds medical school curricula? The same pharmaceutical companies that generate billions from the medications prescribed when parasites go undiagnosed. The IBS drugs. The sleep aids. The antidepressants. The acid reflux pills. A doctor who understands parasites is a doctor who stops prescribing those drugs. That's not a conspiracy theory. That's a market incentive. I've spent my career studying how incentive structures shape health outcomes at the population level. This one is textbook. So your doctor gets four hours of parasitology training. You walk in bloated, exhausted, foggy, waking up in the middle of the night. She reaches for the only tools she was taught to use. IBS. Stress. Hormones. Aging. She orders the O&P test. It comes back negative. Because it was designed to come back negative. A test with 10 to 30 percent sensitivity isn't a diagnostic tool. It's a rubber stamp that says "no parasites" so everyone can move on to the prescriptions. The tests are designed to miss this. Every missed diagnosis becomes a recurring prescription. $200 a month. $2,400 a year. For five years. Ten years. Twenty years. Multiply that by the tens of millions of Americans whose parasitic infections are hiding behind negative test results and wrong diagnoses. That's not a healthcare failure. That's a business model. One I can see clearly in every dataset I've ever analyzed, and one that nobody in my field is allowed to talk about. — There's a reason parasites are so good at hiding from the tests. And until I understood it, I couldn't understand why 60 million was just the beginning. Parasites don't float around in the digestive tract waiting to be detected. The ones that cause chronic, long-term damage — the ones responsible for the symptoms I was tracking across millions of patient records — they burrow into the intestinal wall. Anchor themselves into the tissue lining. And then they build something that makes them virtually invisible. Biofilm. A thick, dense, biological shield. Gelatinous. Gray. So dense in severe cases that it completely obscures the intestinal tissue underneath. Parasites construct this fortress wall around themselves, and once it's established, they're hidden from the immune system, from laboratory detection, and from every compound you swallow. Biofilm is the reason the O&P test fails. Biofilm-protected parasites don't shed eggs or larvae into the stool consistently. They sit behind their walls. Silent. Invisible. The test looks for what's floating loose. Everything that matters is locked behind fortifications that the test was never built to penetrate. You can have a massive chronic infection — the kind I was tracking across population datasets, the kind producing every symptom that's filling American doctor's offices — and every lab result says you're healthy. That's what "few symptoms" means in the CDC report. It means the infection hides well enough that the system can't find it, so the system pretends it isn't there. Sixty million confirmed infections. With the worst detection tools in modern medicine. For one species. The number that would come back if we actually looked — with tests designed to find what's hiding behind biofilm, across all 120+ species — is the number that ended my funding before I could calculate it. — I need to tell you about the parasites themselves. What they're actually doing inside those 60 million people while the CDC says "few symptoms" and moves on. Parasites are nocturnal. Most active between midnight and 4am. During those hours they feed, reproduce, and release endotoxins directly into the intestinal tissue and bloodstream. That's the 3am wake-up. The one where you bolt awake with your heart pounding and lie there staring at the ceiling until the alarm goes off. That's not anxiety. It's not cortisol dysregulation. It's organisms active inside your gut releasing compounds that trigger your nervous system during the hours you're supposed to be in deep sleep. I found this pattern in the data before I ever felt it myself. Sleep disruption peaking between 2 and 4am is one of the most common complaints in American primary care. Millions of people. The standard response is a sleep aid prescription. The sleep aid sedates you through the parasitic activity window — it doesn't stop what's causing it. The organisms feed while you're chemically unconscious. The prescription gets refilled month after month. The parasites keep building. The sugar cravings — the ones that feel involuntary, like something is pulling you toward the kitchen — that's biological demand from organisms feeding on glucose inside your gut. They consume it before you absorb it. Your body signals for more. You eat the sugar. They eat it first. You gain weight. They grow stronger. Your doctor discusses "dietary discipline" and writes it in your chart. The brain fog. The word-finding problems. Walking into a room and forgetting why you're there. Parasites produce ammonia and neurotoxic compounds that cross the blood-brain barrier. The cognitive effects are documented in the research literature. But your doctor covered parasitology in four hours and wasn't taught to connect the symptom to the cause. So she refers you for cognitive evaluation. The bloating. The fatigue that sleep doesn't fix. The joint aches. The skin issues. The mood swings. Every one of these has a direct parasitological explanation in the published literature. And every one of them is being managed with a monthly prescription instead. Those aren't separate problems being addressed by five different doctors writing five different prescriptions. Those are warnings. Connected. Coming from the same source. From something living inside you that the system was never built to find. — Eight months ago, I became part of my own dataset. Bloating first. My stomach distending after meals. I'd never had digestive issues in my life. Then fatigue — the deep kind, where you wake up after eight hours of sleep and feel like you never went to bed. Then the 3am wake-ups started. Like clockwork. Heart pounding. Wide awake. Lying there until my alarm went off at 6. I recognized the pattern immediately. I'd been staring at it in population-level data for months. The same symptom cluster. The same progression. The same timeline. I went to my doctor. Full workup. Blood panels. O&P test. Comprehensive stool analysis. Everything came back normal. Of course it did. I'd spent the last year of my career documenting exactly why those tests produce normal results in chronically infected patients. A test with 10 to 30 percent sensitivity told me exactly what I knew it would tell me. Nothing useful. I knew oral medications wouldn't reach what I suspected was inside me. Not because I read a blog about it. Because I'd analyzed the pharmacokinetic data. Every oral antiparasitic — pharmaceutical and natural — faces the same set of limitations. Stomach acid degrades the active compounds before they reach the intestines. What survives gets diluted across 20 feet of digestive tract. The concentration that arrives at the intestinal wall — where parasites are actually burrowed, inches deep behind biofilm — is nowhere near enough to penetrate those biological shields. You can't poison something you can't reach. The herbal protocols — wormwood, black walnut, clove — kill whatever's floating loose. The organisms behind biofilm survive. When you stop, they repopulate. Two weeks of improvement, then a crash that's worse than before. I'd seen this cycle in patient data thousands of times. Feel amazing for two weeks while the exposed parasites die. Then the protected eggs hatch behind their biofilm walls — a brand new generation — and the symptoms come roaring back. Prescription antiparasitics hit the same wall. Ivermectin. Fenbendazole. They work on what they can reach. They can't reach what's behind biofilm. And they don't drain the dead ones — the parasites that die inside you release more toxins during decomposition than they did while alive. Without lymphatic drainage, those toxins circulate. That's the "die-off" that parasite cleanse communities celebrate as a sign of healing. It's your body drowning in debris it can't clear. And every oral protocol works during the wrong hours. You swallow the pill in the morning. It passes through your system during the day while parasites are dormant. By midnight — when they emerge, when they feed, when their biofilm shields are at their most permeable — the compound is long gone. Four limitations built into every oral approach. Can't break biofilm. Can't reach eggs. Doesn't drain the dead. Works when parasites are sleeping instead of when they're exposed. I could see all four failures in my data. Patterns of patients cycling through oral protocols, improving temporarily, crashing, starting over. The two-to-three-week cycle repeating endlessly while the underlying infection deepened with every generation. — I started looking for a different delivery method. Something that could bypass the digestive system entirely and reach tissue that nothing swallowed ever would. One compound kept surfacing in my research. Ricinoleic acid. Found in castor oil at 90% concentration. The only natural compound shown to break down biofilm matrices. Not kill parasites through the biofilm. Dissolve the biofilm itself. Expose everything hiding behind it — adults, larvae, eggs — regardless of species, regardless of how deep they've burrowed. I'd known about ricinoleic acid in an academic context. It appears in biofilm disruption studies going back decades. But I'd only ever considered it as an oral compound, and orally it fails for the same reasons everything else fails. Stomach acid degrades it. Dilution destroys the concentration. By the time it reaches intestinal tissue, there isn't enough active compound left to dissolve anything. But the research on transdermal delivery changed the equation. When castor oil is applied directly over the abdomen — with compression and sustained heat — the ricinoleic acid absorbs through the dermal layers. Bypasses the digestive system entirely. No stomach acid. No dilution. Full concentration directly into the tissue surrounding the intestines. Body heat activates the ricinoleic acid and dilates blood vessels, driving it deeper. Compression pushes it inches deep into the tissue where parasites have built their fortresses. Right to the biofilm walls. Right to the organisms anchored behind them. And overnight delivery — 6-8 hours of sustained contact while you sleep — puts the compound to work during the exact window when parasites are feeding, reproducing, and exposed. Midnight to 4am. The hours I'd identified in my data as peak parasitic activity. The hours that generate the 3am wake-ups that fill doctor's offices the next morning. Compression over the abdomen also activates the lymphatic system. Dead parasites, dissolved biofilm, eggs, toxins — flushed out through the body's drainage network. Not left to rot inside you. Not creating the toxic die-off cascade that makes people abandon oral cleanses. The biofilm doesn't stand a chance. Every ancient culture on earth arrived at this independently. Ayurvedic practitioners prescribing abdominal castor oil packs for over 4,000 years. Mediterranean women wrapping their bellies with oil cloths for centuries. Cleopatra used castor oil. Ancient healers called it "Palma Christi" — the palm of Christ. Grandmothers in the American South doing "spring cleaning" on the inside every year. Different continents. No contact with each other. Same compound. Same delivery method. Same results. In my field, when independent populations arrive at the same conclusion without shared knowledge, we call it convergent evidence. We take it seriously. It's one of the strongest signals in epidemiology. And the modern data supports every piece of it. — I tried to set it up at home first. Bought castor oil from a health food store. Soaked an old t-shirt. Wrapped plastic wrap around my midsection. Disaster. Oil soaked through the shirt within an hour. Plastic wrap came undone before midnight. I woke up at 2am with the cloth bunched under my ribs and castor oil on my sheets. I tried three nights in a row with different materials. Each attempt failed the same way. The compression wasn't sustained. The oil wasn't contained. The whole setup fell apart hours before the parasites' active window even started. Fifteen years of precision data analysis and I couldn't engineer a t-shirt to stay on my stomach. Then I found Eden Labs. Organic cotton and bamboo fibers that hold castor oil without leaking. Adjustable compression that stays in place all night — I'm a side sleeper who moves constantly, and it didn't shift once. Designed for overnight wear. No plastic. No mess. No stained sheets. I put it on the first night and understood immediately. The materials held the oil at full concentration. The compression stayed uniform across the entire abdominal area. This was designed for exactly what the data told me I needed: sustained transdermal delivery with consistent pressure over 6-8 hours while you sleep. — Week one. More bathroom activity than usual. Subtle. Steady. I knew what it meant — something was moving. No headache. No crash. No die-off. Quiet drainage. Week two. The bloating resolved. My stomach was flat after dinner for the first time in months. I stood in front of my bathroom mirror and just stared. I'd gotten so accustomed to the distension that its absence felt strange. Week three. This was the week I was watching for. In my data, week three is when every oral protocol collapses. The protected eggs hatch. New generation. Symptoms crash back harder than before. I'd tracked this two-to-three-week failure cycle across thousands of patient records. Nothing crashed. Bloating stayed down. Sleep stayed solid. The biofilm was being dissolved. The eggs were being reached. The cycle that I'd watched destroy thousands of oral cleanse attempts in my datasets was broken. Week four. The 3am wake-ups stopped. Completely. I slept seven uninterrupted hours for the first time since the symptoms started. The brain fog cleared — I sat through a four-hour data review session without losing my train of thought once. Sugar cravings disappeared. Not gradually. The pull toward the kitchen at 9pm just wasn't there anymore. A research assistant I'd worked with for three years looked at me across a conference table and said, "Did you change something? You look different." I hadn't changed anything. I'd just finally eliminated what had been feeding on me. By week six, every symptom was gone. The bloating. The fatigue. The wake-ups. The fog. The cravings. The joint stiffness I'd attributed to too many hours hunched over datasets. I'm 47 years old and I feel clearer and more energetic than I did at 30. Because I stopped being one of the 60 million. I stopped being the statistic I'd spent my career studying. And I reached what the entire medical system told me wasn't there — even though their own data proved it was. — I still work in epidemiology. Different institution now. Smaller. Less funding. No pharmaceutical sponsors. I still see the same numbers every day. The IBS diagnoses climbing. The chronic fatigue rates rising. The sleep disruption epidemic getting worse. Tens of millions of prescriptions being written for symptoms that have a cause nobody is trained to find and no one is funded to study. And underneath all of it, sitting in plain sight in the CDC's own surveillance data, the number that ended my last position and started everything that matters. Sixty million. One species. "Few symptoms." The most dangerous phrase in American public health. Because "few symptoms" doesn't mean you're fine. It means the system counted you, classified you as not worth investigating, and moved on. While the organisms inside you kept building their fortresses thicker, burrowing deeper, and feeding on you every night between midnight and 4am. While your doctor prescribed IBS medication and told you to manage your stress. — The bloating. The fatigue that sleep doesn't fix. The 3am wake-ups. The brain fog. The sugar cravings you can't control. The weight that won't move no matter what you try. Those aren't separate problems requiring separate prescriptions from separate doctors. Those are warnings. Something is living inside you. Building walls. Stealing your nutrients. Releasing toxins into your bloodstream 24 hours a day. And the system that's supposed to find it has spent billions making sure nobody looks. Your tests will come back normal. They always do. A test with 10 to 30 percent sensitivity run by a doctor with four hours of parasitology training is not a diagnostic tool. It's a permission slip to prescribe something else. The only compound shown to break down biofilm is ricinoleic acid — 90% of castor oil. Delivered through the skin. With compression and heat. Overnight, during the hours when parasites are active and their shields are at their most permeable. 90-day money-back guarantee. Every penny back if nothing changes. They're a small company and sell out constantly. If they're out of stock, sign up for the restock. It's worth the wait. Every night you sleep without this is another night they feed. Another night they reproduce. Another night they dig deeper into the tissue and build their fortresses thicker. I spent 15 years analyzing the data that proves something is wrong. I watched my career shrink for saying it out loud. Then I became part of the dataset I'd been studying and discovered the only approach that made sense based on everything the numbers told me. Sixty million Americans are chronically infected with just one species. The CDC published that number and called it harmless. Your doctor was never trained to think about it. The tests were never built to find it. And every prescription written for the symptoms it causes generates revenue that depends on the cause staying hidden. I found the cause in the data. I found it in my own body. And I found the only delivery method that reaches it where it hides. Stop feeding what's feeding on you. EDIT: Almost forgot the link. Here it is:
Like this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.