
 Barbara Hartley
 Facebook ad: “41% of HR+ Women Will Late-Recur. Nobody Has A Plan”
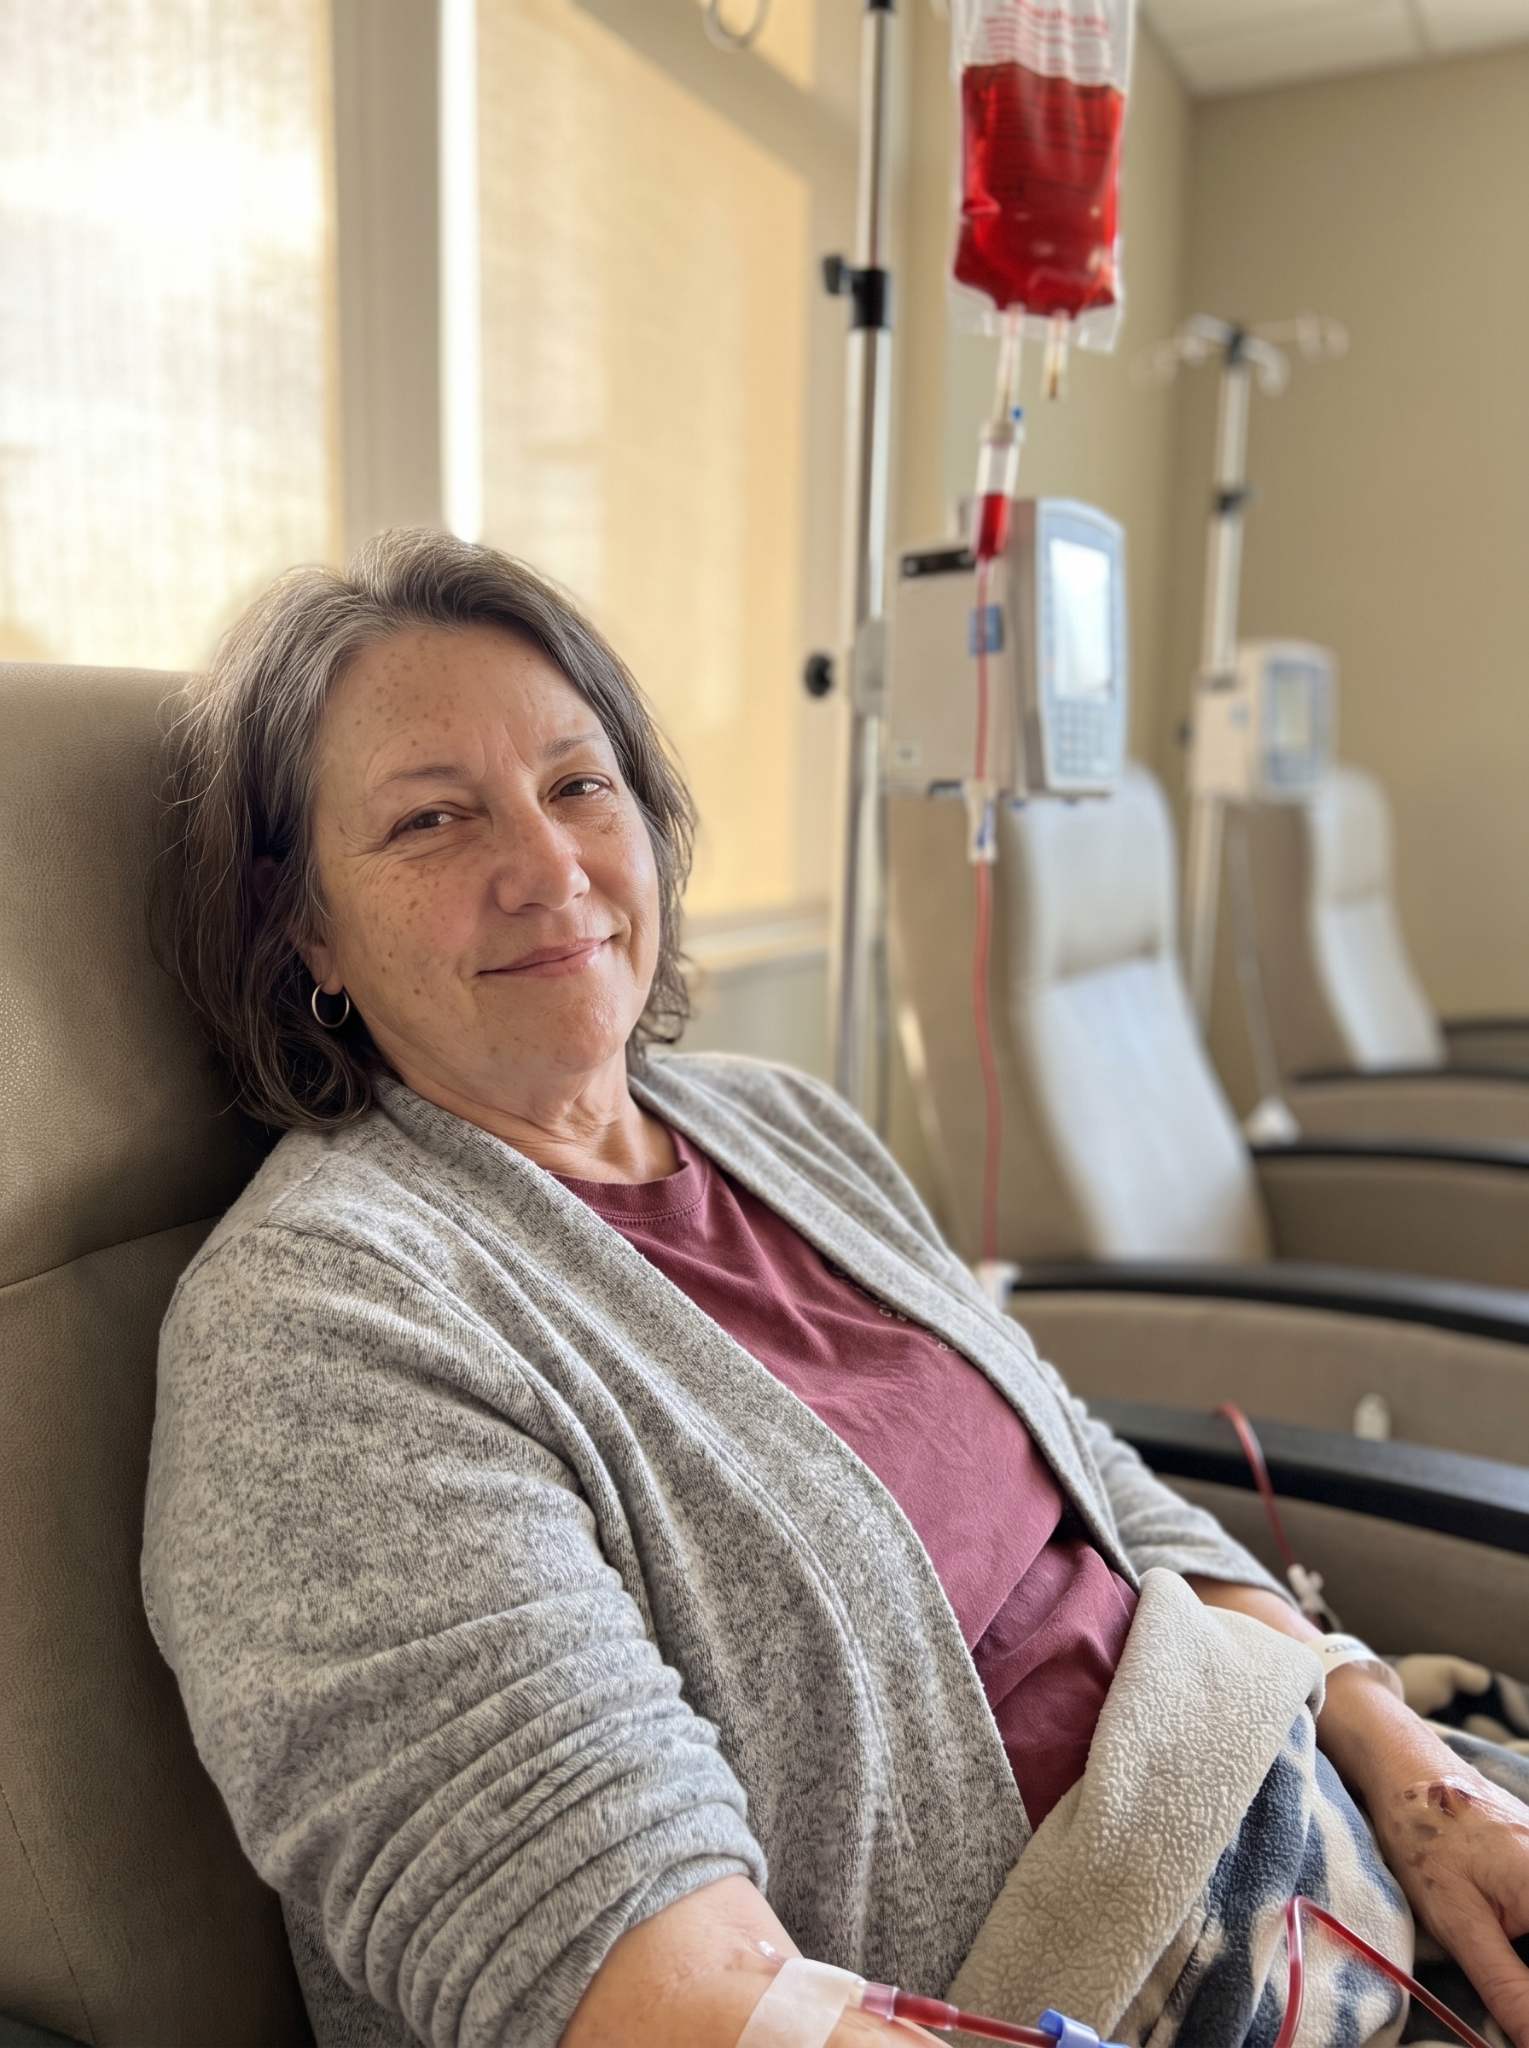
Ran for 23 days, from August 15 to September 7, 2026, the last day Crush saw it.
Run by Barbara Hartley on Facebook. Crush is not the advertiser and does not verify its claims. See this ad in Meta's Ad Library(opens in a new tab)
Want an ad like this for your product?
Crush makes new ad images for your product from this ad: your logo, your product photo, your offer.
Trials from $19.95 USD, then $79.95 USD a month. Cancel anytime.
About this ad
- Meta Ad Library ID
- 1045284185148674
- Platforms
- Relaunches
- 0
Ad text
Caribbean breast cancer survivors do not take an endocrine pill every morning for ten years. No follow-ups every three months. No DEXA scans dropping into osteoporosis. No dormant cells waking up as Stage 4 at year twelve. Zero late recurrences over thirty years. American HR+ women who did everything right: up to 41 percent have their dormant cells wake up between year five and year twenty. I pulled the NIH file after sixteen years as a medical oncologist. Thirty years of tracked data. Buried in a report most oncologists never read. Then the funding was cut. The lead researcher was reassigned. The dataset disappeared. A decade of endocrine pills is worth billions to Big Pharma. Then a former patient of mine called me three years after her second remission. Tumor markers at baseline. She told me what she had been drinking every morning. Let me tell you what she said. My name is Barbara Hartley. I'm 58 years old. Board certified medical oncologist. Retired. Sixteen years at a major cancer institute on the East Coast. I am not some fringe doctor selling crystals on Instagram. I am the system. I prescribed the Anastrozole. I ordered the DEXA scans. I sat across from women who had just rung the bell after eight months of chemo and radiation and I said the sentences oncologists are trained to say. "Congratulations. You're NED. Take this pill every morning for the next ten years and we'll see you in three months." I said those words thousands of times. And I believed them. Then I felt the lump. It was a Tuesday morning in January. Standing in the shower. Soaping under my left arm. My fingers hit something that didn't belong there. Hard. Painless. About the size of a marble. Didn't move when I pressed it. I want you to understand something about this moment. Most women describe it as "the drop." The room shrinks. Your vision tunnels. The doctor keeps talking about margins and lymph nodes and you hear none of it because the only thing in your head is "I am going to die." That's not what happened to me. I felt the marble and I knew immediately it was invasive ductal carcinoma. HR+/HER2-. I knew because I had felt that exact texture under my fingers in clinic a thousand times before. Hard. Immobile. Irregular edges. The exact profile that makes up 70% of the breast cancers I had ever treated. I didn't panic. I didn't cry. I didn't go numb. I finished my shower. I dried off. I stood in front of my bathroom mirror and I said out loud to nobody, "Okay. Ringing the bell is not the end. Ringing the bell is the celebration before the sentence. You know this. You've always known this." And that is the sentence that separated my experience from every patient I have ever treated. I knew what was coming after the bell. Not in the vague way patients know — the relief of finishing chemo, the joy of hair growing back, the assumption that "cured" means cured. I knew it the way a mechanic knows what happens when you fill a tank with the wrong fuel. I knew that HR+/HER2- breast cancer — my subtype, the most common subtype, the one my colleagues call "the best kind" — was going to do the following things to my body in a very specific order. First, I would beat the tumor. My prognosis was excellent. Over 95% of women with early-stage HR+/HER2- reach NED. The surgery would go well. The radiation would work. My tumor markers would drop back to baseline. My hair would grow back. My family would celebrate. My colleagues would hug me in the hallway. Then the second war would start. The one nobody rings a bell for. Because HR+/HER2- has something no other breast cancer subtype has to this degree. It is called cellular dormancy. During the primary tumor's growth, microscopic cancer cells break off and travel through the bloodstream into distant tissue. The bone marrow. The liver. The lungs. The spine. They embed themselves in that tissue. And then — this is the part that separates HR+ from every other breast cancer — they go to sleep. Deep sleep. So deep that no PET scan will find them. No MRI will find them. No CT scan will find them. Not because the technology is bad. Because they are not actively growing. They are not metabolizing. They are not doing anything a scanner can detect. They can stay asleep for five years. Ten years. Fifteen years. Twenty years. And then, one day — when your estrogen levels shift, or when you stop taking your endocrine pill because the joint pain has become unlivable, or sometimes for no reason we can identify — they wake up. And when they wake up, they don't come back as another Stage 1 lump in your breast. They come back as Stage 4 Metastatic disease in the bones or liver or lungs where they've been sleeping. There is no cure for Stage 4 Metastatic breast cancer. There is only life extension. That is the 20-Year Shadow. And here is what I knew from sixteen years of watching it happen to other women. There is a landmark New England Journal of Medicine study — the Pan study — that followed HR+ women who had reached the 5-year NED mark. If she had triple negative or HER2+, that 5-year mark meant she was functionally cured. Recurrence after 5 years for those subtypes is rare. For HR+, the 5-year mark meant nothing. The Pan study proved that HR+ women's risk of the dormant cells waking up remains steady from year 5 all the way to year 20. Depending on tumor size and lymph node involvement at diagnosis, the late-recurrence risk ranges from 10% to 41%. Let me say that number one more time. Up to 41 percent of HR+/HER2- women who successfully reach NED will have those dormant cells wake up between year 5 and year 20. And every oncology institute in this country hands those women an endocrine pill and calls it a plan. Anastrozole. Letrozole. Exemestane if you are post-menopausal. Tamoxifen if you are pre-menopausal. The pill starves the dormant cells of estrogen. That is its only job. And here is the honest truth my colleagues will not print in a patient brochure. The endocrine pill is a slow-motion assault on the rest of your body. It drains every molecule of estrogen out of your tissue. Estrogen is the hormone that keeps your joints lubricated. Your bones dense. Your vaginal tissue intact. Your sleep protected. Your mood stable. Your cardiovascular system healthy. Rip all the estrogen out of a 50-year-old woman for a decade and you get exactly what the endocrine patient experiences every single morning. You wake up with hands so stiff you cannot open a coffee jar without physically massaging your fingers first. You limp to the bathroom because your knees have locked up during the night. Your hips ache going up the stairs. Your ankles crack with every step. This is called AI-induced arthralgia and 60% of the women I put on Anastrozole eventually came into my office begging me to change the dose or take them off the drug entirely. You wake up in a puddle of sweat at 3 AM. Not warm. Not damp. Drenched. Sheets soaked through. Nightgown soaked through. Then chilled. You get up. You change everything. You lie back down. You do it again at 5 AM. You have not slept a full night in nine months. You bleed during intercourse because your vaginal tissue has become paper-thin from estrogen deprivation. Intimacy with your husband becomes a source of pain, then avoidance, then quiet distance you both pretend not to notice. Your DEXA scan drops from a T-score of -0.8 the year of diagnosis to -1.7 at year two to -2.4 at year four. Below -2.5 is osteoporosis. You are watching your skeleton disappear in slow motion while you take the pill that is supposed to keep you alive. And here is what the compliance data shows. Up to 40% of women on endocrine therapy quietly stop taking the pill before they reach the 5-year mark. They don't tell their oncologist. They just stop refilling the prescription. Because the daily quality of life has become worse than the theoretical risk of a dormant cell they cannot see and cannot feel. When they stop, the estrogen returns. The dormant cells wake up. And I have signed dozens of Stage 4 recurrence diagnoses for women who quit their endocrine pill at year three or year four because their body could not survive another day of it. That is the trap. Take the pill and destroy your body slowly. Stop the pill and wait for the dormant cells to wake up. The institution has no third option. In sixteen years of oncology I have never seen a published protocol — from any major cancer institute in the country — for keeping the dormant cells asleep independent of the endocrine pill. We have the endocrine pill. We have surveillance mammograms. We have DEXA scans. We have annual tumor marker panels. We have follow-up appointments every three to six months for the first three years, then every six to twelve months, then annually forever. We have no second wall of defense. If the endocrine pill fails, or you cannot tolerate it, we have nothing. I knew this before I got cancer. I knew this while I was prescribing it. And when I sat in the patient chair myself and I looked at the bottle of Anastrozole they handed me the week after I rang the bell, I decided I was not going to leave that gap empty the way I had left it empty for 2,000 patients before me. Here is what I did not do. I did not take soy isoflavones. I know the online remission forums push these as "natural estrogen support" for menopausal symptoms. But my tumor was ER positive. Concentrated soy acts as a phytoestrogen — meaning it mimics estrogen inside the body. Feeding a phytoestrogen to an ER-positive dormant cell is like ringing a dinner bell inside the exact tissue you are trying to keep starved. I did not take red clover extract for the hot flashes. Same problem. Concentrated red clover is a potent phytoestrogen. It will quiet your night sweats. It may also wake up a sleeping cell in your bone marrow. I did not take DIM at high doses without medical supervision. The molecule affects estrogen metabolism and the dosing window that helps versus harms an ER-positive patient is narrow enough that I would not touch it without a functional medicine physician monitoring my labs. Most supplement bottles do not warn you. I did not take St. John's Wort for the depression that comes with the diagnosis and the joint pain and the sleep deprivation. It forces a specific liver enzyme called CYP3A4 into overdrive and crashes the blood levels of Tamoxifen — the exact drug supposed to be blocking my estrogen receptors. A woman who feels fine on her endocrine pill while quietly taking St. John's Wort may be metabolizing her cancer drug so fast that the pill is doing nothing. I did not drink grapefruit juice or take grapefruit seed extract. Grapefruit does the opposite — it blocks the enzyme your body uses to clear Anastrozole and Letrozole, which sends the drug levels into ranges that can cause organ toxicity. Nobody at my oncologist's office asked me if I was drinking grapefruit juice. I did not take high-dose vitamin E. Studies have shown it can interfere with the way Tamoxifen binds to estrogen receptors, potentially reducing the drug's protective effect. I did not take black cohosh. The estrogenic activity is contested in the literature — some studies show it acts as a phytoestrogen, others show it doesn't. In a body full of dormant HR+ cells, contested is not good enough for me. Seven natural supplements that the internet swears will help you through menopause or through the endocrine pill. Seven biological traps that would have either woken up my dormant cells or canceled the exact drug supposed to be keeping them asleep. I tried none of them. But I did know about soursop. Not from the internet. Not from a blog. Not from a wellness influencer on TikTok. From my own patients. In sixteen years of treating cancer I had noticed something that I never published, never presented at a conference, and never discussed with my colleagues because I already knew what they would say. Post-remission patients who came into my office already taking some form of soursop — usually women from Caribbean or West African families who had been given it by their grandmothers, aunts, and mothers — had different long-term trajectories than everyone else. Not slightly different. Different enough that I started flagging their charts in my personal notes. Their tumor markers stayed at baseline year after year. Their CA 15-3 numbers were not just "in normal range." They were rock stable — the same reading at year one, year five, year ten. Their DEXA scans held longer than they should have on Anastrozole. And in one specific pattern I could not stop tracking — none of them late-recurred. I had a cohort of eleven Caribbean women in my long-term follow-up who all had similar HR+/HER2- profiles at initial diagnosis. Similar stage. Similar tumor size. Similar nodal involvement. All eleven reached NED. All eleven were on endocrine therapy. Six of them were also drinking their grandmothers' soursop preparation. At the ten-year follow-up mark, three of the five who were NOT on soursop had late-recurred with metastatic disease. Two in bone. One in liver. All six who were on the family preparation were still NED. The five non-soursop women had a 60% late-recurrence rate. Right on the upper end of the Pan study's predictions. The six soursop women had a 0% late-recurrence rate. Ten years after ringing their bell. Some of them fifteen years after ringing their bell. I noticed the way you notice a pattern before you have a name for it. A sense that these women's dormant cells were staying asleep in a way I had no biological explanation for. But I never asked them what brand. I never asked them how they prepared it. I never investigated why their late-recurrence rates were essentially zero. Because the institution I worked for had a clear, unwritten rule. You do not recommend botanical supplements to breast cancer survivors. You do not discuss them. You do not validate them. And if a patient asks you about them, you tell them there is "insufficient evidence" and you redirect back to the endocrine pill. I followed that rule for sixteen years. Then I sat in that chair myself with a bottle of Anastrozole in my hand and a body that was about to spend a decade being systematically drained of estrogen. And I pulled the file. The same NIH data I had seen years earlier. Buried in a report most oncologists never read. A Caribbean village of 347 people. Tracked for over 30 years. Zero cases of breast cancer late-recurrence in the entire cohort of women who had been treated for early-stage disease decades earlier. Zero. Statistical modeling of that population predicted a normal late-recurrence rate of 15 to 30% over that time window based on age, stage at diagnosis, and hormone receptor status. The village should have seen dozens of Stage 4 recurrences. They saw none. The villagers had been consuming fermented soursop leaves for generations. Not raw leaves. Not tea. Fermented. For a full year. Cold fermentation in traditional vessels. 365 days. The fermentation is the entire mechanism. It transforms the raw leaf compounds into bioavailable acetogenins at a concentration — 2% — that the raw plant can never reach. Without fermentation the concentration stays below 0.5%. Below therapeutic range. Below anything your body can actually use to keep dormant cells asleep. And here is the part that made me angry. I already knew this. Years earlier. I had seen it in the long-term follow-up charts of my Caribbean patients. I had seen the compound work in real time inside real women who should have late-recurred and didn't. And I had never said a word to anyone because the institution told me not to. The institution that now had me in their chair holding a bottle of Anastrozole and a prescription for annual DEXA scans to watch my bones disappear. I ordered SimplySours the night I pulled the NIH data for the second time. Let me tell you why I chose them because this part matters. Every other soursop product I tested — and I tested eleven — failed one or both of the critical tests. VitalSour claimed pharmaceutical-grade. Lab showed 0.5%. No fermentation records. Fruit-based, not leaf-based. Useless. HerbaSour Naturals claimed organic Caribbean. Lab found pesticide contamination and heavy metal traces. I threw it away. PureLeaf Soursop claimed six months of fermentation on the label. Lab confirmed 40 days. Lied right on the bottle. 0.3% concentration. Annona Gold claimed 2% on the front label. Actual lab result: 0.35%. Deliberately mislabeled. TropicaPure. TropicWell. SourLeaf Naturals. VitaMax Botanical. Eleven brands. All failed. SimplySours passed every test. Certificate of Analysis. ISO 17025 certified. Zero heavy metals. Zero pesticides. Full 365-day fermentation confirmed by batch logs with timestamps. Heritage Caribbean trees in volcanic soil. Leaf-only — ten times more concentrated than fruit. 2% acetogenin verified by independent lab. And the format solved the biggest problem post-remission women face with supplements. You are already choking down a horse pill every morning that you resent. You have set alarms on your phone. You have arguments with yourself in the mirror about whether to keep taking it. The last thing you want is another chalky capsule added to that pile. SimplySours delivers the acetogenins in a pectin-bound gummy. Pectin is fruit fiber. Your brain recognizes it as food, not medicine. No struggle. No gag. No adding another pill to the stack that already makes you dread mornings. And pectin dissolves slowly. Not a thirty-minute spike your kidneys flush before it helps. A steady twelve-hour release that keeps the acetogenins active in your bloodstream around the clock — the same way a dormant cell needs constant fuel starvation to stay asleep. One-hit doses do not work for dormancy. Steady presence does. The liquid drops hit and leave. The capsules pass through the gut whole. The gummy stays and works. I took my first one on a Wednesday morning standing at my kitchen counter. Nine months after I had rung the bell. Nine months into my Anastrozole prescription. My hands were already stiff. My hips were already aching. I had lost two teaspoons of bone density on my last DEXA. My hot flashes were waking me up three times a night. I put the gummy in my mouth. I chewed. It tasted like fruit. I did not feel it in my joints. I did not feel it in my stomach. I felt nothing except that for the first time in nine months, I had put something in my body that did not hurt me. I took one gummy every morning for the next six months alongside the Anastrozole. Month one — nothing dramatic. But the joint stiffness in my hands eased noticeably by week three. Not gone. But I could open a coffee jar without wincing. I could grip a steering wheel without white knuckles. Month two — first tumor marker panel post-SimplySours. CA 15-3: 12. Baseline. Exactly where it was the week after I rang the bell. My oncologist made a small note in my chart. Month three — hot flashes reduced from three per night to one. I slept through the night for the first time since starting Anastrozole. My eyes had color under them again. Month four — DEXA scan. My T-score had held from the previous panel. It had not dropped. Anastrozole should have continued the slow erosion. It didn't. Month five — intimacy with my husband stopped hurting. The vaginal atrophy that had made physical connection impossible for eight months began to reverse. I do not have a biological explanation for that one. But it happened. Month six — CA 15-3: 11. DEXA held. Ki67 tumor markers on the panel my oncologist ordered — undetectable. Eighteen months into SimplySours my oncologist looked at my file for a long time. Every marker holding. Bones stable. Tumor markers rock steady. He said, "Barbara. Whatever you're doing, continue." I have said that exact sentence to patients who surprised me. Word for word. I never knew what it felt like from the other side until it was mine. That was two years ago. I am still NED. My last four tumor marker panels have come back at baseline. My DEXA has not dropped. I have not late-recurred. I still take my Anastrozole every morning because I am not going to pull down the first wall. But I have added a second wall behind it. And that second wall is what has let me function. I retired from the institute six months into my second year of remission. Not because I was forced out. Because I could not go back to doing what I had been doing for sixteen years knowing what I now knew. I could not sit across from another HR+/HER2- woman who had just rung the bell and hand her a bottle of Anastrozole and tell her to "just push through" the joint pain while I watched her walk out of my office knowing that 40% of women in her exact situation quietly quit the pill within four years and 10 to 41% would late-recur into Stage 4 disease. I could not follow the unwritten rule anymore. The institution doesn't want doctors recommending botanical compounds to cancer survivors. That is the rule. I followed it for sixteen years. I followed it while I watched Caribbean women in my long-term follow-up not late-recur and I said "insufficient evidence" every single time a remission patient asked me if there was anything else she could do. There is not insufficient evidence. There is inconvenient evidence. Evidence that a non-patentable plant compound growing on a tree in the Caribbean can do what my institution has no second-line drug for. Evidence that traditional preparations used for generations by communities our medical system has never studied can keep the dormant cells asleep even when the endocrine pill has to be reduced or the patient can no longer tolerate it. There is no Herceptin moment for HR+/HER2-. The community waiting rooms know it. We do not have a drug in the pipeline that will do for late recurrence what Herceptin did for HER2 relapse. We have Anastrozole and Letrozole and Tamoxifen and hope. The institution knows this. And still — every one of my colleagues will say "insufficient evidence" when a remission patient asks about soursop. They don't deny it because it doesn't work. They deny it because it works. And it costs less than a dinner at a restaurant. And there is no pharmaceutical patent to protect. And there is no billing code. And there is no profit margin. And a cheap compound that reduces late-recurrence rates would collapse a decade of guaranteed revenue for the endocrine pill manufacturers and every follow-up appointment on my old clinic's calendar. I do not work for SimplySours. I receive nothing for writing this. I am a retired oncologist who got HR+/HER2- breast cancer, rang the bell, took the pill, and discovered that the most important thing I did for staying NED long-term was something I would have been trained to tell every one of my own patients not to take. If you are in remission right now and you are staring at a bottle of Anastrozole or Letrozole or Tamoxifen every morning and your joints are screaming and your sleep is destroyed and you are counting down the days until you can stop the pill — Please build the second wall. Do not stop your endocrine pill. Do not skip your follow-ups. Do not ignore your tumor markers. That pill is the first wall. Keep taking it. Every day. But add the second wall behind it. So that if the pill fails, or if the pain forces you to reduce the dose, or if you finally reach year five or year ten and your oncologist takes you off it — the dormant cells still have nothing to wake up on. One gummy. Every morning. Five seconds. No horse pill added to your stack. No nausea. No fighting your body. SimplySours. 365-day cold-fermented soursop leaf extract. 2% acetogenin concentration. Heritage Caribbean trees. ISO 17025 lab certified. Pectin-bound slow-release delivery. Order it directly from the company. Not Amazon. The Amazon counterfeits are raw soursop with no fermentation. They will not touch the dormancy mechanism. The real product only ships from here: https://simplysours.shop/products/100-pure-organic-soursop-gummies They produce one batch per year. The fermentation takes 365 days. There is no way to speed it up. In 2026 you are buying the 2025 fermented batch. It sells out every year by August or September. Once it's gone you wait twelve months. EDIT: Since I posted this, my messages have been full of women in remission saying they bought soursop on Amazon and their tumor markers didn't hold. SimplySours does not sell on Amazon. Anything you find there is not their product. The fermentation is everything. Amazon supplements are not fermented for 365 days. Please buy directly from the website: https://simplysours.shop/products/100-pure-organic-soursop-gummies P.S. If you are considering stopping your endocrine pill because the side effects have become unlivable, please talk to your oncologist first. Do not stop cold turkey. But if you are already on the pill and simply want a second line of protection behind it, add the gummy tomorrow morning. My tumor markers have held at baseline for two years running with the pill plus the gummy. The pill starves the cells of estrogen. The gummy starves them of the metabolic fuel they need to wake up. Two locks on the same door: https://simplysours.shop/products/100-pure-organic-soursop-gummies P.P.S. I made a promise to myself the morning I rang my own bell. I promised that if the dormant cells stayed asleep, I would not keep quiet the way I kept quiet for sixteen years while my Caribbean patients showed me the answer and I said "insufficient evidence" to every white woman who asked me for it. I kept that promise. I am a retired oncologist writing under my own name telling you that the second wall exists. The institution knows. I am building it in my own body every morning. I would build it in yours if you were sitting across from me in an exam room today: https://simplysours.shop/products/100-pure-organic-soursop-gummies
Where the ad sends people
simplysours.shop
41% of HR+ Women Will Late-Recur. Nobody Has A Plan 👇
Every HR+/HER2- woman who reaches NED is handed a daily pill and told she's done. She isn't. What nobody explains is what wakes up dormant cells 15 years later.
Order now: simplysours.shop(opens in a new tab)


















