
Active· since Aug 29, 2026
- 18
- days running
- 1
- relaunches
Ad copy
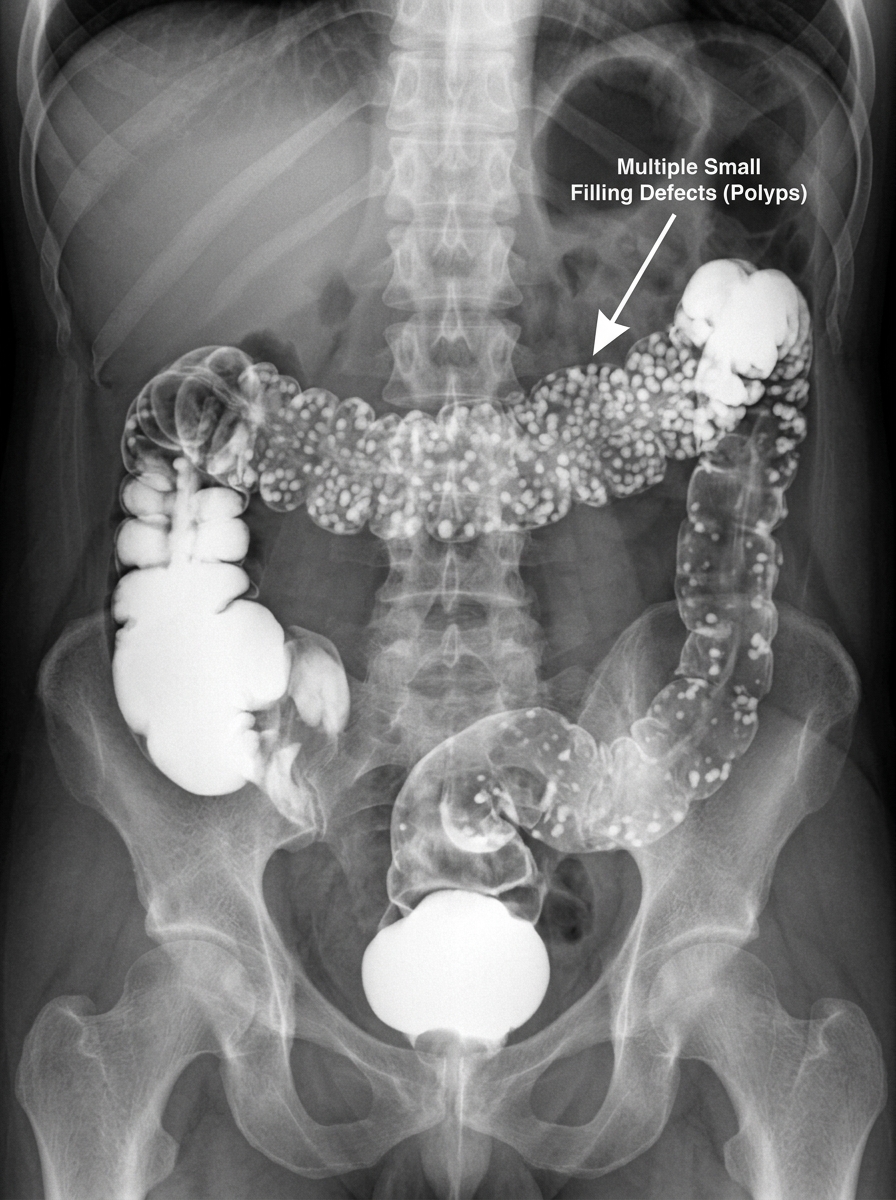
I do not care if this upsets you. I am going to say something that nobody with chronic constipation wants to hear. I performed my 347th colectomy on September 14th, 2024. Five weeks later, at 3:12 AM on October 22nd, I was the one being wheeled into the emergency room. I was 58 years old. I am a board-certified gastroenterologist. Twenty-two years of practice. A CT scan of my own abdomen showed fecal loading from my cecum to my sigmoid. Colonic walls thinned to the point where the ER attending used the phrase "perforation risk." The same phrase I had dictated into charts for hundreds of patients over two decades. I was twelve hours from the same procedure I had performed on patients for twenty years. The ER bill was $14,200. Follow-up imaging and specialist consults added another $6,800. They will let me practice again. My hospital privileges are intact. But I will never recommend another scoop of MiraLAX without remembering that I was on that same gurney with a colleague reading my own CT scan because everything I was taught to prescribe had not saved me. I am writing this because I know exactly what my colleagues will say when they see it. I do not care. If you are over 45 and you have been dealing with chronic constipation, or someone you love has, please read the entire thing. I know it is long. I know you are scrolling. I know you have things to do. Fifteen months ago I would have given anything for someone with my credential to sit me down and tell me what I am about to tell you. Nobody did. I was put on MiraLAX six years ago at 52. My days-between had climbed to five, then seven. Straining every time. Hard pellets that took forty-five minutes and left me shaking. Bloating so bad I could not button my slacks by 2 PM most days. The diagnosis did not surprise me and it did not. My mother had chronic constipation for the last twenty years of her life. She was on MiraLAX, then Dulcolax, then a prescription her doctor kept adjusting. She ended up with a colostomy bag at 67. Dead at 69 from post-surgical complications. I had watched the pattern in my own family and I had built my entire practice on treating patients who looked like my mother. I did what any gastroenterologist would prescribe. I started MiraLAX at diagnosis. A daily scoop in water every morning. My internist referred me back to my own department when the MiraLAX stopped producing results a year later. A colleague added Linzess. When Linzess stopped working reliably, they switched me to Amitiza. Three medications. Two of them medications I had personally prescribed to hundreds of my own patients. I drank 80 ounces of water a day. I ate 35 grams of fiber. I walked three miles every morning before rounds. I tried the Squatty Potty. I tried magnesium citrate on weekends. I ordered a colonoscopy on myself the year I started MiraLAX. Clean scope. No structural issues. I checked every box on my own protocol. By last September I was going every three to four days with pharmaceutical help. My bloating was manageable with diet timing. My colonoscopy was clean. By the standard of the guidelines I had helped write for our hospital's GI department, I was managed. Managed. That word again. I ordered a comprehensive stool panel on myself last September, six years after I started MiraLAX. I did it because a feeling would not leave me alone. My butyrate level came back at 8.2 micromoles per gram. For context, I have called patients with levels twice that and used the sentence, we need to address this now, not next quarter. Normal is 20 to 30. Mine was 8.2. The chemical signal that tells the colon to squeeze was barely whispering. I sat in my office staring at my own labs on my own screen and I recognized something. I was doing exactly what my mother had done. She had been managed for twenty years before the colostomy. She had been on MiraLAX and then Dulcolax and then a prescription. Her colonoscopy had read clean every five years. Her chart had said managed. And she had died at 69 in a rehabilitation facility twelve weeks after they removed half her colon. I did not follow up on my own stool panel because I already knew what the pattern meant. I did not want to see it confirmed. I told myself I had time. Six weeks later my husband found me on the bathroom floor at 3 AM. I had not had a bowel movement in nine days. The cramping started at 1 AM. By 2:30 it was constant pressure against my pelvic floor. I knew, with the clinical certainty of a woman who has performed hundreds of these procedures, that I was impacted. My husband, an orthopedic surgeon, sat up before I could finish the sentence. He is not a GI clinician but he has heard me describe this presentation at our dinner table for twenty years. He drove me. We went to a hospital across town. Not my own. Because I did not want the residents I had trained to see me on that gurney. They saw me anyway. The ER attending was a woman I had consulted with on three cases the previous year. She walked into the room, saw me, and her face did the thing. She said my name. I need imaging, I told her. CT abdomen and pelvis. Fecal loading. Get me the surgical consult if the wall is thinned. She nodded. The CT confirmed what I already knew. Fecal loading from cecum to sigmoid. Colonic walls dangerously thinned. The radiologist flagged perforation risk in the report. The surgeon who came in was a colleague I had referred patients to for fifteen years. He read the scan. He looked at me. "Carla, if this happens again, we are talking about a colostomy. You know that." I knew that. I had said those exact words to patients in that exact tone for twenty-two years. I was admitted for three days. Manual disimpaction under sedation. IV fluids. Colonic irrigation. I came home on October 25th with my husband, a heating pad, and a discharge sheet listing the same medications I had personally recommended to hundreds of patients over two decades. I did not want the full GI workup my colleagues were suggesting. I ran it on myself anyway. Because I knew that if I did not, in eighteen months I would be reading another patient's post-operative notes and seeing my own trajectory in them. The comprehensive stool panel confirmed what the September test had hinted at. Butyrate at 8.2. Total short-chain fatty acids at 46 percent below normal. Akkermansia muciniphila undetectable. Faecalibacterium prausnitzii at the 4th percentile. The bacteria that are supposed to live in the mucus lining of my colon and send the signal to squeeze were either gone or starving. A motility study showed transit time of 94 hours. Normal is 30 to 40. A follow-up colonoscopy showed visibly thinned mucosa throughout the descending colon. The gastroenterologist who performed it, a former student of mine, used the phrase "significant mucosal atrophy." She was careful not to look at me when she said it. Every system in my gut was showing the pattern I had watched in hundreds of my own patients. Same problem. Same thinning lining. Same missing bacteria. Same dead signal. I sat in my office on November 3rd with all the reports in front of me and I understood something I had never let myself understand before. Every intervention in my medication list had been treating a downstream symptom. MiraLAX was pulling water into the pipe to force things through. Linzess was opening chloride channels to push fluid into the bowel. Amitiza was doing the same thing through a different channel. Not one of them had touched what was actually causing the stoppage. I am a gastroenterologist. I am supposed to be the person who knows how to fix this. I had prescribed the exact protocol I was on to hundreds of patients who looked like my mother. Every one of those prescriptions had followed the guidelines. Every one had been the correct standard of care. And it had failed me at 58. I sat at my desk that night at 11 PM after my husband had gone to bed and I did something I had not done since fellowship. I opened the research databases and I searched for the actual mechanism. Not the management guidelines. Not the prescribing protocols. The mechanism. I read for four hours. What I found rearranged twenty-two years of what I thought I understood about chronic constipation. The mucus layer. A thin, slick coating that lines the inside of the colon. It is what waste slides along. Without it, nothing moves, no matter how much water you pull into the pipe or how hard you force the wall to squeeze. Living inside that mucus layer is a crew of bacteria. Akkermansia. Faecalibacterium prausnitzii. They survive by eating the mucus, and they pay rent in a compound called butyrate. Think of them as tenants who pay rent. When the tenants are fed and housed, they pay their landlord in butyrate. Butyrate is the go-signal. It is the chemical message that tells the smooth muscle of your colon wall to contract and push. Stop feeding the crew, they leave. The rent stops. The landlord shuts down. That is chronic constipation. Not a plumbing problem. A payroll problem. None of this was hidden. It sat in journals I had had access to for twenty-two years. I had read those journals every month. I had read them for the surgical outcomes. I had never read them for the mechanism papers because my training had told me the mechanism was secondary and the treatment was to manage the symptom. My training was wrong. But there was one more finding, and it was the one that kept me up until 3 AM. Researchers studying the gut microbiome had found that in animal studies, polystyrene microplastics administered orally caused constipation directly. Decreased stool weight. Decreased water content. Abnormal stool shapes. Decreased motility. And visibly thinner mucus layers with fewer goblet cells, the cells that produce the mucus in the first place. In longer studies, the same exposure suppressed the genes that build the mucus layer. The blueprint for the housing was being erased. In workers with heavy plastic exposure, the same pattern showed up. Beneficial bacteria dropped. I sat back in my chair. Thirty years of reheating leftovers in plastic containers. Drinking from plastic water bottles. Microwaving in plastic. Nobody did anything wrong. Everyone was living the same way. Nobody has proven this happens in your colon specifically. What has been proven is that your colon looks exactly like a colon that this happened to. And once the housing thins, the cascade is predictable. The mucus layer thins. The bacteria who lived there lose their home. Without them, butyrate production crashes. Without the signal, the colon does not squeeze. Without the squeeze, nothing moves. That is what every failed fix had been chasing the wrong end of. MiraLAX pulls water through the pipe but never rebuilds the lining. Linzess forces a contraction over the top of a dead signal. Amitiza does the same through a different channel. Motegrity pushes a serotonin signal into a wall that has already lost its mucus and its bacteria. More fiber on a dry pipe is more traffic on a road with no surface. I had been prescribing all of them. For twenty-two years. I closed my laptop at 3 AM. I sat at my kitchen table. I could not sleep. I understood at that moment that I had prescribed the exact protocol that failed me to hundreds of other people. And every one of them was sitting at home with the same dead signal and the same thinning lining, waiting for their October 22nd to arrive. Two weeks later a patient came in for follow-up who should not have been in the shape she was in. Her name was Mavis. Chronic constipation for fourteen years. She had been my patient for four years after her primary care doctor referred her when MiraLAX stopped working. Her days-between at intake had been seven to nine. She had been on MiraLAX, Linzess, and a fiber supplement. I pulled her chart before she came in expecting to increase her Linzess dose. Her days-between were one. Every morning. On her own. She had stopped all pharmaceutical assistance eight months earlier. I looked at her across the exam room and asked her what she was doing. She was quiet for a moment. Then she said, "Doctor, my cousin's mother-in-law lives out near Lancaster County. She has been telling all of us for years. I did not bring it up because I did not think you would take it seriously." I asked her what this woman had told her. She wrote a name and a town on the back of my prescription pad. Lillian. A small town I had never heard of near Lancaster, Pennsylvania. A farmhouse where an 81-year-old woman had been growing elderberries the old way for sixty years. I drove there the following Saturday. I did not tell my husband where I was going. I did not tell my practice partner. I did not tell anyone in my hospital that a board-certified gastroenterologist was driving two hours to meet an 81-year-old elder in Lancaster County because everything I had been taught in twenty-two years of practice had not saved me. I pulled into the driveway of a white farmhouse at 11:15 AM. The garden along the front was deep and orderly. Raised beds of herbs I recognized from pharmacology references. Elderberry bushes along the south side of the house, heavy with dark fruit. The kind of quiet, deliberate growing that takes decades of knowledge. She was on the side porch sorting berries into a wooden bowl. Small woman. Thin. Early eighties. White hair pulled back. Hands steady and sure. I introduced myself. Not as a gastroenterologist. As Carla. She looked up with clear sharp eyes and asked me why I had come. I told her. I told her I was a GI specialist. Twenty-two years in practice. That my own bowel had shut down five weeks earlier. That my three medications had not saved me. That a colleague had told me I was one more episode away from the same colostomy I had performed on hundreds of patients. That one of my patients had told me about her. She listened. She did not interrupt. When I finished she set the bowl down and said, "Come inside, doctor." Her kitchen smelled like dried herbs and wood smoke. She poured me tea without asking. She sat across from me and said, "Your medicines are fighting the wrong fight. You know this. That is why you are sitting at my kitchen table." I did know it. She said, "Every medicine you prescribed for yourself. Every medicine you prescribed for your patients. All of them work on the movement from the outside. That is all. The lining underneath, the coating your bowel is supposed to slide waste along, none of them rebuild it." I said, "I understand the mechanism. I read the research last month." She smiled. "Then you understand it from your journals. You do not yet understand it in your own body." She reached into the bowl and picked up five dried elderberries. Small. Dark, almost black. She set them on the table in front of me in a row. "This one is your MiraLAX." She tapped the first berry. "This one is your Linzess." The second. "This one is your Amitiza." The third. "This one is your Motegrity." The fourth. "And this one," she tapped the fifth, "is the surgeon who wants to cut out half your colon." She looked at me. "Five stages. Five different pills and procedures. Every one of your specialists will tell you they are treating five different problems. It is one problem. The coating inside your bowel has dried up. The crew that lived in that coating is gone. And the signal they used to send, the one that tells your body to squeeze, has stopped." I nodded. I could not speak. She said, "Your MiraLAX pulls water through a pipe that has no slide left. Your Linzess forces a squeeze from a wall that has lost its signal. Your Amitiza does the same thing from a different direction. Your Motegrity pushes on a muscle that has forgotten how to listen. And when all four of them fail, your surgeon removes the pipe." She leaned forward. "The colostomy your colleague put on the table did not fix your lining. It removed the problem by removing the organ. If the lining is not addressed, you will be in that operating room within two years. This is not opinion. This is the pattern you already understand." I said, "I know." She said, "For over two hundred years the women in this community have been using one thing for this. My grandmother grew it. Her grandmother before her. I am eighty-one. I have never been backed up for more than a day in my life. My daughters do not have this problem. My granddaughters do not have this problem." She stood. She walked to a shelf above the stove. She pulled down a dark glass jar. Inside were dried elderberries, the same deep black-purple as the ones on the table. "Black elderberry," she said. "Not what your patients are buying in gummies at the drugstore. What is sold as elderberry at the store is cooked at high temperature so it survives a year on a shelf. The heat destroys the anthocyanins. The anthocyanins are the only part that feeds the bacteria living in your colon's lining." She set the jar down. "The polyphenols in cold-extracted elderberry are the specific food that the bacteria in your mucus layer eat. In a published clinical study, standardized elderberry polyphenol extract produced a sustained expansion of Akkermansia, the bacteria that live in your mucus layer, in a significant number of participants. Gut diversity increased by nearly 50 percent. A separate study showed elderberry raised the two biggest butyrate producers in the gut. The bacteria come back. The signal restarts. The colon starts squeezing on its own." She held up the jar. "This is what they take for stage 1. And stage 2. And stage 3. And all of them. One thing. Because it is one problem." I asked her if the form mattered. She nodded. "It has to be cold-extracted. Never heated. Heat kills the anthocyanins and then you are swallowing a berry-flavored nothing. It has to be the full-dose extract, not a gummy with sugar and a fraction of the compound. And it has to be the heirloom variety, grown the way my grandmother grew it, because the commercial cultivars have been bred for sweetness and shipping, not for what your colon needs." She paused. "There is a small company. They source the heirloom variety. Cold-extracted so the heat never touches it. Full clinical dose of the anthocyanins. Zinc citrate and buffered vitamin C to help repair the lining that years of laxatives roughed up. Third-party tested. Made in the USA." She wrote a name on the back of a receipt and slid it across the table. Elvera. I ordered three bottles from her kitchen table before I left Lancaster County. I drove two hours home. I did not tell my husband where I had been. The bottles arrived the following Wednesday. I took two capsules with my dinner that night. Week one. My bloating started to ease by day four. I had been timing my meals around my clinic schedule to avoid the worst of the distension. On day five I ate lunch at noon like a normal person and did not have to unbutton my slacks by 2 PM. I sat at my desk at 4 PM and I recognized that my abdomen felt quiet for the first time in months. Week two. I had a bowel movement on my own. Without MiraLAX. Without Linzess. Without anything. Tuesday morning, 7:15 AM. I sat on the edge of the bathtub afterward and stared at the wall because I did not know what to do with the feeling of something working that I had not forced. Week three. I was going every other day. The straining had stopped. The stools were formed. Not pellets. Not the rock-hard fragments I had been passing for years. Formed, soft, complete movements. Week four. Every morning. On my own. I woke up, went to the bathroom, and it happened the way it is supposed to happen. The way I had not experienced since my early forties. Week six. I ordered a follow-up stool panel through our hospital's outpatient lab. Butyrate 18.4. Up from 8.2. I ran the panel twice because I did not believe it. Both runs matched. Week eight. Butyrate 22.6. Akkermansia detectable for the first time since I started testing. Faecalibacterium at the 38th percentile, up from the 4th. Total short-chain fatty acids within normal range. Week twelve. Full panel. Butyrate 24.1. Transit time 34 hours. Down from 94. Days-between: zero. Every morning. On my own. Bloating resolved. I called the colleague who had warned me about the colostomy and asked her to review my follow-up imaging. She did. She looked at me. "Carla. What did you do." I told her. The elder in Lancaster County. The kitchen table. The elderberries. The mucus layer. The butyrate signal. All of it. She listened for forty minutes without interrupting. When I finished she was quiet for a long time. Then she said, "I have not been trained on this. But I want to see this in my own patients. Tell me the name of the product." I gave it to her. She has been recommending it to eleven of her chronic constipation patients for the last three months. She called me last week. Seven of them have reduced or stopped their MiraLAX. Two have come off Linzess entirely with their doctors' supervision. I am still rebuilding after years of laxative dependency. My mucosal lining is still healing. I ate a full meal at a restaurant with my husband last week without calculating when the bloating would hit. A bowl of pasta at a small Italian place near our house. Nothing happened. My abdomen stayed quiet the rest of the evening. My last butyrate reading two weeks ago was 25.3. I came within twelve hours of a colostomy at 58. I am writing this because I still have my practice. I still have my husband. And I have watched every marker in my gut move in a direction I had not seen in a patient chart in twenty-two years. I have watched a colleague I trained look at my labs and say the word I had waited eleven months to hear. Improving. Not managed. Improving. Your chart says managed. Your body says dependent. Those are not the same word. I am also writing this because I know the truth about what my profession is doing. I did not sit at that elder's kitchen table because I wanted to. I sat there because everything my medical school and my board certification and my twenty-two years of practice had taught me about how to treat chronic constipation had failed me. I performed 347 colectomies before my own bowel shut down. Every one of those patients left my practice with the same protocol I was on. Every one of them was told they were managed. I do not know how many of them are already back for follow-up procedures. I do not know how many of them ended up with the bag. I know that the standard of care my hospital taught me was built on the assumption that managing the downstream symptom with medications that force the process from the outside was equivalent to addressing the upstream failure driving the whole thing. It is not. I have my own stool panels and CT scans that prove it is not. And my mother's surgical record from twelve years ago proves it was not for her either. If your mother, your sister, your wife, or you have been dealing with chronic constipation and you have been told your colonoscopy is clean while your body is quietly falling apart, please listen to what I am telling you. The dead signal is what is failing you. Not the lack of fiber. Not the lack of water. The MiraLAX pulls water through the pipe. It does not rebuild the lining. It does not feed the bacteria. It does not restart the signal. More fiber does not save you. I ate 35 grams a day for six years and it did not stop what was coming. Probiotics do not save you. Dropping strangers into housing that no longer exists. Without the mucus layer to anchor them, they pass straight through. There is one thing I know of that feeds the crew that rebuilds the lining and helps restore the signal. The anthocyanins in cold-extracted heirloom elderberry. They feed Akkermansia and Faecalibacterium. Those bacteria produce butyrate. Butyrate is the go-signal. The colon starts squeezing on its own. Fed, not forced. Elvera. Cold-extracted heirloom elderberry. Full clinical dose of anthocyanins. Zinc citrate and buffered vitamin C for lining support. Third-party tested. Made in the USA. Two capsules every evening with dinner. That is the whole protocol. B2G1, three bottles for $67.20. 30-day money-back guarantee. If your body does not respond, you pay nothing. The system that trained me did not give me this when I needed it. It is reaching you now. Over 100,000 women are taking Elvera. https://tryelvera.com Carla P.S. My mother was on MiraLAX for twelve years before they removed half her colon. She spent her last two years with a colostomy bag and died of post-surgical complications at 69. I built my entire GI practice on the assumption that I would help my patients avoid what happened to my mother. Instead I watched myself walk the same trajectory in my own body. The difference is that I got the twelve-hour warning my mother never got. Please do not let your family's warning be shorter than mine was. P.P.S. I do not work for Elvera. I do not receive a penny from this. I am writing this at 11:40 PM on a Sunday, alone in my office, because a patient came in Friday whose days-between had gone from seven to one in six weeks and I recognized my own numbers on her chart. She had found Elvera on her own after reading something a woman in her church group had shared. She told me it had been going around among the women in her Sunday school class for months. It was the second time in three months I had recognized my own patient's turnaround in a story written by a stranger. Please share this with anyone you love who has chronic constipation. Even a little. Even occasional. Even if they think they are managed. I promise you they are not.
Like this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.