Inactive· since Apr 12, 2026
- 51
- days it ran
- 1
- relaunches
Ad copy
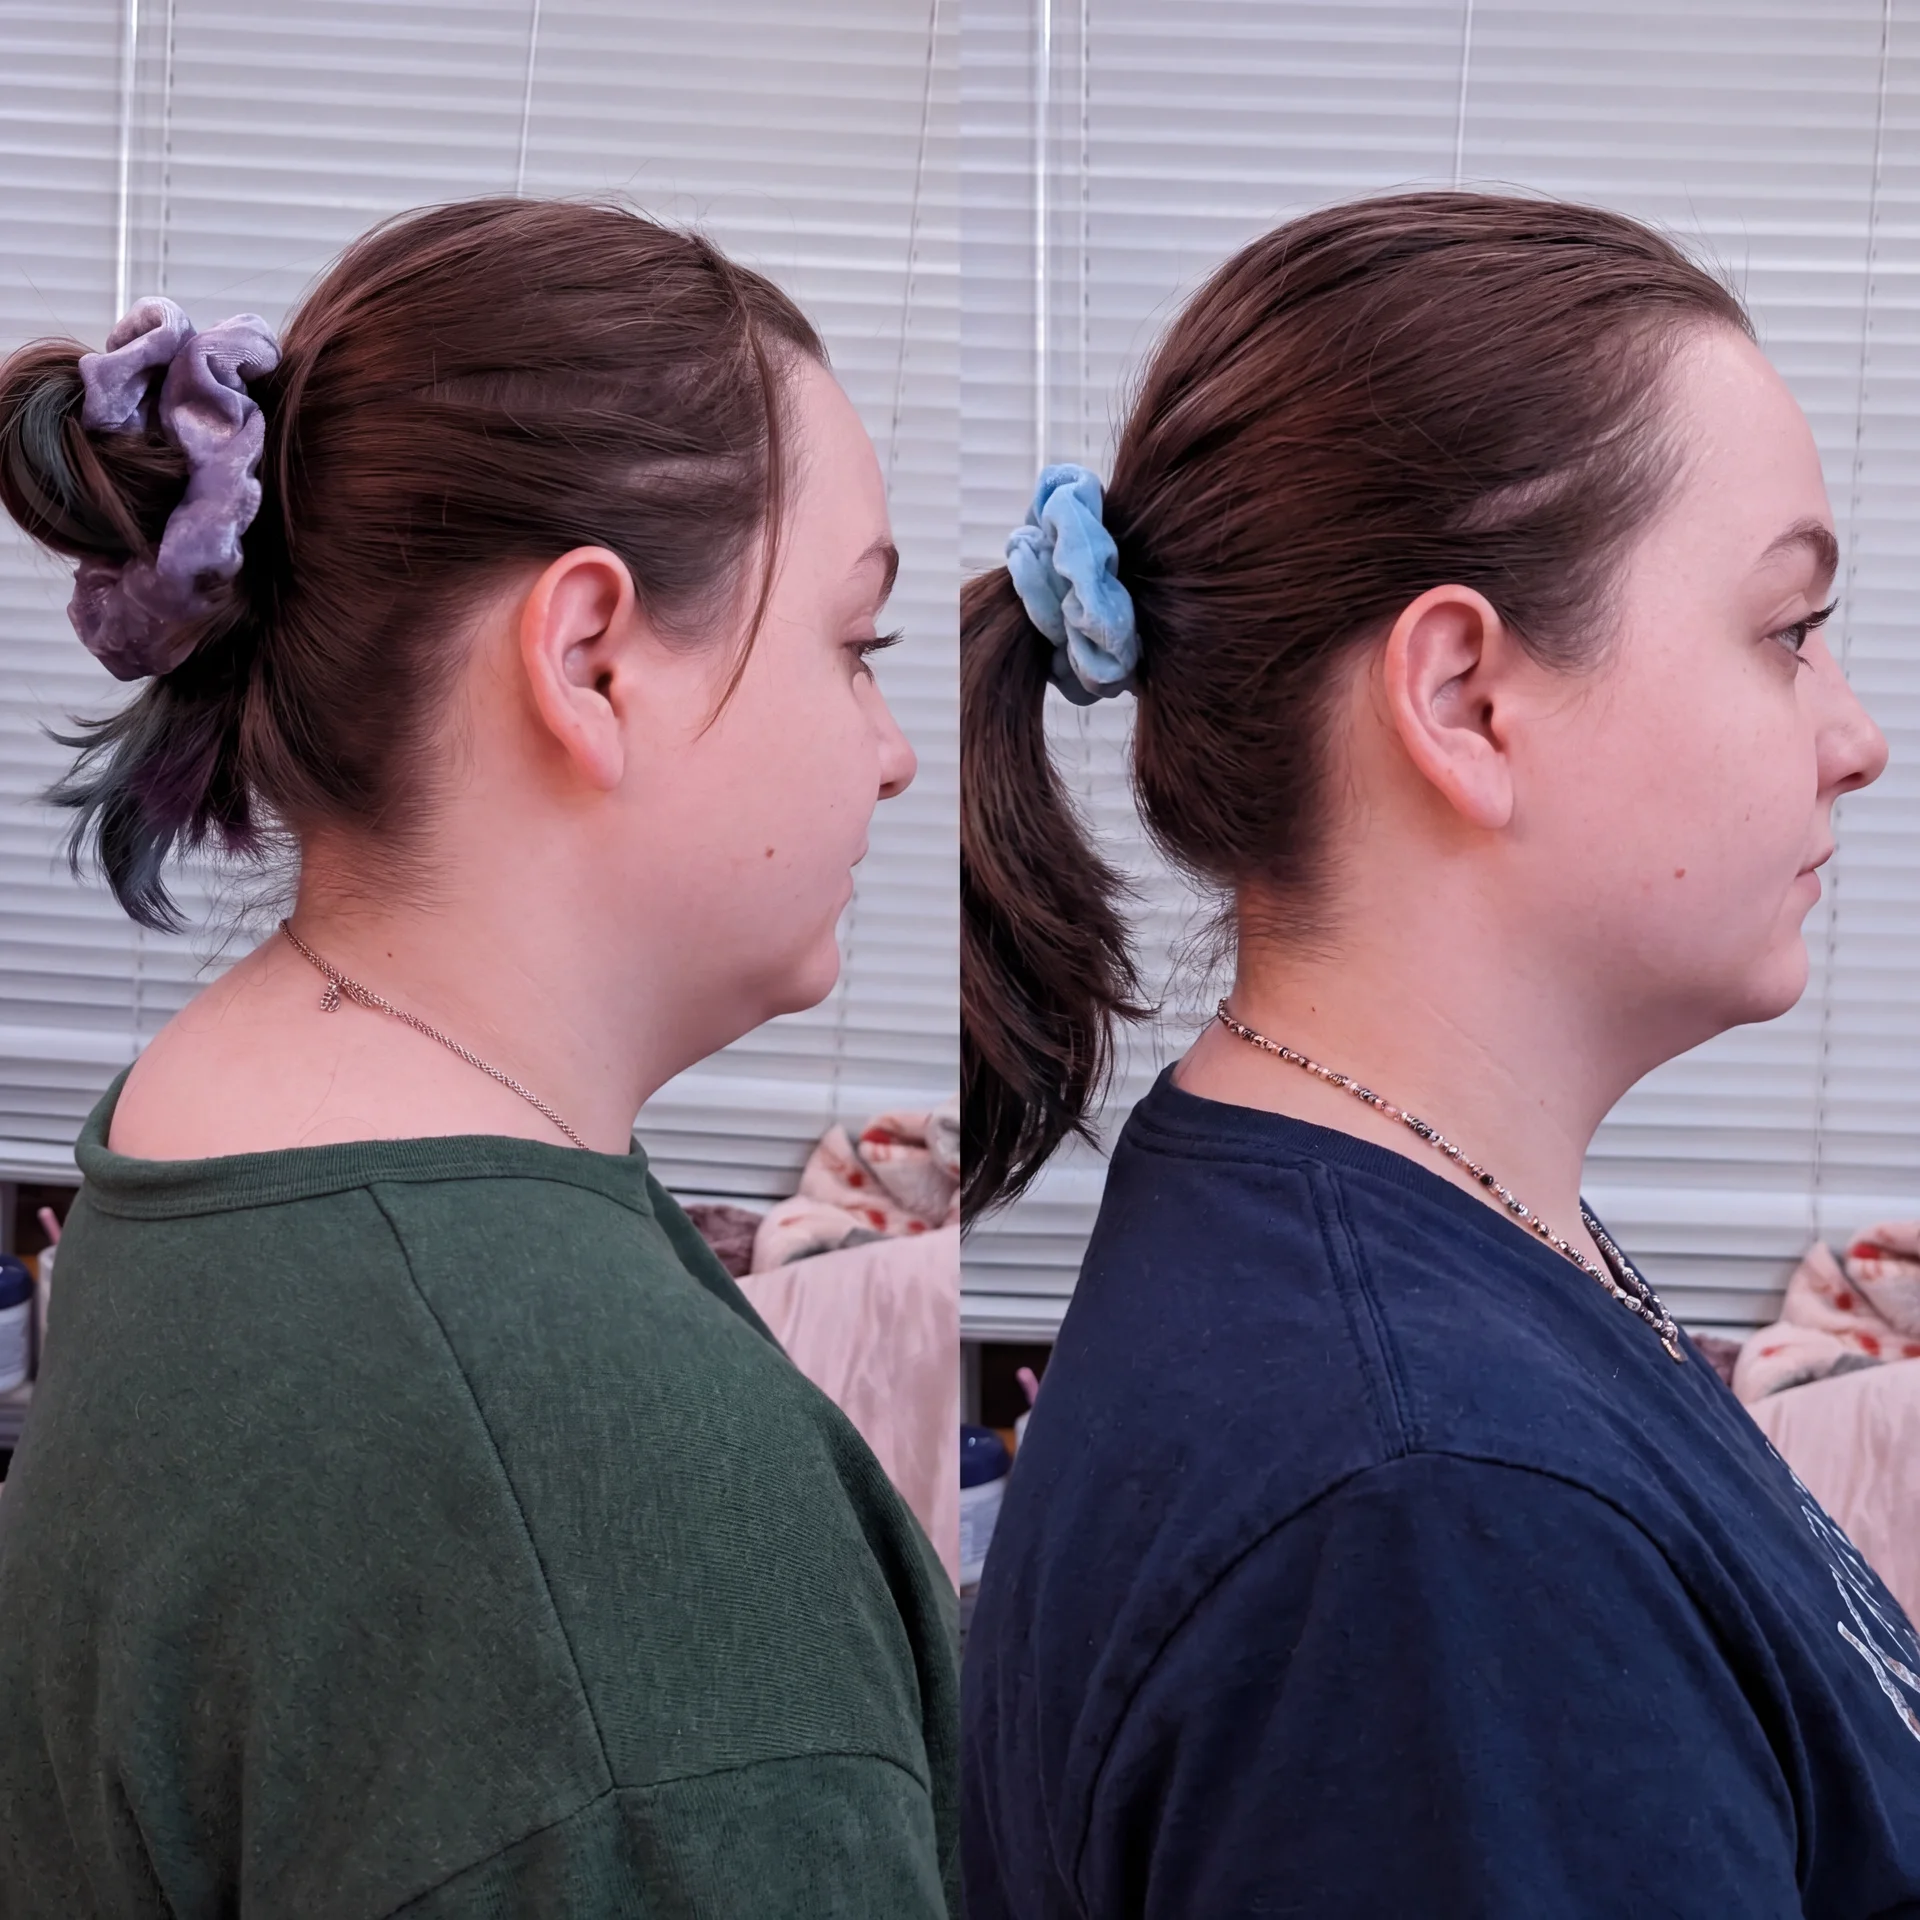
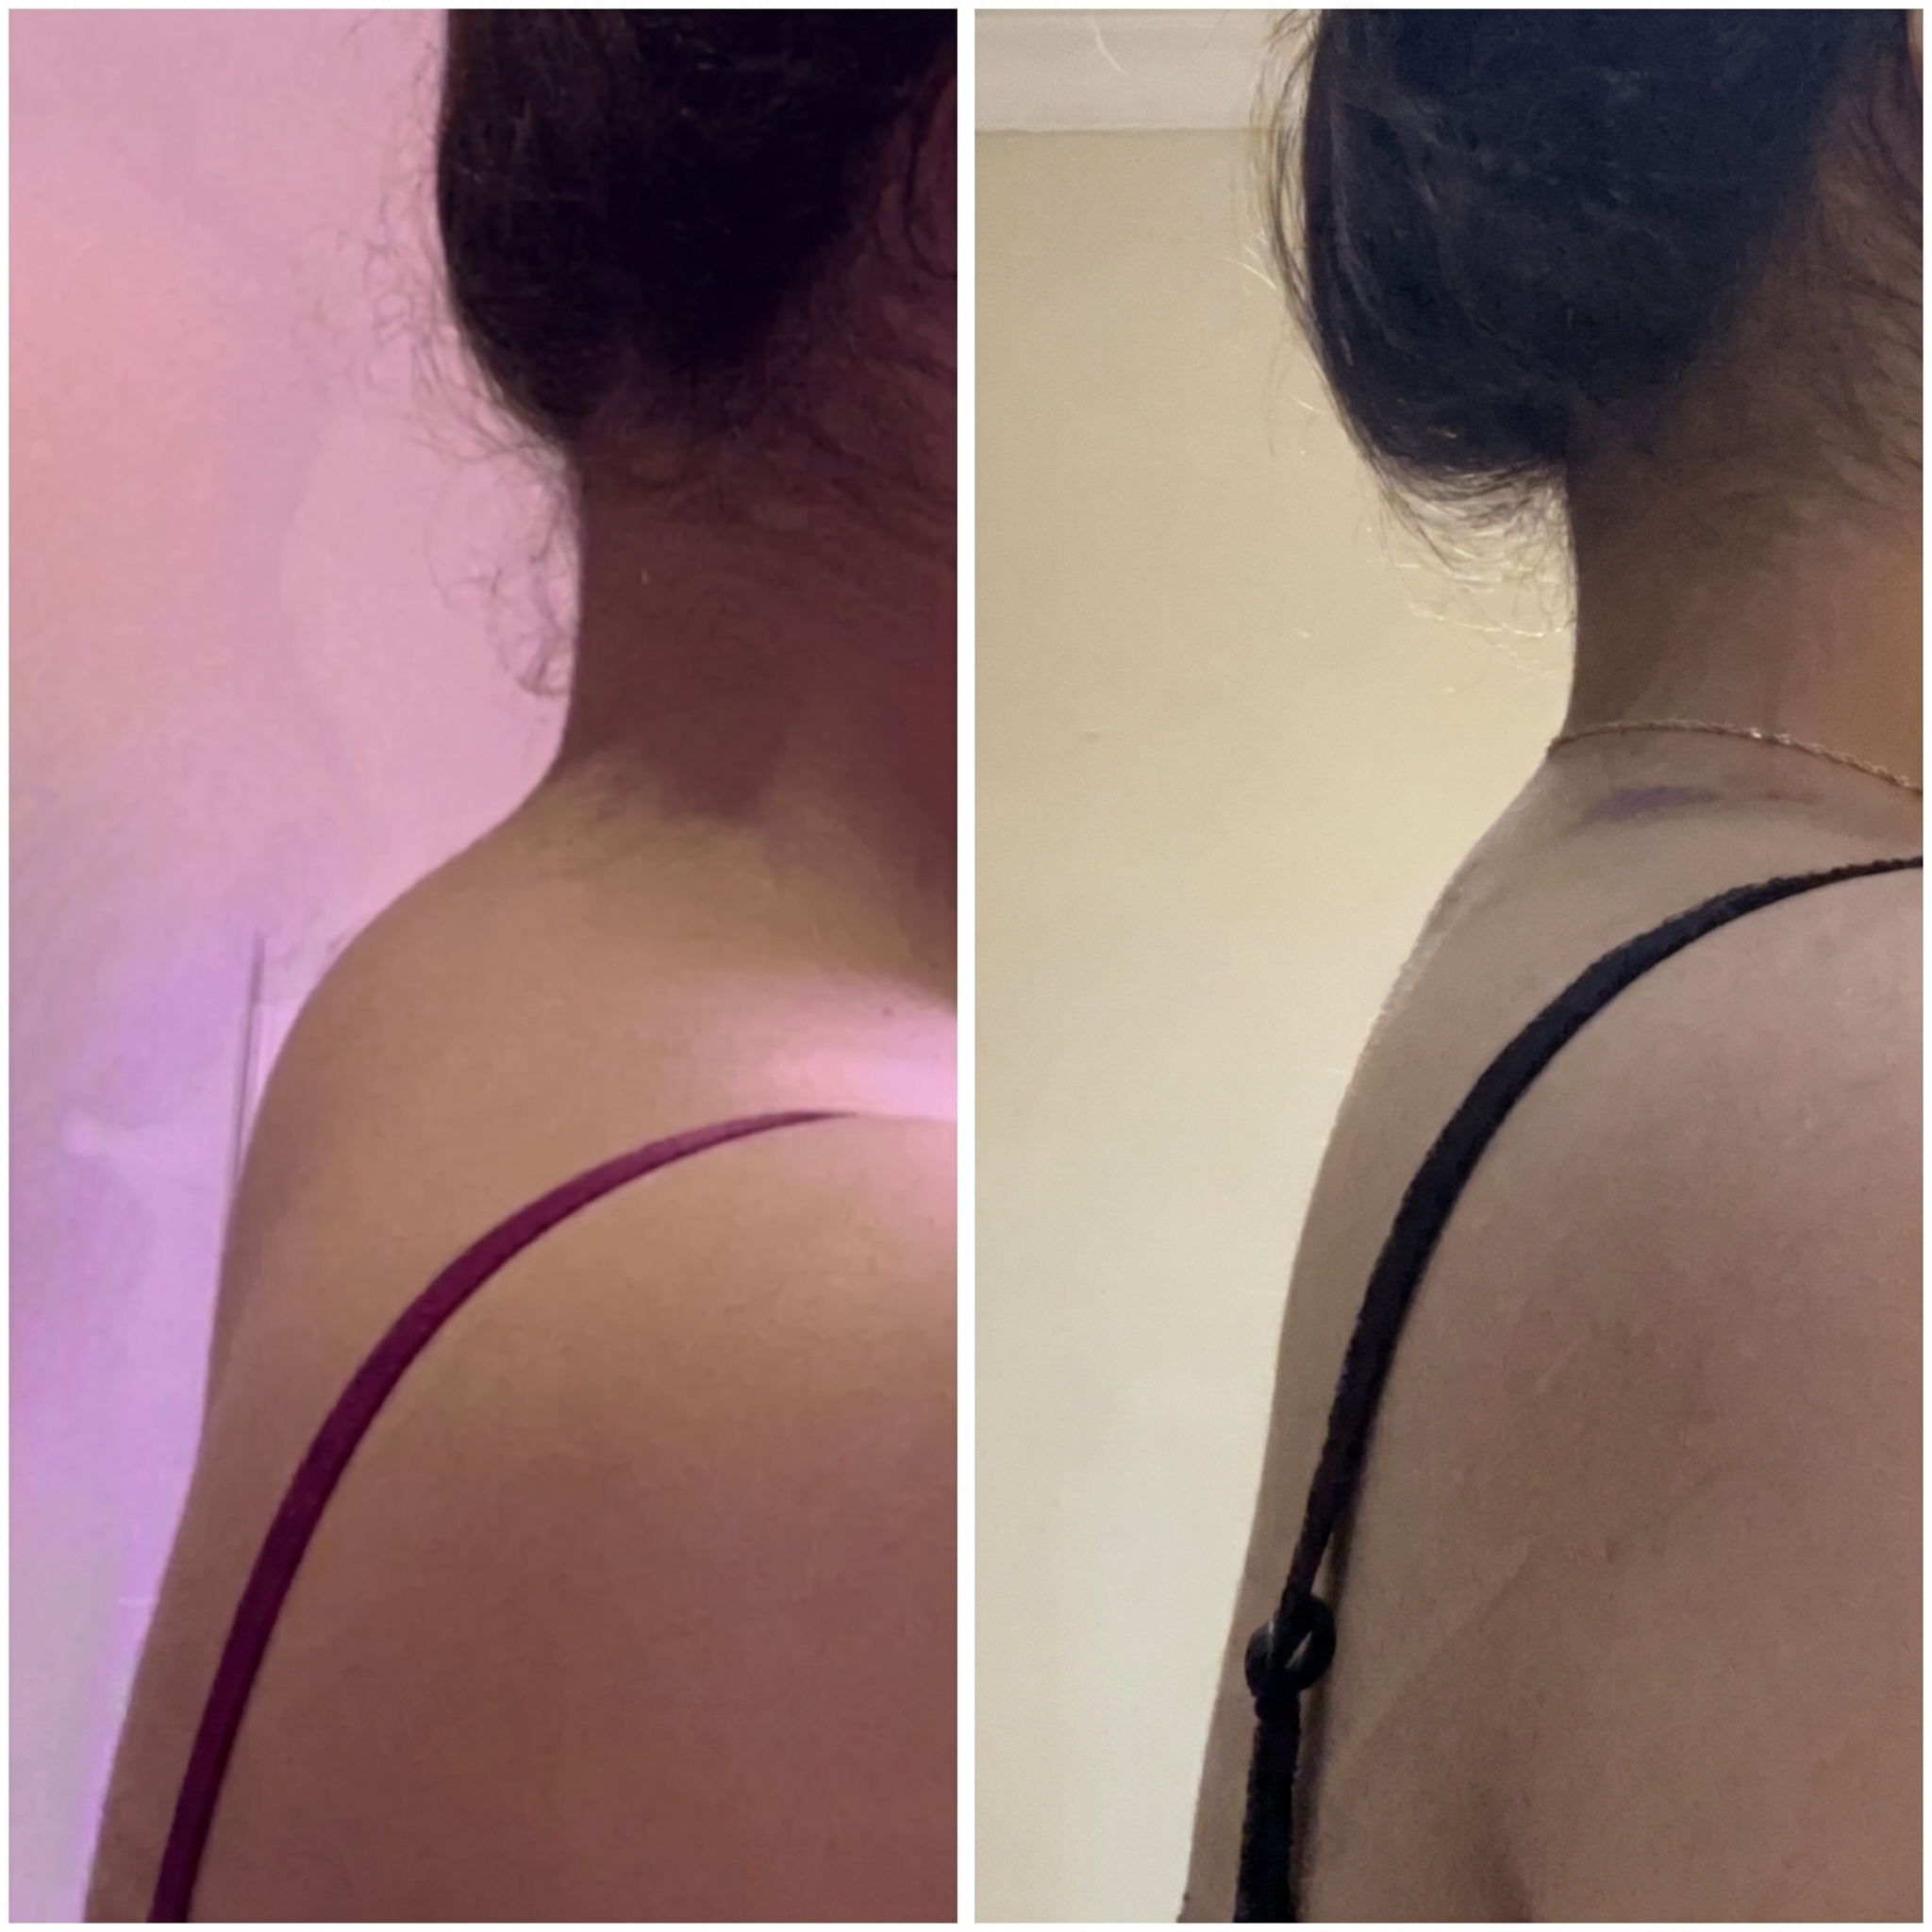
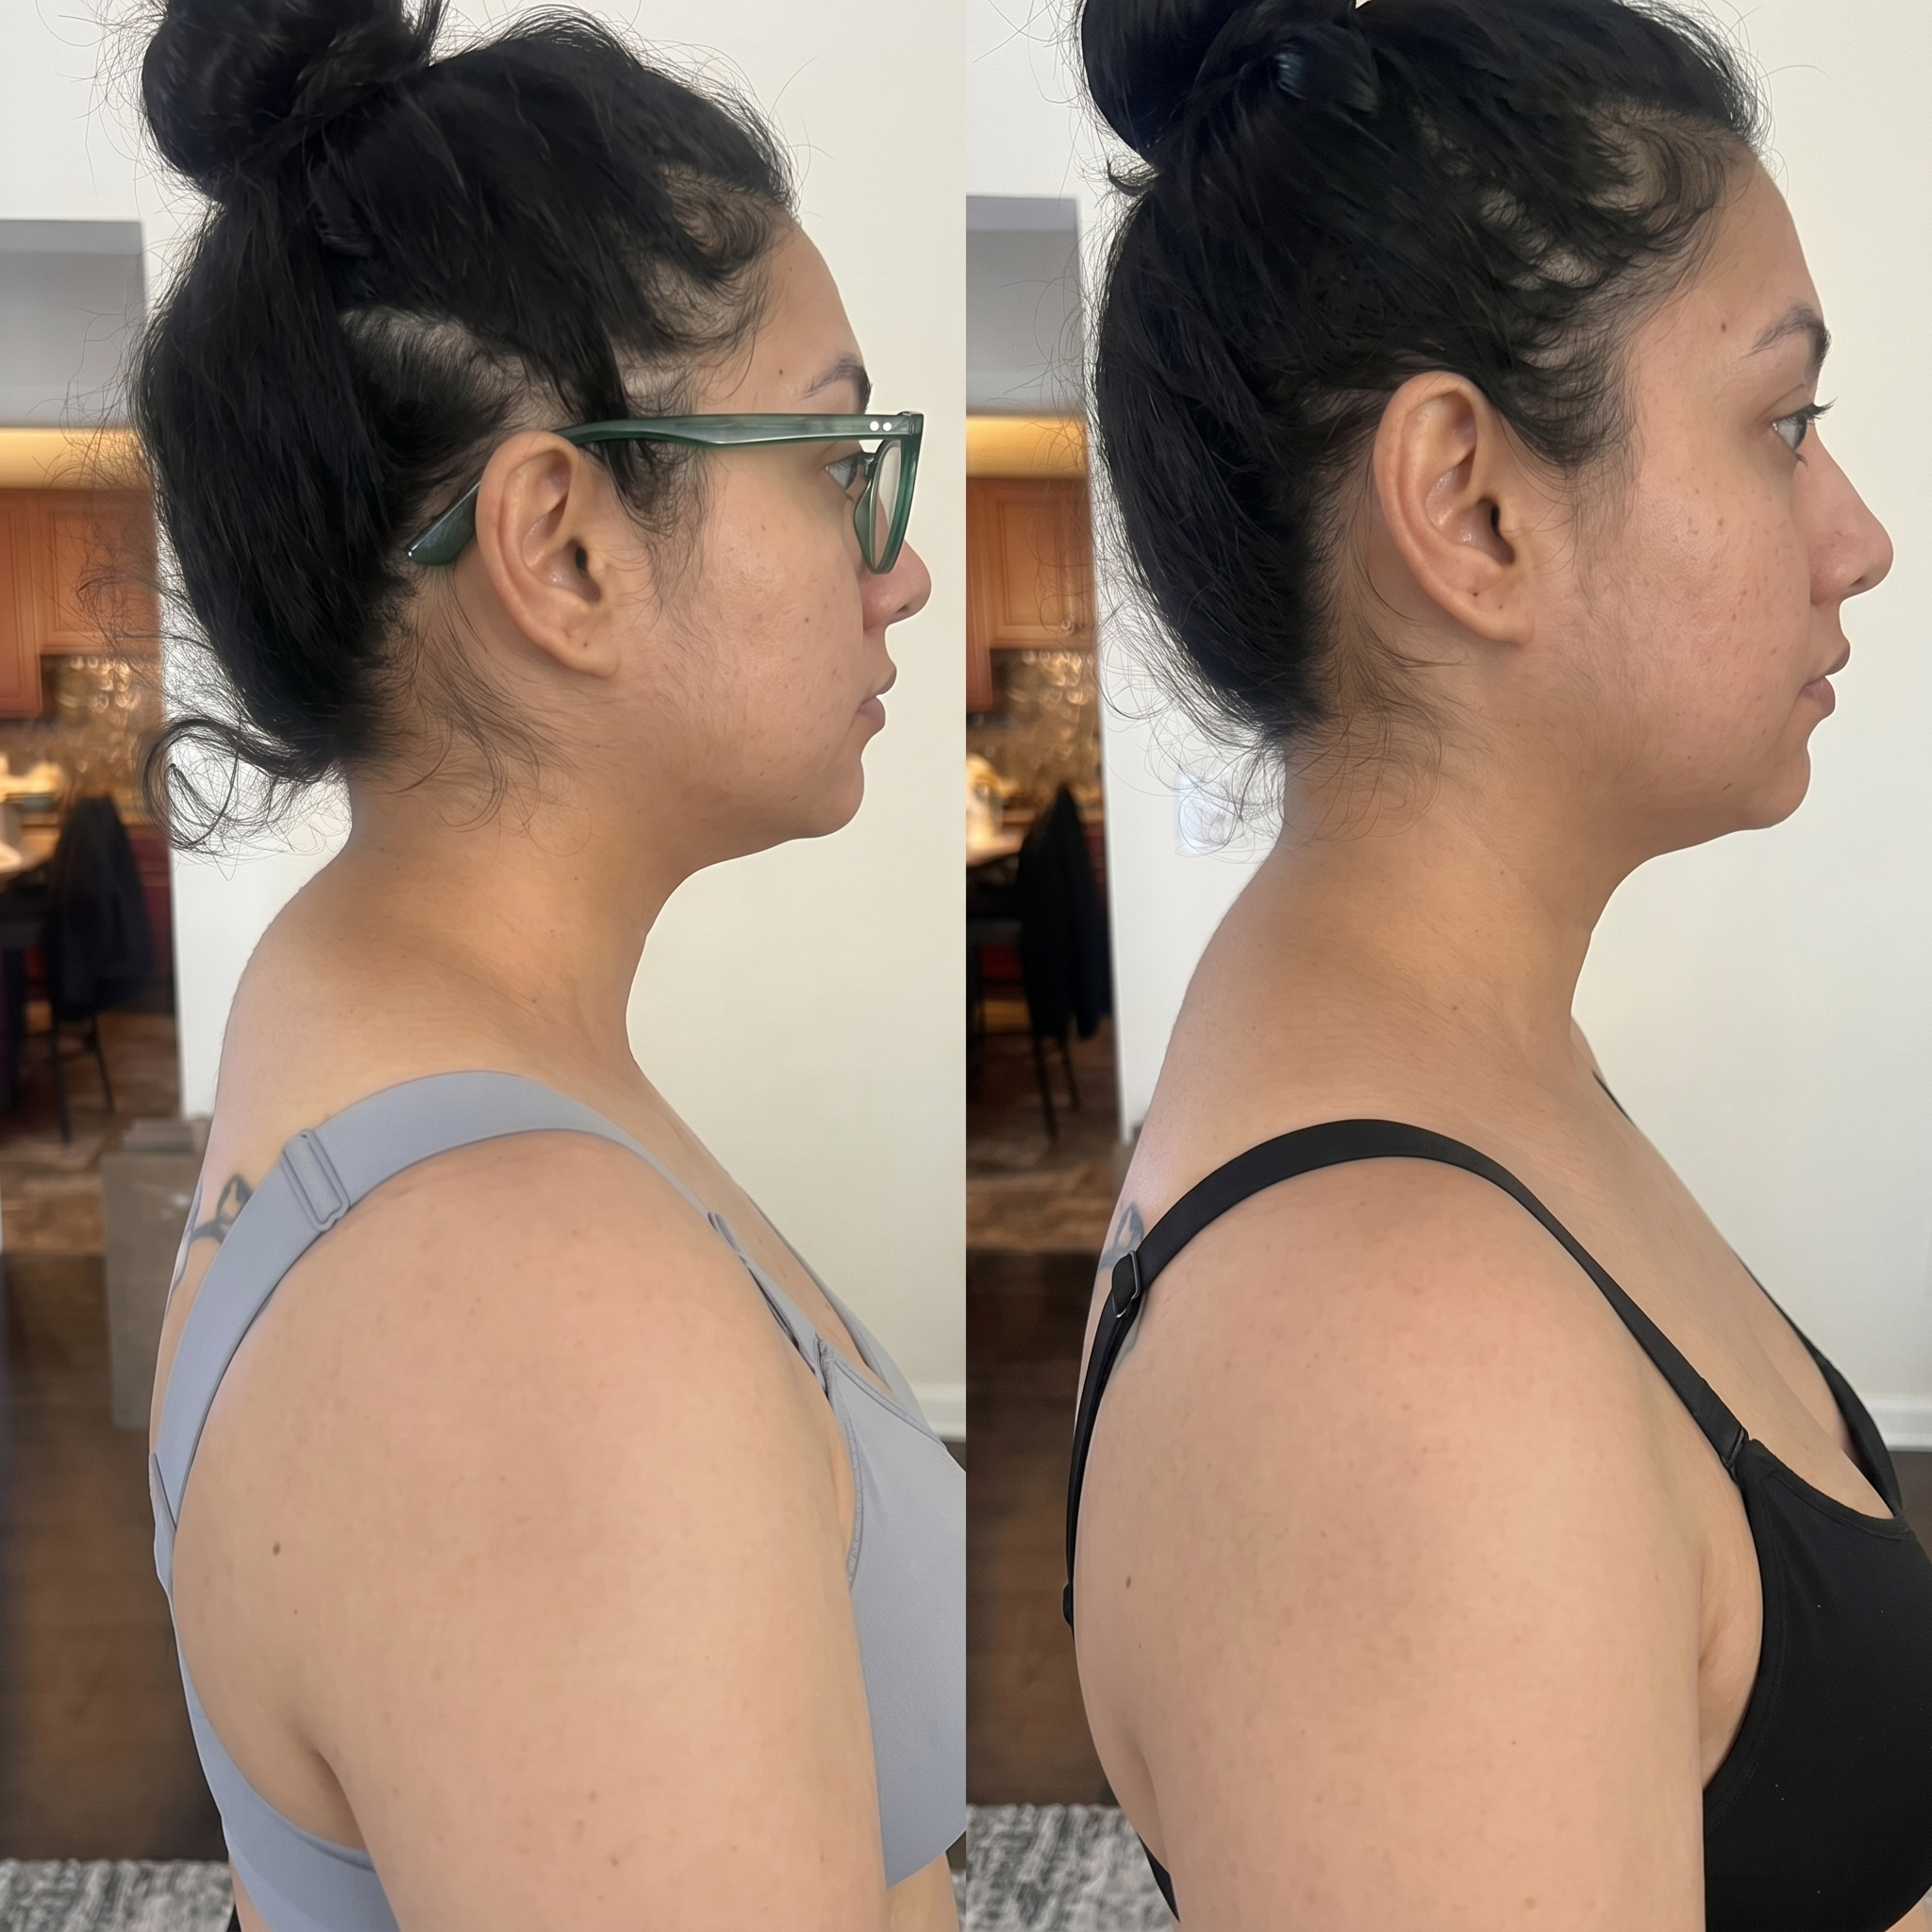
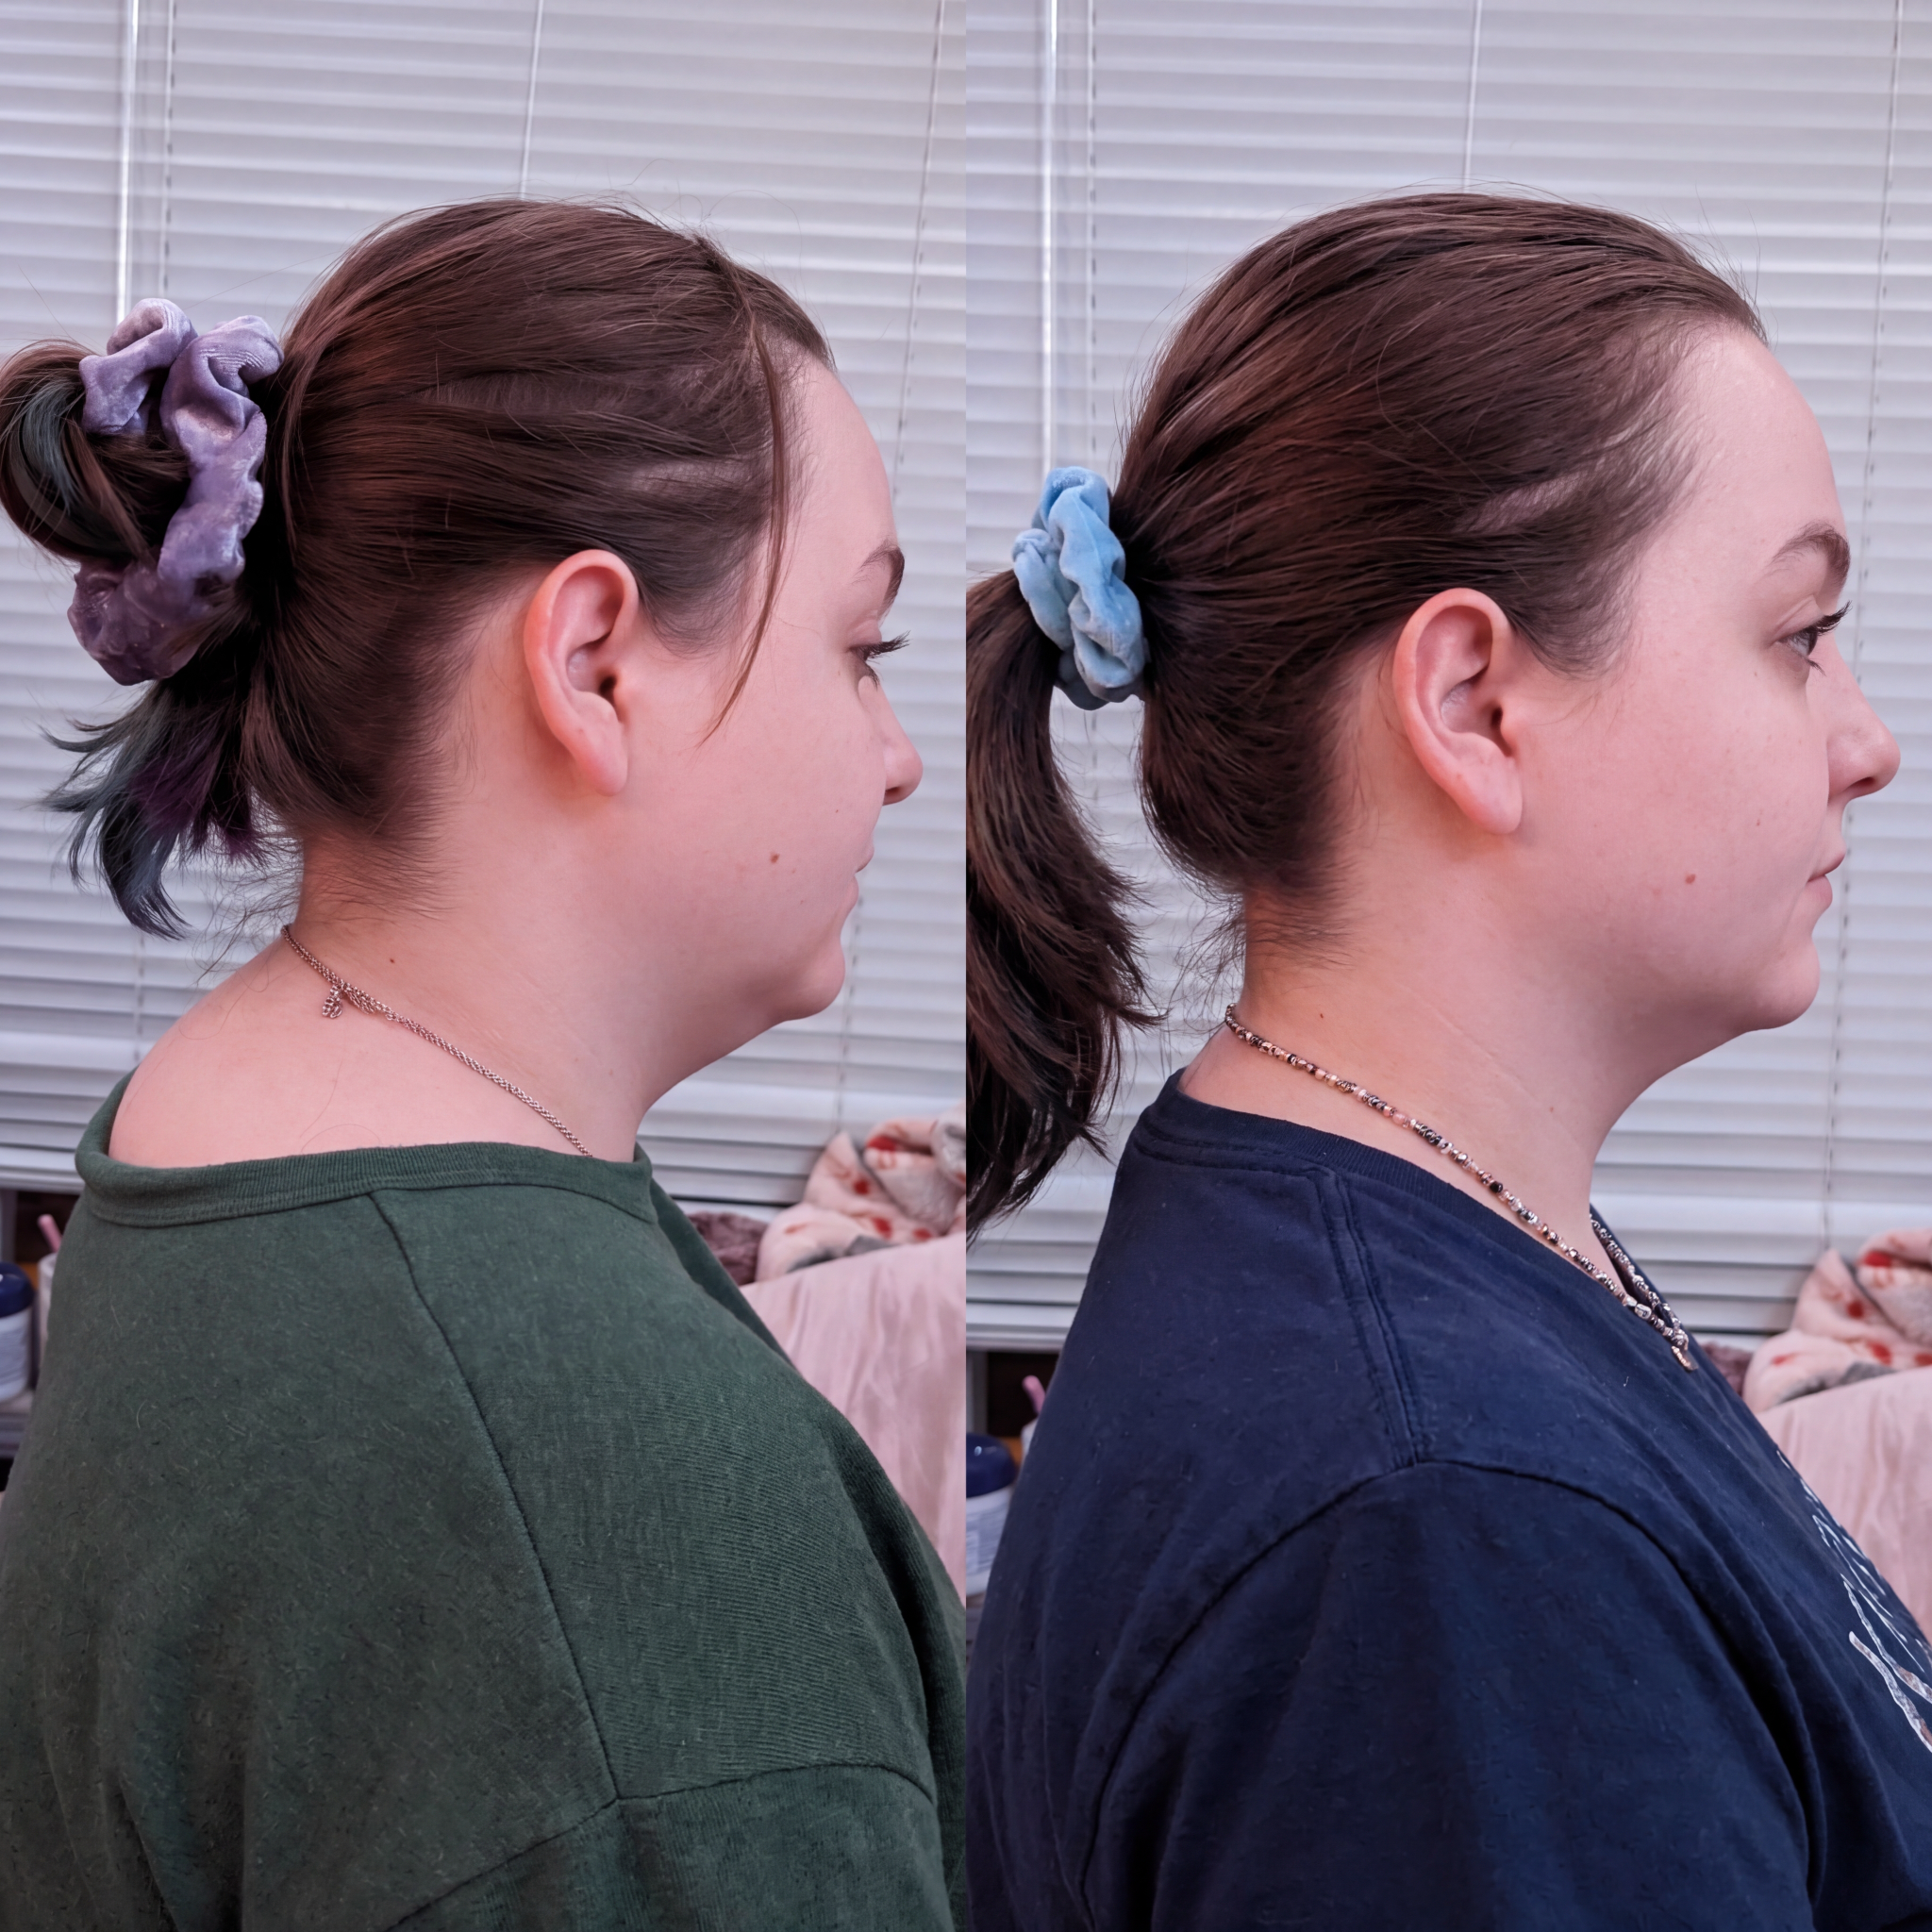
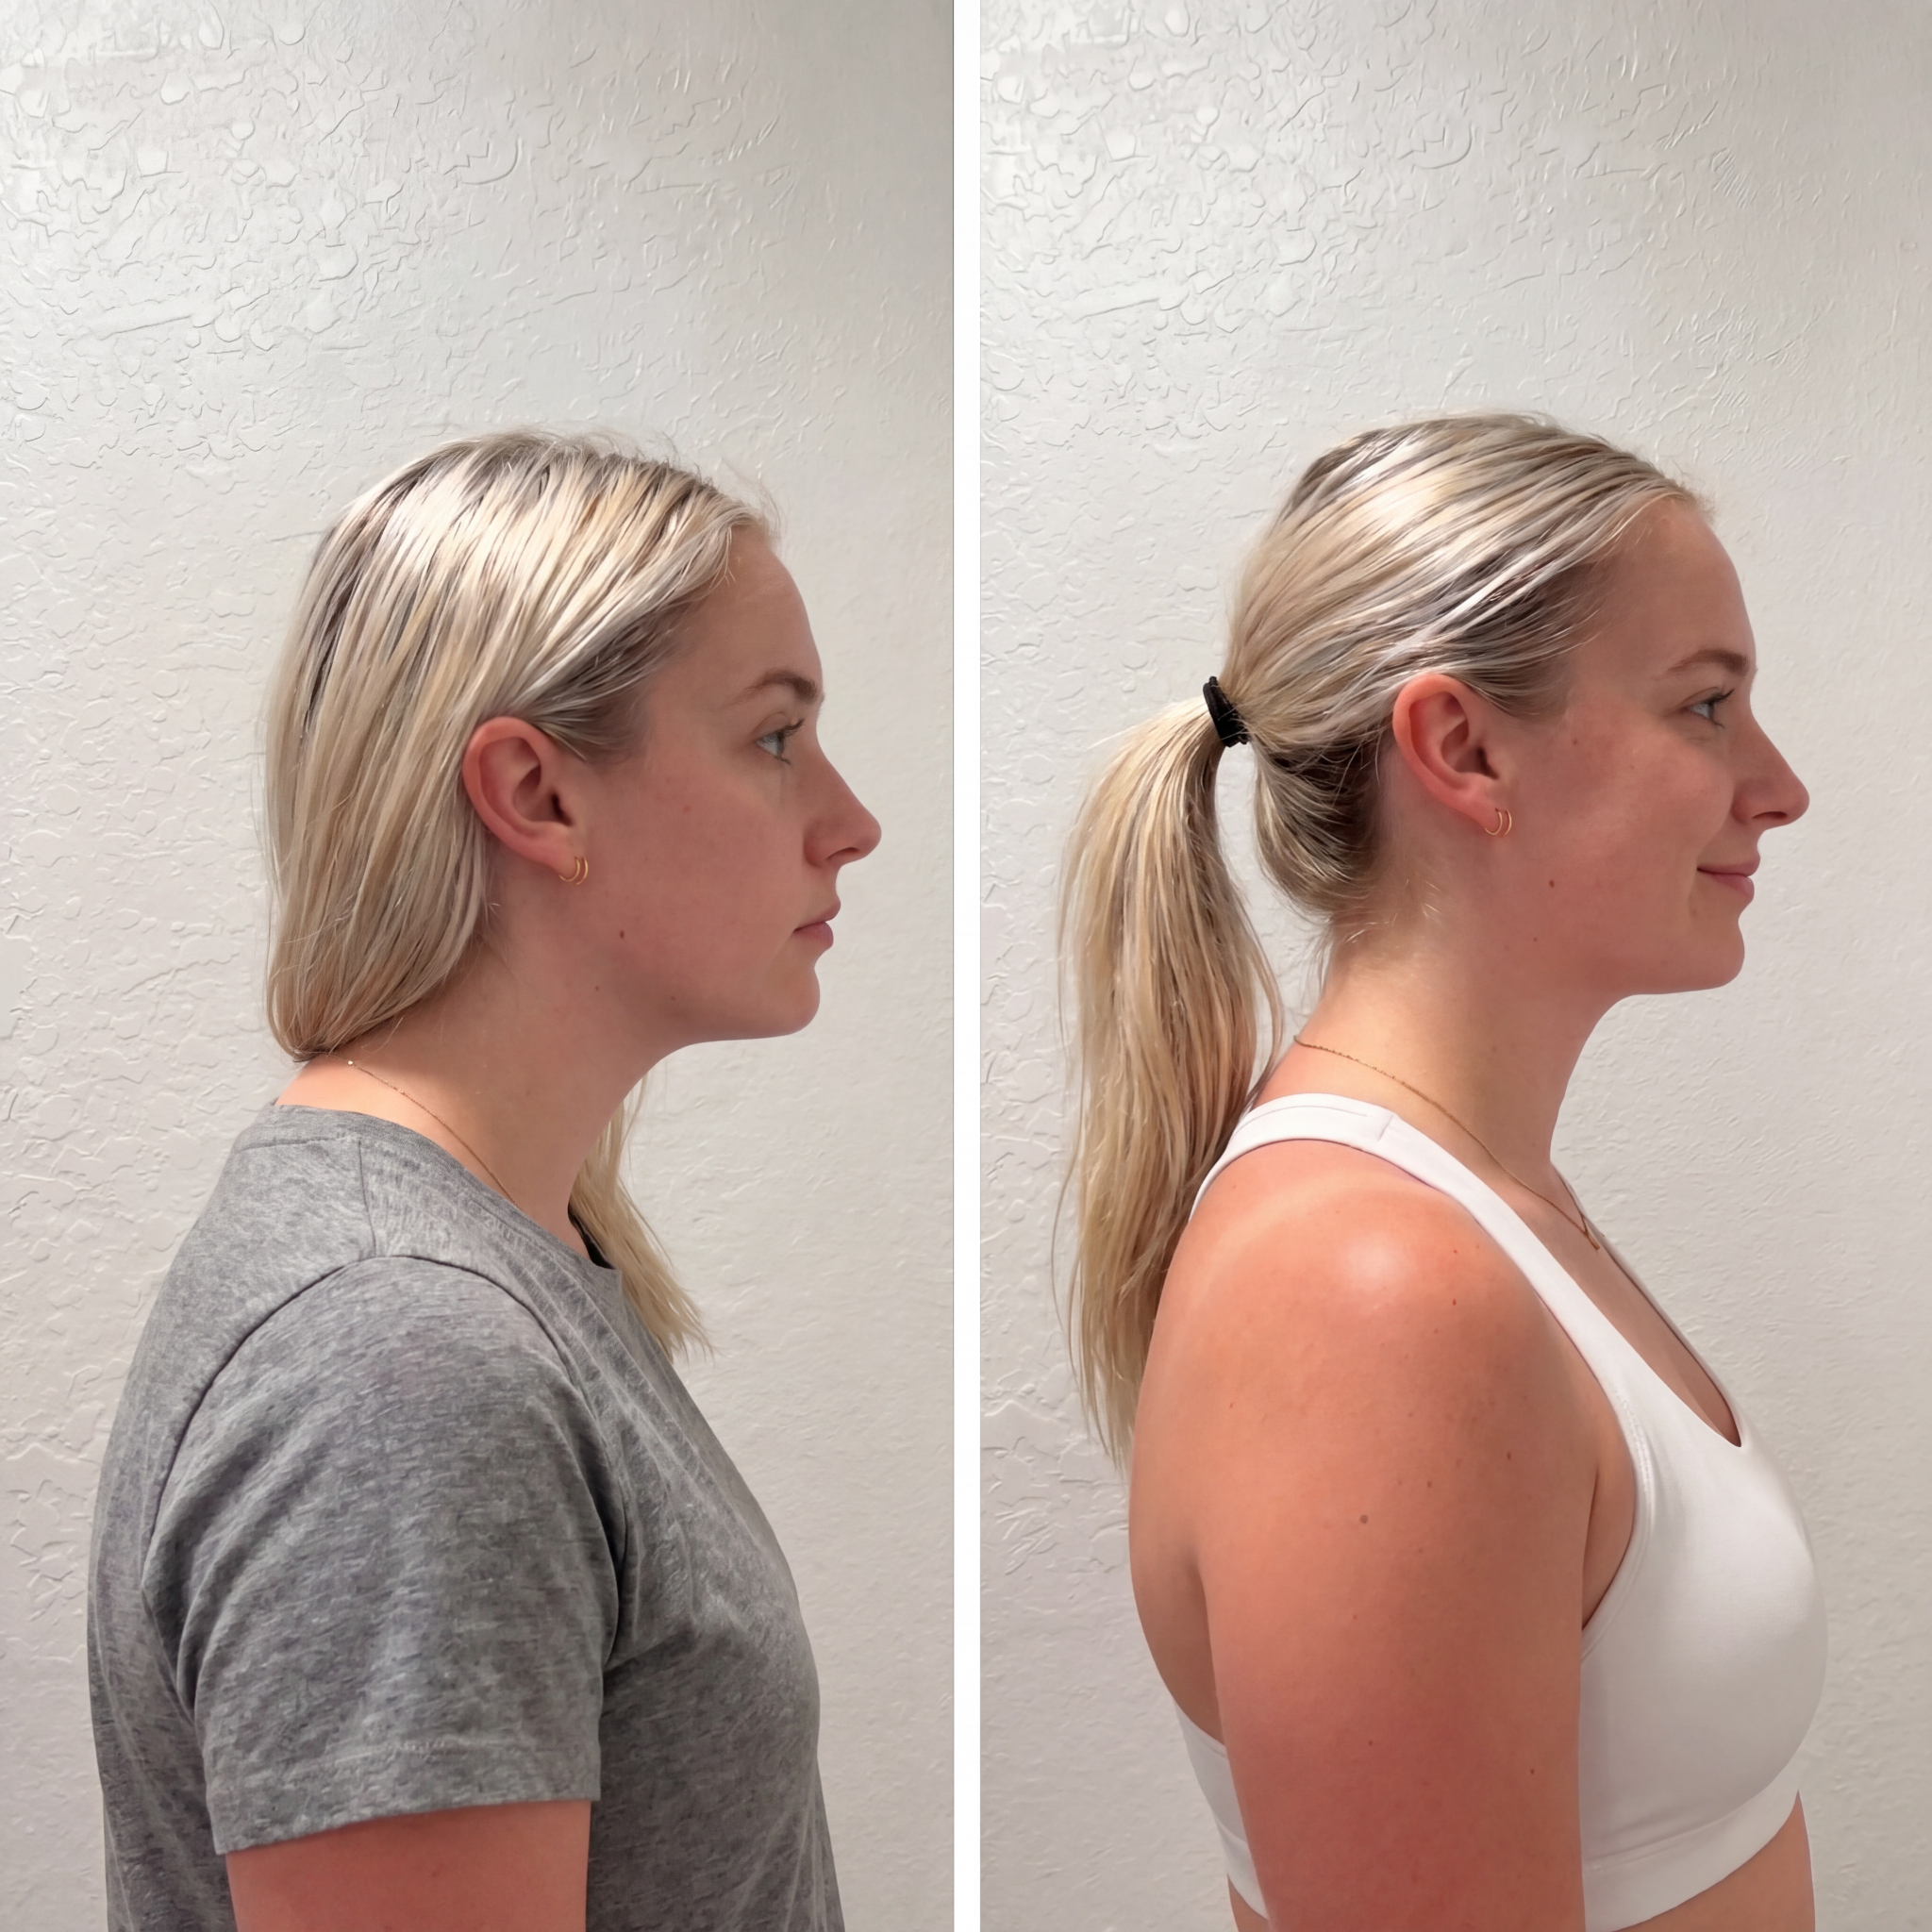
There are two types of Dowager's Hump. One type responds to exercises, chiropractic, and everything your physical therapist prescribes. The other type — the one that keeps coming back no matter what you do — doesn't respond to any of it. And there's a structural reason nobody in American clinical practice is talking about. I know because I spent 19 years treating both types with the same protocol. And I only found out there were two types when my own neck stopped responding to everything I prescribed. My name is Dr. Sarah Chen. Board-certified cervical spine specialist. 22 years at the Mayo Clinic and Stanford Medical Center. Over 8,000 patients. And until last autumn, I had no idea I was failing half of them. Here's what I mean by two types. Type 1 is postural. A woman develops mild rounding at the base of her neck from years of forward head position. The hump is soft, gradual, and responsive. Exercises help. Chiropractic helps. Posture correction helps. Not perfectly, but measurably. This is the type every American clinician is trained to treat. Type 2 is structural. The cervical curve has already collapsed. The connective tissue running across the chest and front of the neck has spent years in a shortened, hardened position and lost its elasticity completely. The small muscles designed to hold the head over the shoulders have gone dormant. This is not a posture habit. It is a mechanical failure at three levels simultaneously. And it was there long before the hump became visible. Type 2 doesn't respond to chin tucks. It doesn't respond to posture correctors. It doesn't respond to chiropractic adjustments, foam rolling, or prescription exercises. Not because those are bad treatments. Because they were designed for Type 1. And Type 2 is a fundamentally different structural event. I didn't learn this distinction in medical school. I didn't learn it in residency. I didn't learn it in 19 years of continuing education. I learned it in September 2023. In London. From a 68-year-old British osteopath named Margaret Holloway. In about 40 minutes. But before I tell you what she taught me, I need to tell you something I've never said publicly. I am Type 2. The hump at the base of my neck had been developing for four years. I'd been treating it myself — the same protocol I prescribed to my patients. Targeted cervical exercises twice daily. Regular chiropractic adjustments. A medical-grade posture corrector worn for hours at a time. Nineteen months of self-treatment. My neck looked the same. Possibly worse. And here's what haunted me: I had other patients on the exact same protocols whose humps were improving. Why was it working for them and not for me? I didn't have an answer. I started wearing my hair down every day and stopped looking at myself in side-profile mirrors. September 2023. The European Spinal Rehabilitation Conference in London. I was the only presenter at the morning coffee break who kept repositioning herself so her back wasn't visible to the room. That's when I saw Margaret Holloway. 68 years old. Head perfectly over her shoulders. No visible hump. No forward head position. Nothing. I introduced myself. I couldn't help asking. She didn't give me a treatment recommendation. She asked me a question. "The patients whose humps improve on your standard protocols — do they have mild rounding that developed gradually over years? Or do they have a pronounced, firm protrusion that has been there for years despite consistent treatment?" I opened my mouth to answer and realized I'd never thought to separate them. She nodded slowly. "That's because American clinical training doesn't separate them. You have one diagnosis: kyphotic posture. One category. One set of protocols. But there are two completely different structural events happening, and only one of them responds to what you're prescribing." She gestured to a quiet corner of the room. "Sit down. I'm going to explain why half your patients improve and the other half don't. And why your own neck hasn't responded. It has nothing to do with your spine being unusual." She drew two columns on a notepad. "Type 1 — Postural Rounding." Margaret explained that in Type 1, the structural damage is limited. The cervical curve has flattened but not reversed. The fascia is tight but not locked. The deep flexors are weak but not dormant. Surface interventions — exercises, chiropractic, corrective bracing — can reach the level where the problem exists. For Type 1, American protocols work. "Type 2 — Structural Collapse." She drew a diagram of a cervical spine. "In Type 2, three things have happened simultaneously. And all three must be addressed at the same time for anything to change. This is why your patients plateau. This is why your own neck hasn't moved in nineteen months. You've been treating one component of a three-component failure." She numbered them. "First. The cervical curve has reversed. You cannot correct a reversed curve with exercises that target the muscles around it. The architecture itself has failed. You need direct, sustained traction at the C7 junction — the exact vertebra where the hump forms — to begin lifting the curve from the inside." "Second. The anterior fascia has locked down. The connective tissue across the front of the neck and chest has hardened into a shortened position. Like a rubber band stretched in one direction for so long it cannot spring back. This is the mechanism that pulls the head forward within hours of every chiropractic adjustment you have ever made. The adjustment decompresses the joint. The fascia contracts it back. You've been doing excellent work on one component while the second component undoes it every time." "Third. The deep cervical flexors have gone dormant. The upper trapezius has compensated. It is chronically exhausted. Exercises can activate the deep flexors temporarily — but without sustained structural correction underneath, the upper traps reassert within days. Your patients feel better after a session. They come back two weeks later exactly where they were." She looked at me. "Your patients who improved? Type 1. Your surface protocols could reach where their problem was. Your patients who didn't? Type 2. All three failures are deeper than anything you've been prescribing. You? Type 2. Nineteen months. Every treatment aimed at the wrong structural level." I asked her how many American clinicians she'd explained this to. "Many. British and European osteopathic research on structural cervical collapse has been published for over a decade. American conferences are largely sponsored by the same companies that sell the equipment your protocols depend on. They don't present research that makes their products irrelevant for half the patient population." I asked her what actually reverses Type 2. She drew three overlapping circles. "Three things. Simultaneously. At the correct structural depth. Miss one, and the other two don't hold." First: Restore the cervical curve with sustained daily traction. Margaret explained that my exercises applied intermittent force — sets of reps, held for seconds. Chiropractic applied manual decompression for minutes, twice a week. Neither delivered the sustained load that a reversed cervical curve requires to begin lifting. The fascia contracts back between sessions. The curve reasserts. You need sustained traction applied directly at C7 — held consistently, daily — not for twenty seconds in a session, not for two minutes in a clinic, but every single day at the anatomical junction where the collapse occurred. "You've been trying to straighten a bridge by adjusting the traffic on it," she said. "The cables have snapped. You need to rebuild the tension from the inside, every day, until the structure remembers where it belongs." Second: Release the anterior fascia under sustained daily pressure at the correct anatomical point. Margaret was precise about this. The anterior fascia does not release under intermittent load. It does not release under passive bracing. It releases under sustained pressure applied at the cervicothoracic junction — the specific anchor point of the anterior chain — held consistently over time. "Your posture corrector holds your shoulders back while you wear it," she said. "The fascia ignores it entirely. The moment you remove the brace, the fascia walks your head right back forward. You need to change what the fascia is doing — not override it temporarily." Third: Reactivate the deep cervical flexors in correct structural alignment. "You can activate the deep flexors with exercises," Margaret said. "But if the cervical curve is reversed and the fascia is pulling the head forward, the deep flexors are being asked to hold the head over the shoulders from the wrong position. They cannot do it. Correct the curve first. Release the fascia first. Then the flexors reactivate into the right position — and hold it, because the structure finally supports them." All three. Simultaneously. Sustained. Daily. "That is what reverses Type 2," she said. "Surface interventions cannot. Not because they're bad science. Because they're aimed at a level where the structural failure doesn't exist." I sat in that conference room for a long time after Margaret left. I thought about the patients I'd been seeing for years with pronounced, persistent Dowager's Humps. The women who'd tried everything. Who'd bought ten posture correctors. Who'd lost 40 or 50 pounds and watched the hump remain. Who'd spent thousands on chiropractic. I'd told them to be patient. To be more consistent. To keep trying. I was telling Type 2 women to keep doing Type 1 treatments. Harder. Longer. More expensive. And it was never going to work. I flew home the next morning. I pulled every persistent Dowager's Hump file from my records. 47 patients over five years who had been under consistent treatment for more than six months. 5 had achieved meaningful structural improvement. 42 had not. My Type 1 patients showed meaningful improvement in 71% of cases on the same protocols. Two types. Same diagnosis in my charts. Completely different outcomes. Because I had never been taught to ask the question Margaret opened with: is this structural, or is it postural? I started the three-component protocol on myself that week. I found the Cervaria — a cervical traction device engineered to deliver all three requirements Margaret had described, simultaneously, in a single passive daily session. The raised arch applies sustained traction directly at C7. The pressure groove targets the cervicothoracic junction where the anterior fascial chain anchors. The base positions the deep cervical flexors in correct alignment so they can reactivate over time. Ten minutes lying down. All three components. Every day. Week 2. A colleague stopped me in the hallway and said my posture looked different. I hadn't told anyone I was trying something new. Week 3. I turned sideways in the bathroom mirror. The same angle I'd been avoiding for years. The hump was smaller. Not gone. But visibly, measurably smaller. I took the photo three times because I didn't trust the first one. Week 6. I attended a department meeting and forgot to position my back away from the door. For four years I had automatically seated myself so nobody could walk behind me. That Tuesday I sat in the first available chair. I only noticed it on the drive home. Week 10. I submitted a clinical assessment to a colleague who hadn't seen me in six months. She documented the cervical curve, the C7 protrusion, the head position. She didn't know what I'd been doing. Her report used the word "significant." Type 2. Nineteen months of failed protocols. Reversed in ten weeks. I called my patients. Patricia, 58. Three years of treatment. $14,000 spent. Hump unchanged. Week 8: "My hairdresser stopped mid-appointment and asked what I had changed. She said my neck looked completely different. I don't know what to say except I'm angry it took this long." Margaret, 61. Fourteen months of my standard protocol. I'd had her at the beginning of Type 2 and spent her most responsive window on treatments that couldn't reach where the failure was. Week 9: "I keep running my hand across the back of my neck. It feels different. Like something that was stuck there for years has started to move." She'd spent $4,200 on surface treatments. The protocol that actually worked cost $49. Karen, 54. Eleven posture correctors. Every one in a drawer. Week 11. She walked into a follow-up wearing her hair up. First time I'd seen her without her hair down since she started coming to see me. She didn't mention it. Just sat down and started talking. I need to be honest about why I didn't know any of this. American clinical training runs through equipment-sponsored continuing education. The companies that make adjustment tables, decompression machines, and therapeutic devices fund the conferences and protocols we are taught. These tools work for Type 1. They are legitimate Type 1 treatments. But there is no profit in telling a clinician: "Half your persistent Dowager's Hump patients have a condition your equipment wasn't designed for. They need a $49 home traction device that resolves in ten weeks." So the conversation doesn't happen. And American clinicians keep prescribing Type 1 protocols to Type 2 patients. Not out of malice. Out of training that was never taught the distinction. Margaret Holloway didn't have equipment sponsors shaping what she could recommend. Thirty-five years of osteopathic practice in London. She could follow the biology wherever it led. How to know which type you have. Press on the hump with your thumb. If it feels soft, slightly moveable — you may be Type 1. Standard treatments may reach where your problem is. If it feels firm, bony, and fixed — you are likely Type 2. The reversed cervical curve, the locked anterior fascia, the dormant deep flexors. Surface treatments are aimed at a level where your structural failure doesn't exist. The Cervaria addresses all three simultaneously. Ten minutes a day. Lying down. Passive. 30-day money-back guarantee. Check availability here. — Dr. Sarah Chen, MD, FAAOS Cervical Spine Specialist, 22 years Mayo Clinic and Stanford Medical Center P.S. — Patricia called me last month. She said: "I spent three years thinking my spine was broken. Turns out the treatment was broken. I was just never the right type for it." She was right. And nobody had ever told her there were types. P.P.S. — Margaret told me: "If someone had explained this to me when I first came to you, I'd have spent $49 instead of $4,200 and gotten my neck back a year earlier." I didn't have anything to say to that. She was right too.
$800 worth of failed products in the trash
Spine & Wellness Today ■ Home > Health > Posture & Spine Top Cervical Specialist: "This Is the Fastest Way to Reverse a Neck Hump for Good" Former chronic sufferer exposes the $4.8 billion posture correction industry conspiracy — and the 10-minute trick that reversed 11 years of Do...
LEARN MORELike this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.