
 The Thyroid Journal
 Facebook ad: “The Truth About Levothyroxine & Weight Gain”
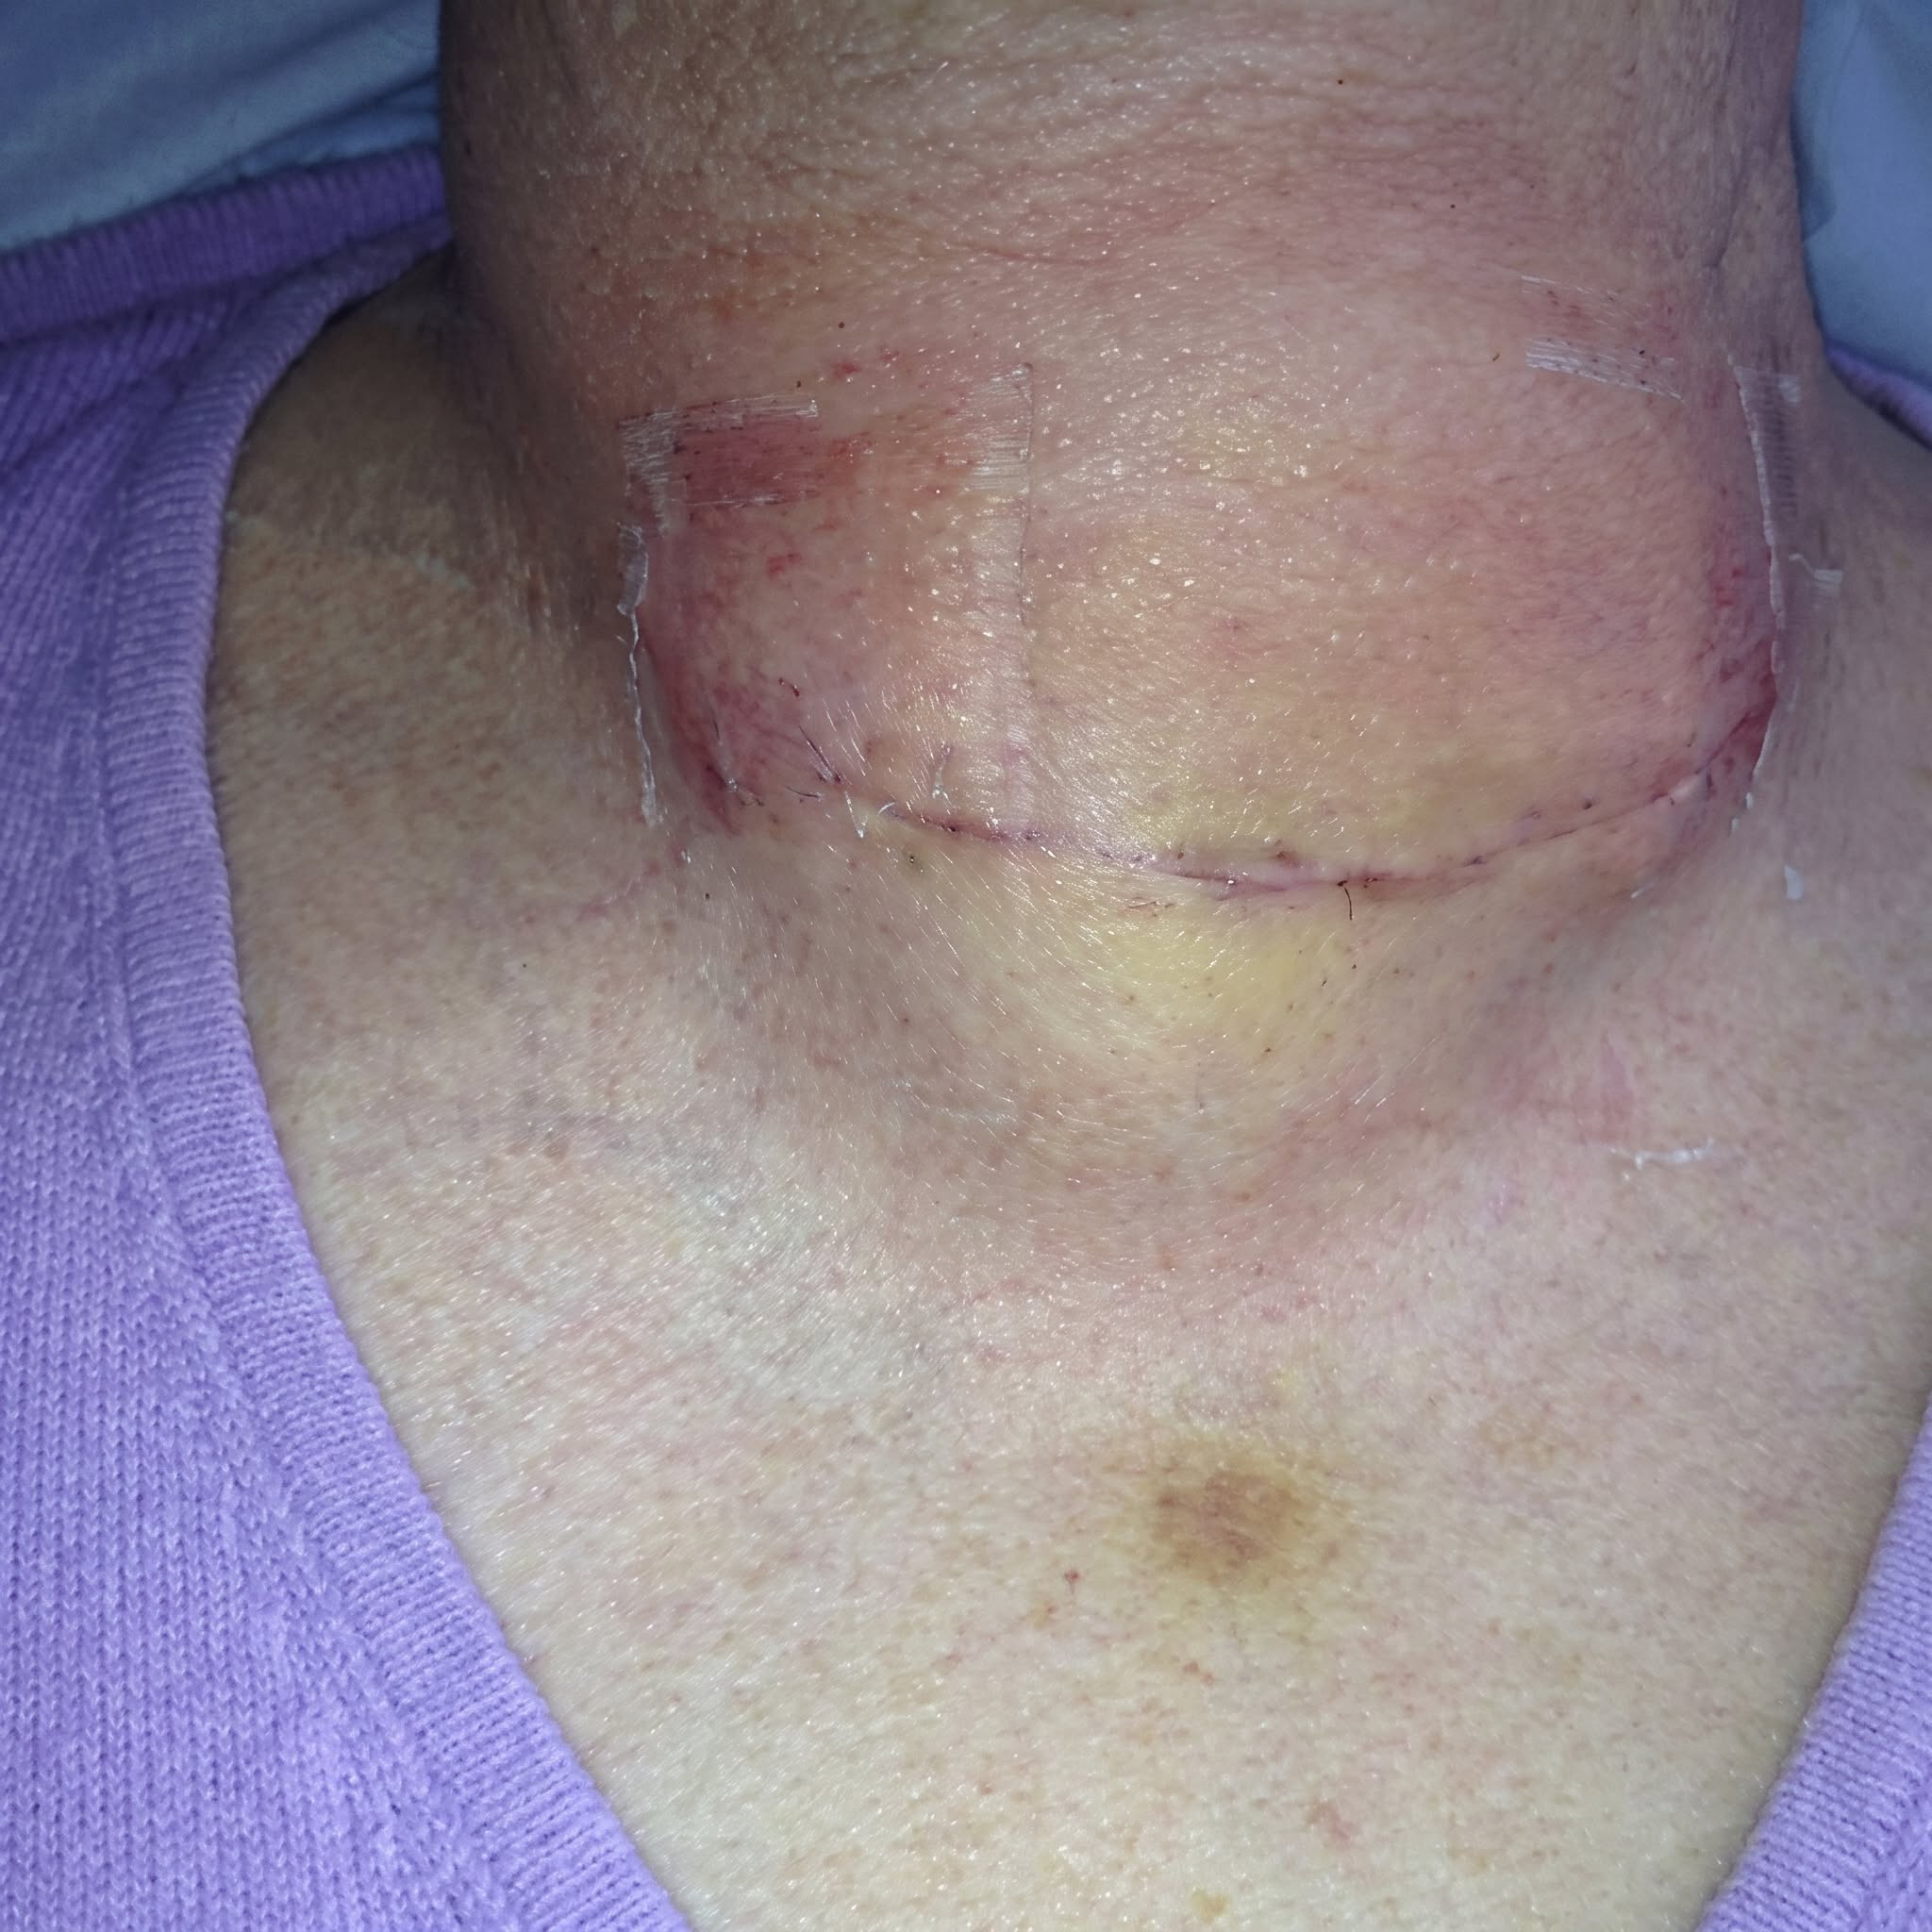
Ran for 3 days, from September 14 to September 17, 2026, the last day Crush saw it.
Run by The Thyroid Journal on Facebook. Crush is not the advertiser and does not verify its claims. See this ad in Meta's Ad Library(opens in a new tab)
Want an ad like this for your product?
Crush makes new ad images for your product from this ad: your logo, your product photo, your offer.
Trials from $19.95 USD, then $79.95 USD a month. Cancel anytime.
About this ad
- Meta Ad Library ID
- 1021398674239875
- Platforms
- Facebook, Instagram, Audience Network, WhatsApp and Threads
- Relaunches
- 0
Ad text
Levothyroxine keeps your TSH in perfect range, but the weight keeps climbing. Your blood pressure creeps higher every year. And now your doctor is mentioning a statin. If your weight, blood pressure, and cholesterol are all moving in the wrong direction on levothyroxine despite doing everything right — here's what's actually connecting all three and what I give my patients instead. For THREE YEARS my sister Laura watched her weight climb on levothyroxine. And then her cardiovascular markers followed it. She was diagnosed with Hashimoto's at 38. Put on levothyroxine immediately. The doctor told her the medication would handle it. Within the first year, she gained over a stone. On medication. Eating less than she ever had. By year two, she was tracking 1,200 calories on MyFitnessPal. Every single bite. She'd trained four times a week for eight months. The scale went up anyway. And then her doctor started watching her blood pressure. 134 over 84. Up from 118 over 76 at diagnosis. Borderline, he said. We'll keep an eye on it. By year three, her cholesterol panel told the same story. LDL 168. Up from 141 two years earlier. Triglycerides elevated. HDL moving in the wrong direction. She noticed her heart pounding climbing stairs she used to take without thinking. She blamed it on the weight. Her doctor looked at the full picture — climbing weight, climbing blood pressure, climbing cholesterol — and reached for his prescription pad. Her TSH was 2.3. Perfect range. Optimal. Her endocrinologist looked at that number every six months and told her everything looked fine. She was gaining weight on twelve hundred calories while her blood pressure and cholesterol quietly worsened, and everything looked fine. And every single doctor told her the same thing. "Your TSH is optimal. The medication is working." "Your blood pressure is borderline. We'll watch it." "Your cholesterol is trending in the wrong direction. Diet and exercise, then we'll talk statins." One of them — and this makes me want to put my fist through a wall — presented three separate solutions for three separate problems. Levothyroxine for the TSH. A statin for the cholesterol. A blood pressure medication for the pressure. Managed individually. None of them connected. None of them aimed at what was running all three. She went through four doctors in three years. Not one — NOT ONE — ever asked why a woman with an optimal TSH was gaining weight AND watching her blood pressure rise AND watching her cholesterol worsen — all three in parallel, all three unresponsive to everything she tried. So here's what they kept telling her to do. And I need you to pay attention because you've probably tried all of this too. Selenium for thyroid conversion — six months — antibodies dipped slightly. Weight kept climbing. Blood pressure unchanged. Cholesterol unchanged. Low-glycaemic diet — six months, properly done — lost a couple of pounds that came right back. Cardiovascular markers continued worsening. The AIP protocol — four months fully committed — weight, blood pressure, cholesterol all moving in the same direction regardless. Magnesium and omega-3 specifically targeting the cardiovascular markers — eight months — LDL continued climbing. Blood pressure continued climbing. The £60-a-month thyroid support formulas — iodine, glandular extracts, metabolism boosters — nothing on the scales, nothing on the blood pressure monitor, nothing on the cholesterol panel. Between the supplements, the private specialist appointments, the nutritionist — she'd spent over £3,500 in three years. Still gaining. Blood pressure still rising. Cholesterol still rising. Heart still pounding on stairs. Doctor now saying statin at every appointment. TSH optimal at every appointment. At this point I'm not frustrated anymore. I'm angry. Because I'm watching my sister — following every instruction, spending thousands, restricting every calorie — get worse across every single marker while her doctors prepare to add more medications to a pile that was already failing her. Managing. Every. Number. Separately. Not asking why a woman with an optimal TSH is simultaneously gaining weight AND watching her blood pressure climb AND watching her cholesterol worsen — all three together, all three in parallel, all three completely unresponsive to the treatments aimed at each. And that's when I started asking the questions nobody wants you to ask. Why do thyroid weight gain and worsening cardiovascular markers happen together so consistently in the same women at the same time? Why does treating the TSH never touch the blood pressure or cholesterol? Why does treating the cholesterol and blood pressure never touch the thyroid weight? What single upstream cause is running all three — and why is nobody looking for it? So I went down a rabbit hole. A deep one. I started researching not how to support the thyroid or manage cardiovascular markers separately — both had been tried every way possible — but what single mechanism would produce weight gain, rising blood pressure, AND rising cholesterol simultaneously in a woman on levothyroxine with a perfect TSH. Every mainstream site gave me the same recycled answers. Adjust the dose. Eat better. Exercise more. Statins when the cholesterol gets high enough. Then I found something in a research paper that stopped me cold. Not a blog. Not a wellness influencer. Peer-reviewed endocrinology research. And it connected the thing I had never seen connected in three years of searching. Here's what I learned. Your levothyroxine is inactive T4. Before it can do anything for your metabolism, it must convert to active T3 in the liver. Your metabolism is what your body runs on — what burns fat instead of storing it, and what processes and clears cholesterol from your blood. When that conversion is blocked, your metabolism shuts down. And a shut-down metabolism can't clear cholesterol any more than it can burn fat. When cortisol stays chronically elevated — the low-grade continuous kind every woman managing a full life carries — it blocks that conversion. The liver tissue where the conversion happens gets surrounded by cortisol-driven fat and can't do the job. The ignition signal the conversion enzyme needs to activate stays suppressed. Decoy molecules flood the thyroid receptors and block the active hormone from landing even when some conversion does occur. Three blockades. Same cortisol. TSH looks perfect because TSH measures hormone in the blood — upstream of every one of these failures. That's why the weight ignores 1,200 calories. The metabolism is running at minimum because the active hormone that runs it never arrives. Fat storage runs as default because the T3 signal to burn never comes. And here's the piece that explained the cardiovascular markers. The same cortisol signal running the conversion blockade is simultaneously giving the kidneys a different instruction. Hold the fluid. The kidneys stop draining what they're supposed to drain. Fluid builds in the circulatory system. Volume pressing against the arterial walls from the inside increases. The blood pressure reading climbs every year not because of salt or age — because cortisol keeps running the hold instruction year after year. And the metabolism running at minimum because the conversion is blocked cannot process and clear cholesterol the way a functioning metabolism does. The LDL accumulates not because of what she's eating. Because the system that handles it isn't running. Three deteriorating markers. One cortisol signal. The weight — conversion blocked, metabolism suppressed, fat storage running as default. The cholesterol — metabolism too suppressed to process and clear it properly. The blood pressure — cortisol instructing the kidneys to hold fluid year after year. All three worsening together. All three unresponsive to separate medications for each. Because none of those medications touched the cortisol signal running all three from the top. And here's the part that made my blood boil. The connection between chronic cortisol elevation and impaired T4-to-T3 conversion is in the endocrinology literature. The role of cortisol in kidney fluid retention and blood pressure elevation is documented. The relationship between thyroid hormone deficiency at the cellular level and cholesterol accumulation is published and replicated. But the standard clinical protocol for Hashimoto's patients with worsening cardiovascular markers doesn't include a cortisol assessment. Doesn't ask whether the same signal blocking the thyroid conversion is building the fluid pressure and suppressing the metabolism handling cholesterol. Because there's no pharmaceutical drug for cortisol-driven simultaneous multi-system failure. You can't patent the mechanism. There's no revenue in finding the single upstream cause and removing it. There IS revenue in levothyroxine for life. A statin for the cholesterol. A blood pressure medication for the pressure. Three separate prescriptions. Three separate specialist relationships. Three separate monitoring schedules. All managing the outputs of a cortisol signal nobody is measuring. Manage every output. Never reset the source. Keep the patient returning indefinitely. So I kept digging. Looking specifically for what resets the cortisol signal at the source — not manages it temporarily, not dampens one output — actually normalises the hypothalamic command running all three mechanisms simultaneously. And I found one compound that kept appearing in peer-reviewed research — not wellness content — as the specific solution. Rhodiola Rosea. Not marketed for thyroid. Not marketed for blood pressure. Not marketed for cholesterol. Researched specifically for cortisol — and for what happens to all three downstream systems when the cortisol signal running them is reset at the hypothalamus where it originates. When that signal normalises, the liver begins clearing the fat burden surrounding the conversion tissue. The conversion enzyme gets the ignition signal cortisol was suppressing. The decoy molecules drop. The T4 from levothyroxine finally converts and the metabolism activates for the first time. Simultaneously, the kidneys stop receiving the hold instruction. The fluid cortisol was building in the circulatory system begins to clear. The pressure drops because the load generating it was removed at the source. And the metabolism running on adequate T3 begins processing cholesterol the way it was always designed to. Three mechanisms. One reset. Because they were always running from the same signal. My sister tried to find a Rhodiola supplement that matched what the research described. First — the highest-rated one on Amazon. Five stars. Thousands of reviews. Eight weeks. Nothing moved. Weight unchanged. Blood pressure unchanged. Cholesterol unchanged. Second — a well-known adaptogen brand. Ten weeks. Marginal stress reduction. Every cardiovascular marker unchanged. Weight unchanged. She went back to the research. Read the methodology. The studies showing cortisol normalisation and downstream cardiovascular improvement used a specific standardisation: 3% rosavins and 1% salidroside. That's the ratio at which hypothalamic reset was measured. That's the concentration at which the downstream improvements — conversion running, fluid clearing, metabolism normalising — were actually recorded. She flipped over both bottles. No standardisation listed on either. Just "Rhodiola Rosea extract." No ratio. No active compound guarantee. Eighteen weeks of ground plant material. The compounds responsible for the mechanism possibly present in trace amounts. Possibly not at all. All three blockades still running. There was also the absorption problem. The rosavins are fat-soluble. Without BioPerine they don't reach the hypothalamus where the cortisol signal originates. Most manufacturers skip it because it costs more. Wrong standardisation. No absorption support. Eighteen weeks of a product that couldn't reach the mechanism at any level. Between the selenium, the dietary protocols, the specialist appointments, and two rounds of unstandardised Rhodiola — she'd spent over £3,500 in three years. I was scrolling through my phone late one night — because her doctor had just told her the statin conversation was no longer optional — and I saw someone in a UK Hashimoto's support group mention a small company called Rosewyn. Different woman. Different city. Same story. Optimal TSH. Weight climbing on levothyroxine. Blood pressure climbing. Cholesterol climbing. Statins being discussed. Tried unstandardised Rhodiola. Nothing worked. She'd found the cortisol connection. Tried Rosewyn. Posted her three-month blood test results. Blood pressure down 24 points systolic. LDL down 34 points. Weight down 7.5 kg. On the same levothyroxine dose she'd been taking for years. Someone in the thread asked about the standardisation. "3% rosavins and 1% salidroside. Clinical dose. BioPerine for absorption. The unstandardised ones can't reach the hypothalamus — the mechanism never runs. This one does." I went to their site. Ready to be disappointed like I had been every other time. Rhodiola Rosea standardised to exactly 3% rosavins and 1% salidroside at clinical dose. BioPerine included for absorption. The only Rhodiola product in this category doing both. Third-party tested. Certificate of analysis published. Manufactured to GMP standards. No proprietary blends. Every amount listed. Not a thyroid supplement. Not a cardiovascular supplement. A cortisol reset formula that removes the signal running all three blockades simultaneously. My sister started taking Rosewyn. After two weeks? She measured her blood pressure on the home monitor she'd been using every morning for over a year. 126 over 81. It had been sitting between 136 and 142 for two years. She texted me the reading without any other words. I knew exactly what it meant. The kidney fluid instruction cortisol had been running was beginning to normalise. After four weeks? The scales moved. Down 2.5 kg. Not from eating differently. Something releasing. She called me not because of the number, but because of what it felt like. "It doesn't feel like diet weight loss," she said. "It feels like something let go." Because it had. The fat cells were finally receiving the T3 activation signal that told them to burn rather than store. The conversion was finally running. After six weeks? She took the stairs at work. Two flights. Without her heart pounding at the top. She stood at the landing and sent me one sentence. "I just walked up two flights without stopping." I knew exactly what she meant. After eight weeks? Blood pressure 118 over 76. Down from 142 over 88 at her worst. The fluid that cortisol had been instructing her kidneys to hold for years was clearing as the cortisol signal driving the instruction normalised. After twelve weeks? She went back for follow-up blood tests. LDL — down from 168 to 127. The metabolism running on adequate T3 for the first time was processing cholesterol the way it was designed to process it. Free T3 — risen into the upper third of the reference range. On the same levothyroxine dose she'd been taking for three years. Weight — down 8.5 kg at twelve weeks. Her doctor pulled up the previous panel. Looked at the current one. Looked at her. "Your LDL has dropped significantly. Your blood pressure at this visit is 116 over 74. Your free T3 is the best I've seen since your diagnosis. What changed?" My sister explained it. The cortisol running three simultaneous mechanisms. The conversion blockade keeping her metabolism suppressed. The kidney fluid instruction building her blood pressure year by year. The suppressed metabolism unable to process the cholesterol accumulating in her blood. The single cortisol signal running all three. The Rhodiola standardised to the ratio that resets the hypothalamic output running them. Her doctor typed notes slowly. "The cortisol-conversion-cardiovascular connection is documented in the literature. I don't typically investigate it because there's no pharmaceutical intervention for it in the standard protocol. But these results across three markers in twelve weeks — that's significant." Long pause. "Whatever you changed — keep doing it. And I'm not writing the statin prescription today." Not writing the statin prescription. After three years of being told it was coming. She walked to her car. Got in. Then she called me. "LDL down to 127. Blood pressure 116 over 74. Free T3 finally in range. No statin. Three years. Four doctors. £3,500. On medication. Getting worse every six months. Every single one of them managing three outputs while the signal running all three kept running underneath." Her husband came home that evening and looked at her across the kitchen. "You look like yourself again." Before she'd told him a single thing about what had changed. Total improvement at five months: LDL normalised. Blood pressure in optimal range. Free T3 in upper third of reference range. Down 11 kg (over 1.5 stone). Same levothyroxine dose. Finally converting. Statin conversation closed. Doctor monitoring without prescribing. Not from a statin managing cholesterol while a suppressed metabolism kept producing it. Not from a blood pressure medication fighting fluid while cortisol kept instructing the kidneys to hold it. From resetting the cortisol signal running all three simultaneously. One reset. All three resolving. This is what they don't want you to know. Because the second you reset the cortisol driving the conversion blockade and the kidney fluid retention simultaneously — you don't need their statin for cholesterol that a functioning metabolism would handle. You don't need their blood pressure medication for fluid that kidneys would drain if cortisol stopped instructing them to hold it. You don't need their dose increases feeding more T4 into three blocked checkpoints. The conversion runs. The fluid clears. The metabolism processes cholesterol the way it was designed to. All three markers move from one upstream reset that none of their three prescriptions was ever designed to reach. Now here's what I need you to understand. The cortisol signal doesn't stop on its own. Every month it keeps running is another month of the conversion blockade suppressing your metabolism. Another month of the kidney fluid instruction building pressure in your arteries. Another month of cholesterol accumulating in blood that a suppressed metabolism can't clear. Another month of your doctor getting closer to a statin conversation that treats the output while the signal keeps running underneath. So if you're dealing with ANY of this — weight that ignores every calorie deficit on levothyroxine, blood pressure climbing year by year while your TSH stays optimal, cholesterol moving the wrong direction despite dietary intervention, heart pounding on stairs while your bloods say you're fine, a doctor preparing three separate prescriptions for three symptoms running from the same signal — this is the time. Not next month when the LDL climbs another nine points. Not when your doctor says the statin is no longer optional. Not when the blood pressure medication gets added to the pile. Right now. Rosewyn. Rhodiola Rosea standardised to 3% rosavins and 1% salidroside. Clinical dose. BioPerine for absorption. Third-party tested. Manufactured to GMP standards. No proprietary blends. Every amount listed. 90-day money-back guarantee. Use every capsule. If the LDL doesn't improve, if the blood pressure doesn't normalise, if the weight doesn't start moving, if your free T3 doesn't rise on the same levothyroxine dose — full refund. No questions asked. Because your endocrinologist isn't coming to identify the cortisol running the conversion blockade and the kidney fluid retention simultaneously. There's no protocol for it. There's no prescription for it. There's no revenue in it. The three prescriptions they're preparing treat the outputs. Nobody is resetting the signal. You have to reset it yourself. https://rosewynhealth.com/pages/thyroid
Where the ad sends people
rosewynhealth.com
The Truth About Levothyroxine & Weight Gain
Rosewyn
Learn more: rosewynhealth.com(opens in a new tab)

















