
Inactive· since Jul 26, 2026
- 8
- days it ran
- 0
- relaunches
Ad copy
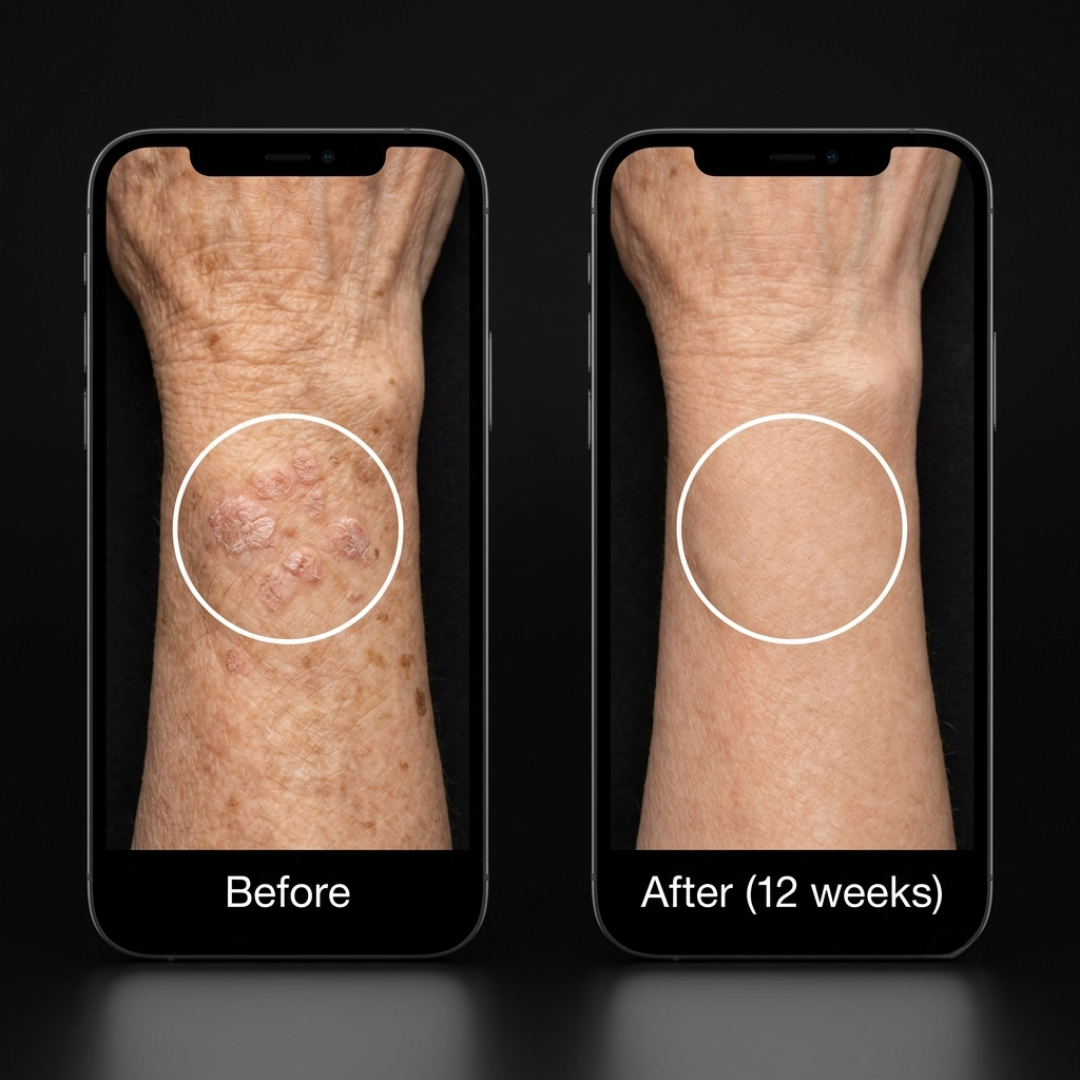
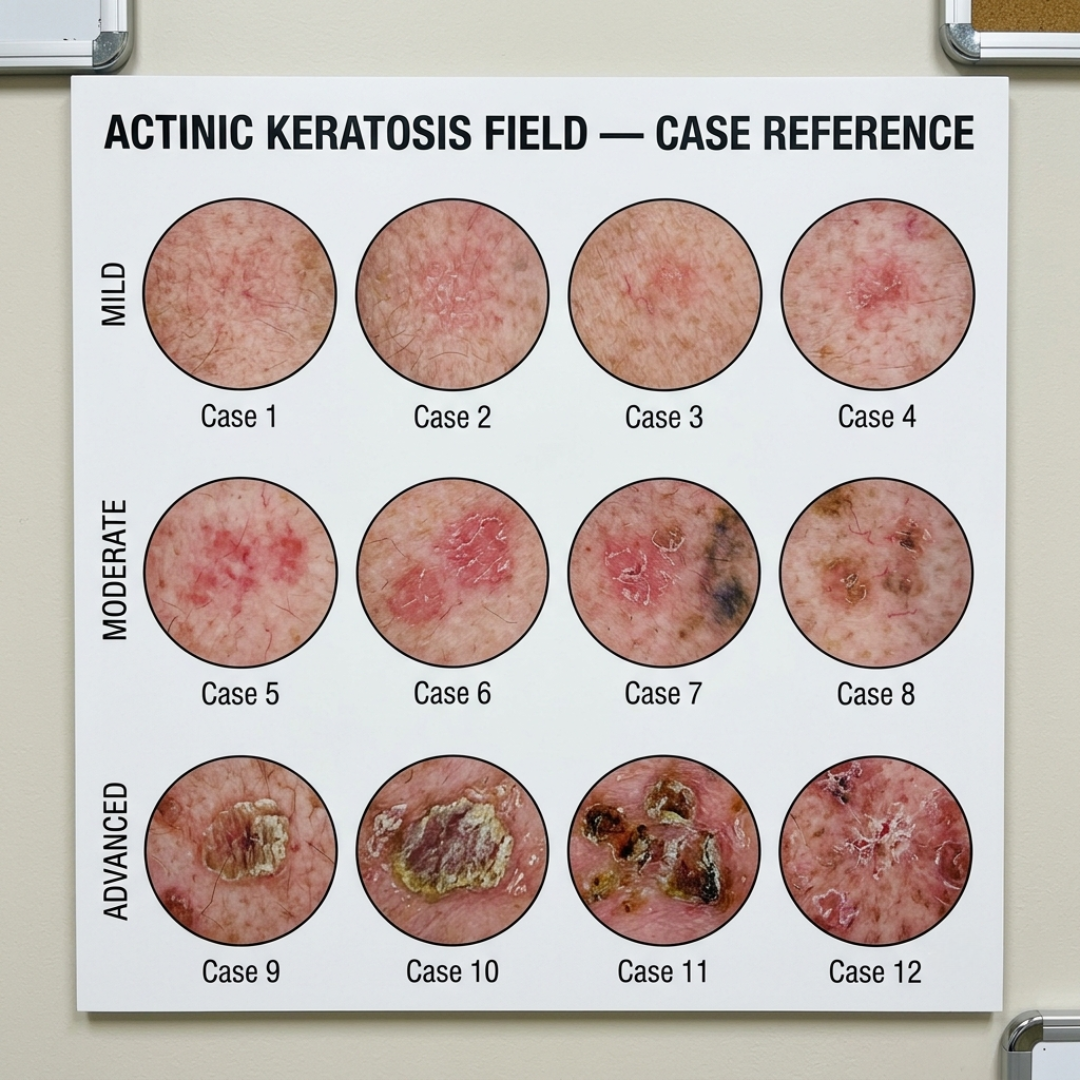
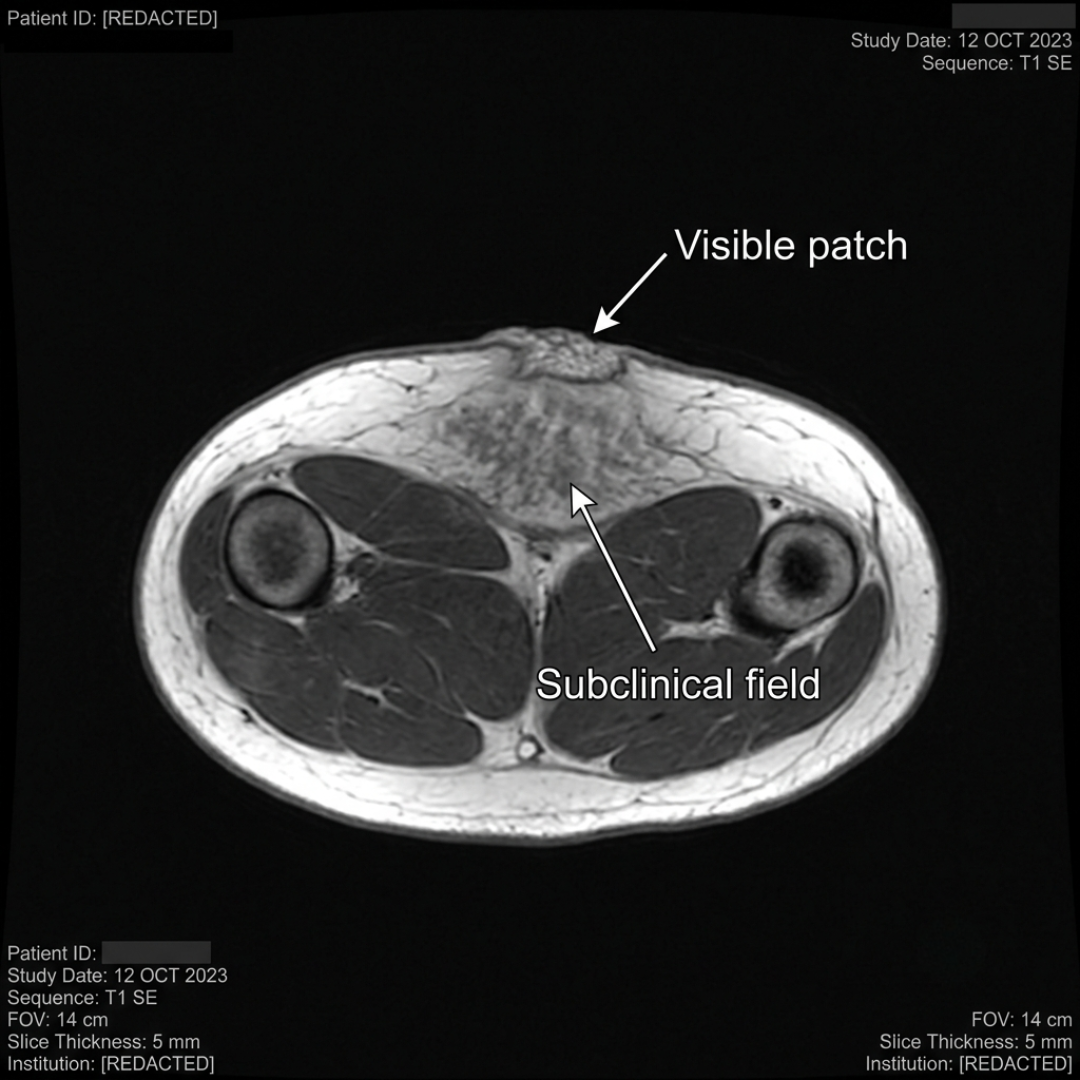
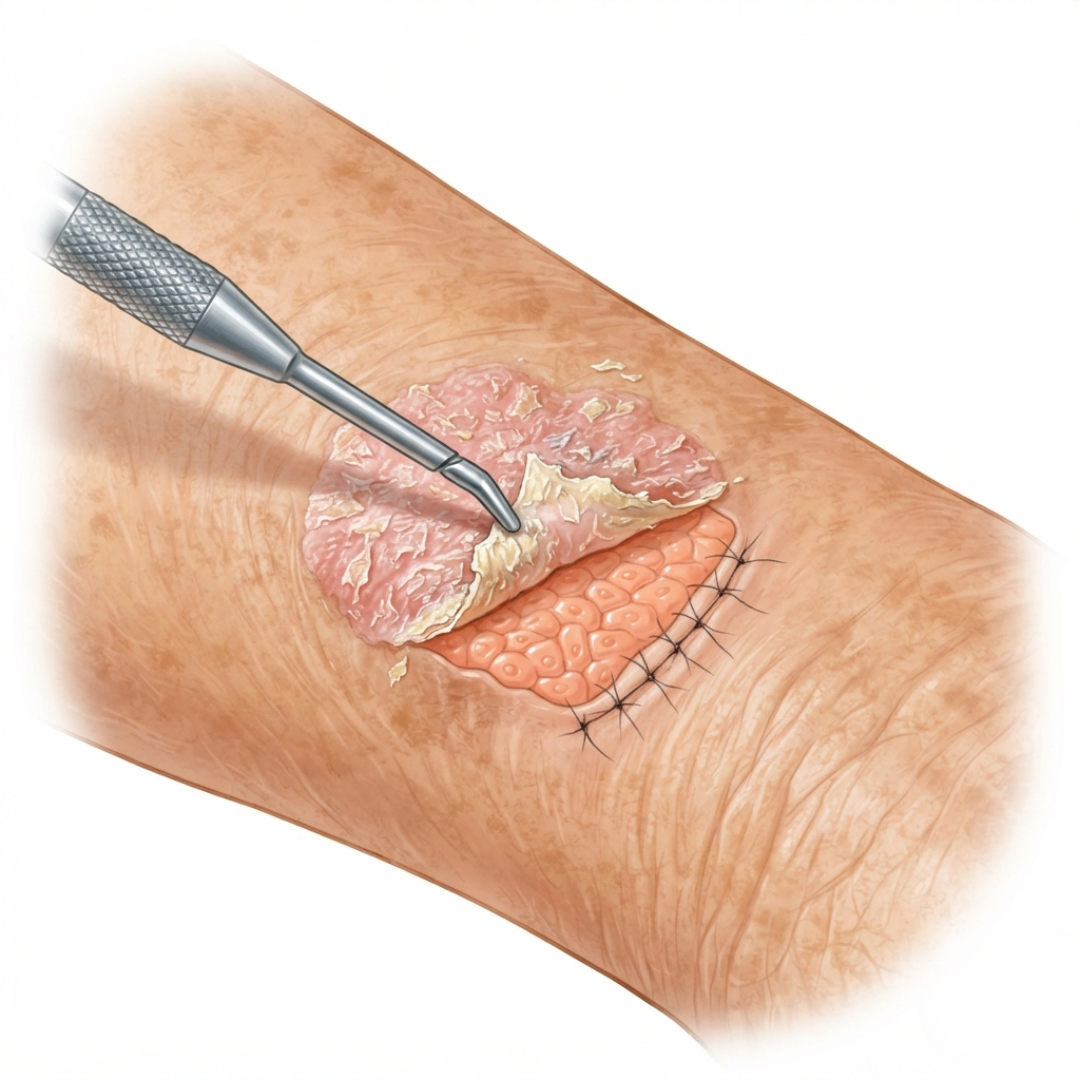
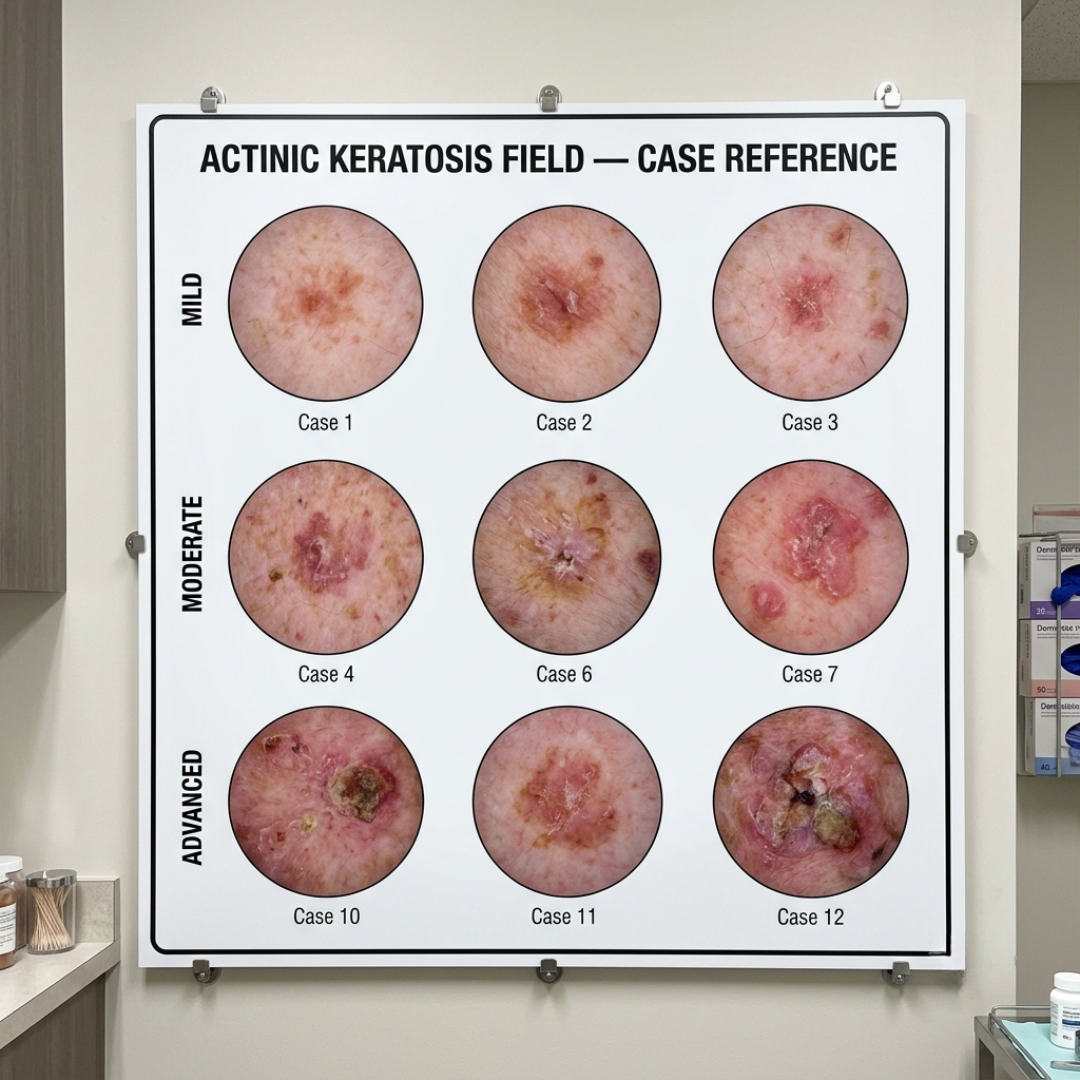
My new dermatologist pulled up my file, read for forty-five seconds, and said "this has been mismanaged." She'd never examined my skin. She was looking at a screen. Dr. Garber's letter arrived on a Friday. Typed. One page. "After 28 years serving this community, I am retiring effective November 30th. Patients will be contacted regarding record transfer and transition of care." I read it standing at the mailbox. Eight years. I'd been going to Dr. Garber for eight years. She had watched my arms from the beginning. Documented every patch from the first rough spot on my left forearm in 2016 to the fourteen active sites that had spread to both forearms, both hands, and my upper arms by 2023. She knew my sister's history — patches that had started in her 50s, freeze sessions every few months for years, a progression that never stopped. She'd always been direct with me. "We stay consistent, Linda. Every new patch gets treated before it has a chance to establish." Now she was retiring. My transition appointment with Dr. Reyes was November 14th. New practice. New building. Same paper gowns. Dr. Reyes came in reading my chart on her tablet. She sat across from me. She had the kind of stillness that comes from delivering difficult information regularly. "Ms. Fletcher." She looked up. "I've reviewed your records from Dr. Garber. I want to talk through what I'm seeing." She turned the tablet so I could see the screen. "2016: one lesion, left forearm. 2017: four lesions, both forearms beginning. 2018: eight active sites, hands included. 2019 through 2023: between eleven and fourteen active sites, documented spread every single year, new lesions appearing between appointments in skin that was photographed as clear at the previous visit." She set the tablet down. "Eight years of quarterly freeze sessions. Your actinic keratosis has gotten worse every year you were under Dr. Garber's care." "She was on top of it. Every new patch—" "Every new patch that appeared after the previous one was treated." Her voice was careful. "Ms. Fletcher, your dermatologist was responding to the condition. She wasn't getting ahead of it. Nobody was addressing the dermal field that was generating new lesions. I need to change your protocol significantly." "What does that look like?" "Aggressive field therapy. 5-fluorouracil cream across all affected areas — both forearms, both hands, upper arms — twice daily for six weeks. Then photodynamic therapy, minimum two sessions. I also want to begin imiquimod on the forearm sites. Twice weekly, ongoing." She was entering it into the system. "If we don't see adequate field response after the first full treatment cycle, we look at escalation." "I've had sixteen freeze sessions over eight years and nothing has—" "I know. That's why we're not doing seventeen freeze sessions. This is whole-field intervention." "But new patches kept forming between every appointment. Every time I'd come in thinking we'd gotten ahead of it—" "Because the subclinical field underneath was never being addressed. We were destroying visible lesions while the field generating them was left untouched. We need to treat the entire affected surface now." The printer ran. She handed me a sheet. 5-fluorouracil cream, six-week course: $360. Photodynamic therapy, two sessions: $1,600. Third session likely needed: $800. Imiquimod cream, ongoing: $195/month. Freeze sessions as needed: $185 each. Follow-up every 8 weeks: $210. $2,560 to start. Then close to $1,200 every quarter going forward. She stood. Shook my hand. Eight minutes. I walked to my car. In the parking lot, I called my husband. "How did it go?" "New dermatologist says eight years of treatment was mismanaged. Wants me on aggressive field therapy — a cream twice a day for six weeks that she said would cause my skin to weep and crust. Then light therapy. Over $2,500 today. Then more than $1,000 every quarter after." Quiet. "Every quarter?" "If I don't agree, she documents it as non-compliance." "But you've been doing freeze sessions every few months for eight years—" "And I have fourteen active sites. More than I started with." He was quiet for a moment. "So the answer is... harsher treatment?" I didn't have a response. That night I couldn't settle. Walked the house. Stood in the kitchen with the lights off. Dr. Garber had done what Dr. Reyes wanted to do. Just less intensely. Freeze every visible patch. Diclofenac between. Photograph and document. Return in three months. Sixteen freeze sessions. Fourteen active sites. More than I'd started with. And Dr. Reyes wanted to do the same thing harder. Wider field treatment. More aggressive chemicals. Fifteen times the annual cost. Was harder the answer to something that hadn't worked in eight years? At 2 AM I sat at the kitchen table with my laptop open. *actinic keratosis keeps spreading despite regular freeze treatment* *does freezing address subclinical AK field* *why does diclofenac stop being effective for AK* The clinical sources all said the same thing. Cryotherapy is the standard first-line treatment for visible actinic keratosis lesions. Monitor and treat as new patches appear. Then I found the patient forums. "Eight years of freeze sessions. Fourteen active sites. My dermatologist just says 'we'll watch the new ones closely.' When does watching stop and fixing start?" "$185 every session, four appointments a year, eight years. Over $5,900. My patches are worse than when I started. But the answer is apparently to keep going." "The 5-FU treatment was the hardest six weeks of my life. Couldn't go outside. Couldn't cook. Couldn't do anything that involved my hands. Two months after finishing — new patches at the borders of the treated area. Already scheduled for a second round." "Ten years of freeze sessions. Twelve thousand dollars. My new dermatologist says I need photodynamic therapy. I asked her — if the freezing was going to stop the field, wouldn't it have stopped it by now? She didn't have a good answer." I read those over twice. These women had my story. Some eight years behind me, some eight years ahead. I searched: *why does actinic keratosis keep progressing after treatment* And I thought about my sister. She'd started freeze sessions in her late 50s. Quarterly, sometimes every six weeks when it was bad. Same cycle every appointment — the ones that had calmed, and the new ones appearing in skin that was photographed as clear at the last visit. Seven years. Close to $6,000. Her AK never stopped spreading. The appointments became her whole rhythm. She stopped wearing anything without sleeves past the elbow. She started timing garden work to avoid being seen by the neighbors. She stopped accepting invitations that would put her arms visible in photographs. She reoriented everything around a condition that just kept getting worse. Then 5-fluorouracil. The crusting and weeping. Back again within the season. Imiquimod next. Coverage fights. Another round. I talked to her on the phone one evening not long ago. She mentioned she'd pulled her sleeves down at her granddaughter's birthday. Had been doing it for so long it was just what her hands did now. "Seven years," she said. "Seven years on the schedule. Four rounds of field therapy. Everything they could suggest. And I still can't wear a short sleeve without feeling like everyone's staring." Her AK is still spreading. I closed the laptop. Sixteen sessions over eight years. Fourteen active sites and spreading. And Dr. Reyes wanted more. Wider. Harder. More money. The same approach that hadn't worked for my sister in seven years and hadn't worked for me in eight. The treatment plan was on the table. $2,560 today. $1,200 every quarter. Indefinitely. I left it there for a week. Dr. Reyes' office called. "Ms. Fletcher, you haven't scheduled your photodynamic therapy sessions. Dr. Reyes wanted to confirm you're proceeding with the treatment plan." "I need more time." "Ms. Fletcher, actinic keratosis is a progressive pre-cancerous condition. The subclinical field continues to develop without intervention. Dr. Reyes was very clear about the timeline—" "I understand. I need more time." I ended the call. My husband found me in the backyard the following Sunday. Sitting on the bench. Arms in my lap. "Talk to me." "Sixteen freeze sessions over eight years. Fourteen active sites. How." "Dr. Reyes says more aggressive—" "More aggressive. The same thing. More expensive. The same thing that didn't work in eight years, done harder. And my sister has been through this for seven years and still can't wear short sleeves without anxiety." He sat beside me. "What do you want to do?" "I want to understand why it keeps spreading. Not just do more of what hasn't worked." That week I read everything. Clinical journals. Studies on AK field treatment outcomes. Research on topical penetration and keratinocyte populations. And I found the answer. *Why doesn't freezing stop new lesions from forming?* Liquid nitrogen destroys the visible lesion. The surface patch the dermatologist can see and target. That's why the site calms after a session. That's why Dr. Garber always said "that one looks good." But the subclinical field — the wide zone of UV-damaged keratinocytes spreading invisibly through the surrounding dermal tissue — doesn't get reached. Cryotherapy is a targeted, precise tool. A point treatment. It was never designed to address a field of abnormally cycling cells in the dermis. Those cells keep generating. Keep producing. Within weeks, a new lesion surfaces in skin that was photographed as clear at the last appointment. The field continues on schedule, every quarter, regardless of how many visible patches have been frozen. That's the cycle. Freeze the visible. The field generates the next one. Repeat. And diclofenac? It reduces inflammation on the surface. Slows the visible progression. But it's water-based. It can't cross the lipid barrier of the stratum corneum in meaningful concentrations. The UV-damaged keratinocytes generating new lesions live in the dermis, at a depth water-based compounds don't reach. Less than four percent penetrates far enough to matter. Like putting a compress on the ceiling while the water source is in the floor below. And the 5-fluorouracil Dr. Reyes proposed? It treats the surface field aggressively. Forces cell turnover across the affected area. Your skin weeps and crusts for weeks as surface-layer damaged cells are destroyed. But the dermis underneath — where the keratinocytes generating the next round of lesions are cycling — isn't reached. Nothing in the standard protocol addresses the actual source. I sat back. Sixteen freeze sessions addressing visible lesions while the field generated underneath. Eight years of diclofenac sitting on the surface barrier. Field chemotherapy next — treating a wider zone of visible surface while the dermal field continued beneath it. The same fundamental approach. Applied with more force. More cost. Then I found a different line of research. Studies on lipid-soluble delivery systems and UV-damaged keratinocyte populations in the dermis. The key finding: water-based compounds — gels, serums, diclofenac — cannot penetrate the stratum corneum to reach the dermis where the subclinical field operates. But cold-pressed plant oils can. Camellia oil and sea buckthorn oil — lipid-based carriers — penetrate all seven skin layers and deliver actives directly to the dermal layer where the field lives. Oil-soluble vitamin C — ascorbyl tetraisopalmitate — at clinical concentration: directly addresses the UV-induced oxidative cascade driving abnormal keratinocyte proliferation. In the dermis. Where the field generates. Bakuchiol at clinical concentration: supports normal keratinocyte cycling without the rebound irritation that retinol causes in UV-damaged skin. Replacing the abnormal proliferation signal with healthy cell renewal from the dermal layer outward. The delivery principle: oil-soluble actives require a lipid carrier. Water cannot transport them through the skin barrier. Cold-pressed camellia and sea buckthorn oil penetrate the stratum corneum and carry actives with them — through all seven layers — to the dermis. To the field. I started testing botanical oils. First: the best-reviewed vitamin C body oil I could find. Six weeks, twice daily, no exceptions. Patches still rough. Still raised. Next: a botanical formula a naturopath had recommended to two people I knew. Six weeks. Maybe marginally less rough. Impossible to say for certain. Third: a specialized formulation from a dermatology-adjacent skincare brand. Eight weeks. No change. New patch forming at the edge of the treatment zone. My appointment was two weeks out. I was going to have to choose. $2,560 today. $1,200 every quarter. Field therapy that would address the visible surface while the dermal field kept generating underneath. Ten days before the appointment, I was at a Saturday market. Local vendors. Stopped at a skincare table without meaning to — old habit of checking botanical oils. A woman nearby was doing what I was doing. Reading the ingredient panel on a bottle. Late 60s. Reading glasses. Taking her time. She looked up at me. "Checking the carrier?" "Checking whether anything here is going to actually reach the dermis." She set the bottle down. "None of these will. Safflower. Sunflower. They sit on the surface." "I've tried three brands in four months. None of them touched my patches." "Actinic keratosis?" "Fourteen active sites. Eight years on the freeze schedule. New dermatologist says I need aggressive field therapy — over $1,000 a quarter. Sixteen freeze sessions never stopped the field from generating." She nodded. She had the look of someone who'd spent time in this exact research. "My neighbor. Eight years on the schedule. Year of botanical oils that didn't work. Almost started the field chemotherapy." "What happened?" "She asked me to look into why the oils weren't doing anything." She picked up a bottle and read the back. "It's always the carrier. Sunflower and safflower moisturize the stratum corneum. They don't penetrate to the dermis. You need cold-pressed camellia oil and sea buckthorn oil — the two lipid carriers that actually transport actives through all seven skin layers. And the vitamin C needs to be ascorbyl tetraisopalmitate — the oil-soluble form. Ascorbic acid is water-soluble. It bounces off the stratum corneum. For it to reach the field in the dermis, you need the oil-soluble form, carried by camellia and sea buckthorn, in a formula with zero water. Every drop of water cuts what reaches the dermis." She showed me her phone. "One formula actually does this. Dermiqua. Cold-pressed camellia and sea buckthorn as the carrier. Oil-soluble vitamin C at clinical concentration. Bakuchiol. Sixteen botanicals. Zero water. Zero filler. It goes to the dermis. To the field." The ingredient list matched the research I'd read exactly. Ninety-day money-back guarantee. "My neighbor has been using it six months. Arms clear — texture gone, edges flat, nothing new at her last two quarterly checks. No field chemotherapy. No photodynamic therapy. After eight years of freeze sessions that never stopped the spreading." "Her dermatologist went along with this?" "Watched it for two visits. Nothing new to document. If it holds — and it's holding — annual checks only. No more quarterly sessions." I ordered it on my phone standing there. Three days for the package to arrive. I applied it that evening. No optimism left — three botanical oils and sixteen freeze sessions had taken care of that. Morning. Patches still there. Of course. Week one — checking every morning. Still rough at the edges. Maybe very slightly less pronounced in one patch. I wasn't counting it. Week two — I ran my fingers across my left forearm. Smoother than yesterday. Ran them again the next morning. Still smoother. And the morning after. Not imagination. Something measurable. My husband noticed I'd stopped wearing the cardigan inside. "You cold?" he asked. "No. I just — didn't need it." Week three — the largest patch on my right forearm. I'd carried it for five years. I pressed it with two fingers. Flat. I did it again. Flat. I walked to the bathroom, looked at it in good light. The raised edges — gone. I went outside and stood in the morning sun with my arms uncovered. Sixteen freeze sessions over eight years never let me do that without immediately checking for new formations afterward. Week four — the day before my appointment with Dr. Reyes. My husband ran his hand across my forearm before I left. "Linda. Your skin." At the appointment, the nurse examined both forearms and hands during intake. She stopped twice. Looked at her notes. Then looked again at my arms. She photographed everything carefully. Dr. Reyes came in. Opened the file on her tablet. Her expression shifted. "The texture across both forearms — significantly reduced. Sites three, seven, and eleven — flat at the margin. No new lesions documented at the previous three active sites." "Yes." She compared the images side by side. Previous visit: rough, raised, spreading. Current visit: smooth, flat, no new formations. "You completed the 5-fluorouracil course?" "No." She looked at me directly. "No?" "A botanical oil. Cold-pressed camellia and sea buckthorn as the lipid carrier — the vehicle that actually penetrates all seven skin layers to the dermis. Oil-soluble vitamin C at clinical concentration. Bakuchiol for cellular turnover. It reaches the subclinical field where the UV-damaged keratinocytes are generating. Where the freeze sessions and the diclofenac never penetrated." Her voice went careful. "Ms. Fletcher, a cosmetic product doesn't constitute medical treatment for—" "Fourteen active sites of rough, raised, spreading actinic keratosis are now smooth and flat. No new lesions at sites that were actively generating every quarter for eight years. That's in your file right now. Sixteen freeze sessions never produced a single visit with nothing new on the watch list." She looked at the images again. The chart. Then me. A pause. "What is it called?" "Dermiqua." She looked it up. Read the site. Reviewed the ingredient list. Camellia oil. Sea buckthorn. Oil-soluble vitamin C. Bakuchiol. Zero water. Silence. "Continue what you're doing. I want a follow-up in eight weeks. If the results are holding, we'll reassess the monitoring schedule." If the results are holding, we'll reassess the monitoring schedule. No field chemotherapy. No $2,560 upfront. No $1,200 every quarter. No photodynamic therapy treating the surface while the dermis kept generating underneath. I walked out. Sat in my car. Texted my sister. "Dr. Reyes just cancelled the aggressive protocol. Fourteen active sites — smooth and flat. No new lesions. I need to tell you about something." She called back before I'd put the car in drive. That was four months ago. Skin this morning: stable. Smooth across all previous sites. No new formations. My dermatologist photographs at every appointment. Nothing to document. Nothing to freeze. I'm wearing the clothes I stopped wearing. Reaching across the table. Standing in the garden in the afternoon with my arms out. I called my sister last week. She's two months into it. She ran her fingers across her forearm while we were talking and said "Linda. It's different." --- If you're reading this, something here is yours. Years on the schedule. Patches that keep coming back. A dermatologist who wants to escalate — field chemotherapy, photodynamic therapy, more aggressive intervention. A treatment plan that costs more than anything you've tried and promises to address the same field that every previous treatment left untouched. A mother or sister who went through this. Years of freeze sessions that never stopped the spreading. Field therapy that came eventually. A life that arranged itself around a condition that kept progressing anyway. You've done the math. $185 a session, four times a year, eight years. More than $5,900. For a field that kept generating. You've tried what was suggested between sessions. Diclofenac. Moisturizers. Maybe other botanical oils. Nothing reached the field. Because nothing was designed to reach the dermis. Here's what I need you to know: If I hadn't stopped at that table at the market, I'd be in week three of the 5-fluorouracil course right now. Skin weeping. Hands unusable. Waiting for the photodynamic appointments. Over $4,800 a year. Watching new patches appear at the treatment margins because the dermal field is still running. Following my sister's path. Seven years of freeze sessions, then field therapy round after round, still spreading, still rearranging life around it. While the subclinical field — the source, the thing every freeze session addressed on the surface and never reached — kept generating. But there's a third option. One that reaches the dermis. Not just manages what the field produces. If you're where I was four months ago — done with the quarterly schedule, watching your AK spread despite everything you've done — try Dermiqua. Morning and evening. Watch your skin. Give it an honest trial. Your future self will thank you. --- I tried three botanical oils before Dermiqua. None of them reached the dermis. Here's why Dermiqua is different. 1. Cold-Pressed Camellia and Sea Buckthorn as the Carrier (Not Sunflower or Safflower) Most botanical body oils use sunflower or safflower. Surface moisturizers. They don't penetrate to the dermis. Dermiqua uses cold-pressed camellia oil and sea buckthorn oil — the lipid carriers that transport actives through all seven skin layers to the UV-damaged keratinocytes generating new lesions. To the field. Freeze sessions clear what they can see. This reaches what they can't. 2. Oil-Soluble Vitamin C — Not the Water-Soluble Version Most vitamin C products use ascorbic acid — water-soluble. Sits on the stratum corneum. Doesn't reach the dermis. Dermiqua uses ascorbyl tetraisopalmitate — oil-soluble vitamin C — at clinical concentration. Carried by the camellia and sea buckthorn into the dermis. Inhibiting the UV-induced oxidative cascade driving abnormal keratinocyte proliferation. Where the field lives. Diclofenac softens the surface. This addresses the generating layer. 3. Bakuchiol at Clinical Concentration for Cellular Turnover Bakuchiol at clinical concentration. Normal keratinocyte cycling. Replacing abnormal proliferation with healthy cell renewal from the dermal layer outward. Without the irritation retinol causes in UV-damaged skin. 4. Zero Water. Zero Filler. Full Penetration. Water dilutes penetration. Dermiqua has zero water. Zero filler. Sixteen cold-pressed botanicals. Every ingredient oil-soluble and lipid-delivered. Everything reaches the dermis. 5. 90-Day Money-Back Guarantee Up to 90 days. Watch your skin every morning. If the rough texture isn't smoothing, if the edges aren't flattening, if new lesions are still appearing on schedule — full refund. No questions. You've already spent enough on sessions that cleared the visible patch and watched the next one form. --- You're being pressured. Aggressive field intervention. Field chemotherapy. Photodynamic therapy. Quarterly freeze sessions on top. Thousands upfront. Thousands every quarter. Maybe a non-compliance notation in your chart. Two paths: One path: Aggressive protocol. Thousands today. Thousands every quarter. New lesions at the treatment margins. Another session. Follow your sister's path. Another path: Find something that reaches the dermis where the field actually lives. Watch your skin every morning. 90-day trial. Zero financial risk. I chose the second path. No more quarterly schedule. No $4,800 a year. Not following my sister's path — seven years on the schedule, four rounds of field therapy, still rearranging life around spreading AK. It gave me my arms back. --- Four months ago I felt like the only choices were two different ways to keep losing. Fourteen active sites. Eight years of freeze sessions. A new dermatologist with a documentation threat and a $2,560 treatment plan. I was watching myself become my sister. Seven years in, still spreading, life arranged around it, no end in sight. I sat at my kitchen table at 2 AM reading posts from women who had spent $6,000, $9,000, $14,000 on sessions and specialist visits. Still spreading. Still told "come back in three months." But there was a third option I didn't know existed. If you're where I was — exhausted from years of the quarterly schedule, watching your AK spread — try Dermiqua. Watch your skin. Give it an honest 90-day trial. Your future self will thank you. 👉 dermiqua.com/pages/actinic-keratosis — Linda Fletcher, 64, Sacramento CA P.S. — Smoother texture by week two. Flat patches by week three. Brought my results to Dr. Reyes at week four. She cancelled the aggressive protocol immediately. Sixteen freeze sessions over eight years never gave me a single visit with nothing new on the watch list. Your dermatologist might back off too — if you have results to show them. P.P.S. — Every freeze session clears the patch they can see while the field in the dermis generates the next one. The field doesn't care how many sessions you book. Liquid nitrogen can't reach a field that lives deeper than the surface. Only lipid-delivered oil-soluble actives get there. Don't spend another year on the quarterly schedule. Order now. P.P.P.S. — I called my sister last week. Two months in. She ran her fingers across her forearm while we were talking and said "Linda. It's different." Eight years of freeze sessions and field therapy never let her say that. A bottle of Dermiqua did.
Like this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.