
Inactive· since Jul 13, 2026
- 21
- days it ran
- 3
- relaunches
Ad copy
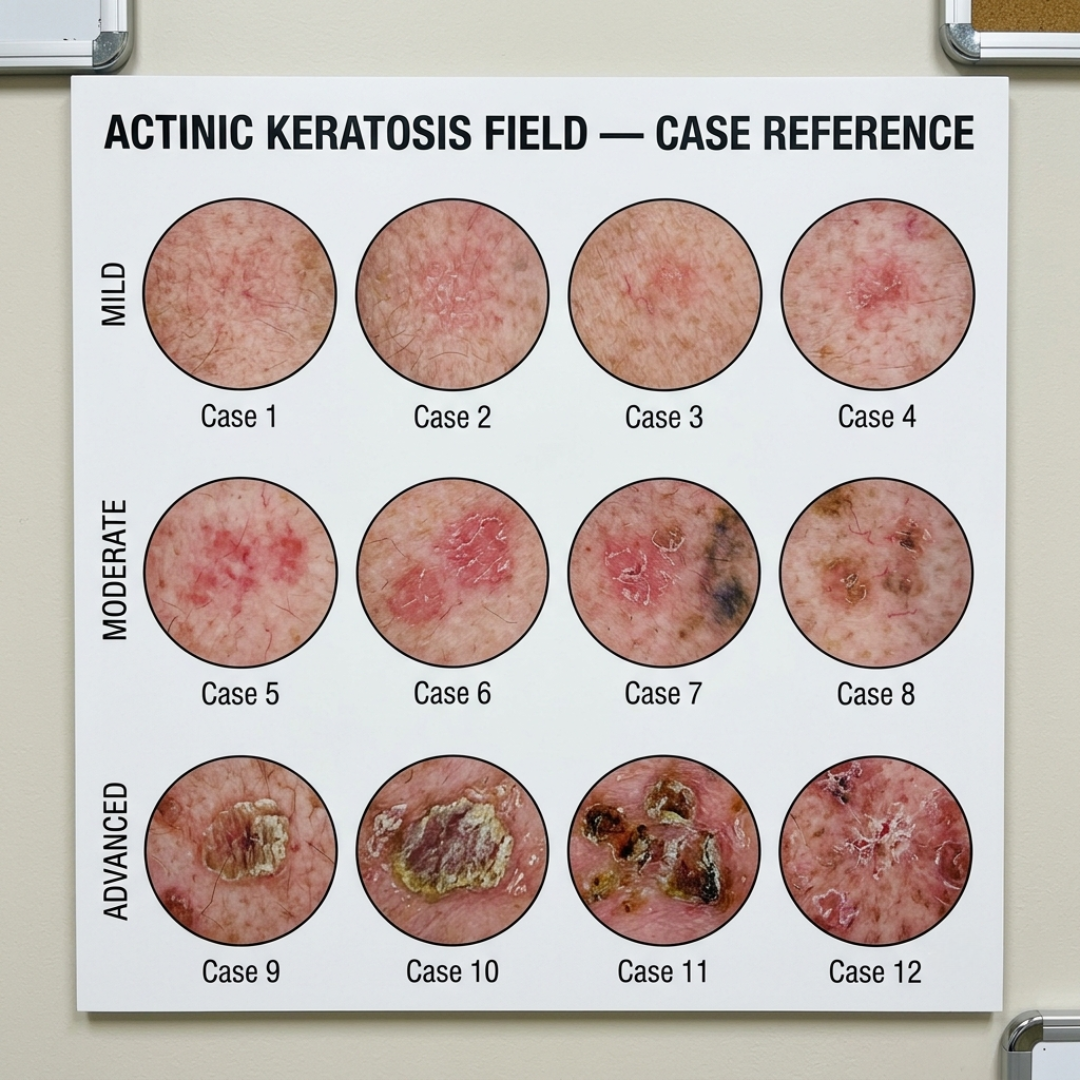
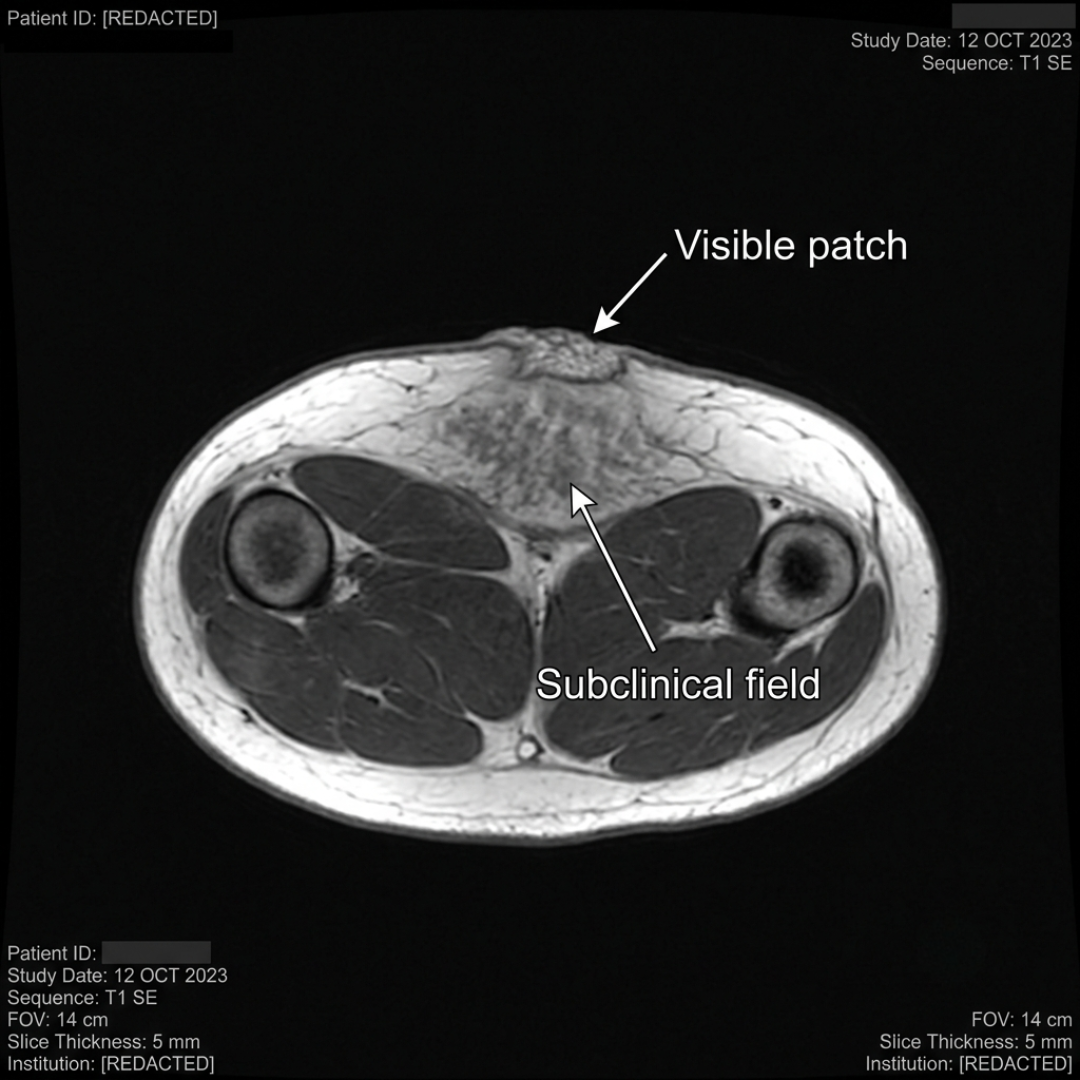
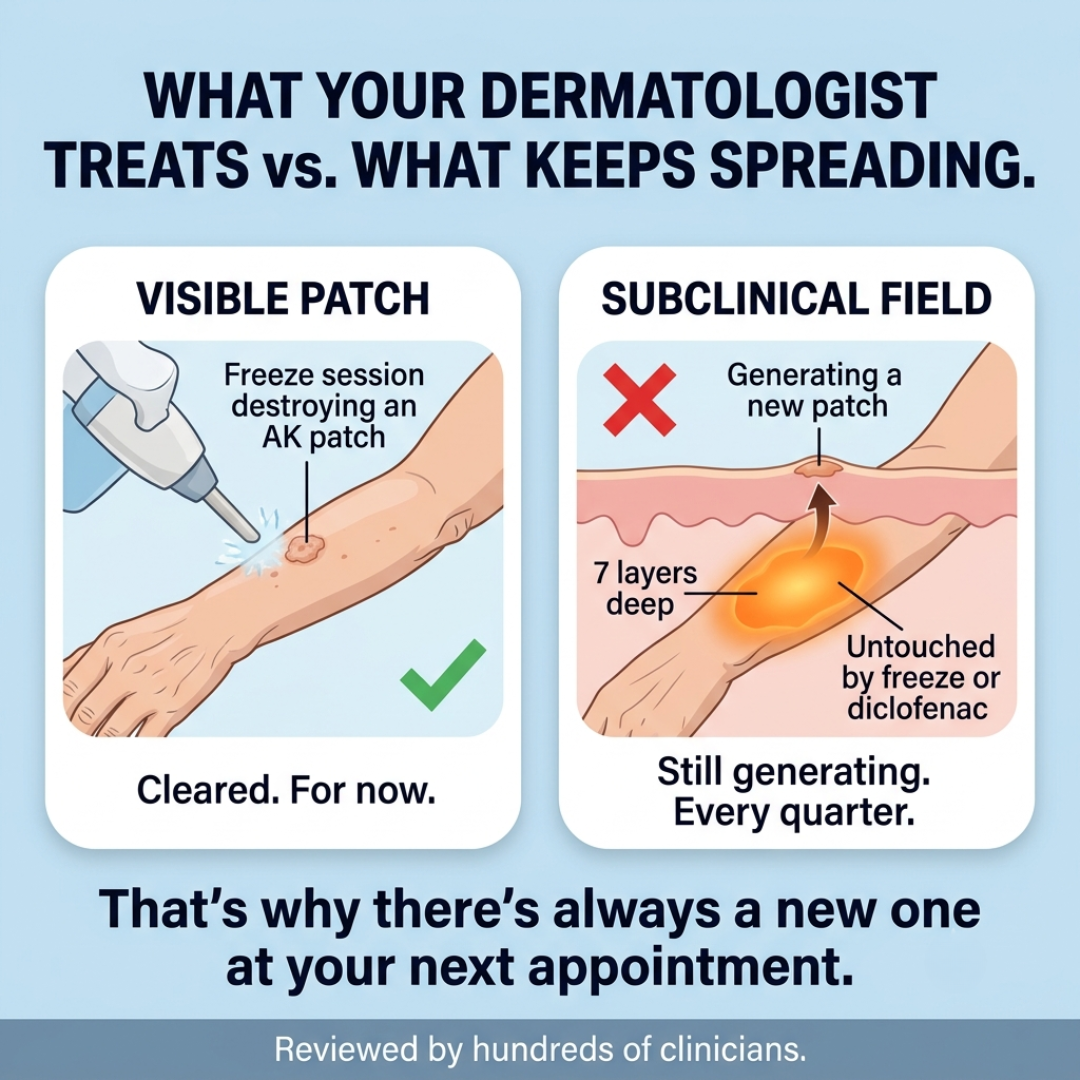
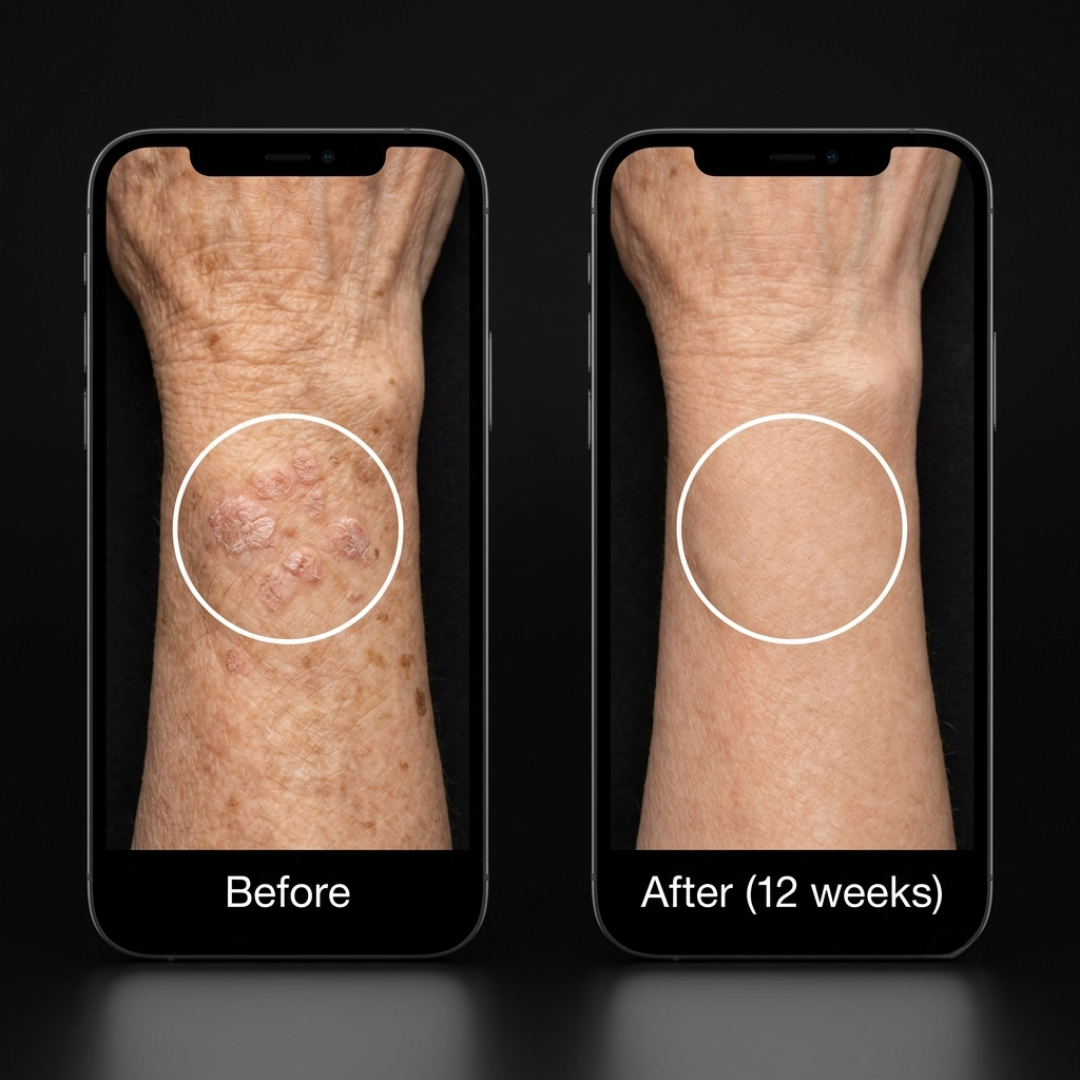
I had actinic keratosis at a dermatology conference in Zurich. The Swiss specialist asked me one question that made me feel dumb. I'm 52. I've been a dermatologist for 18 years. I was at a dermatology conference in Zurich. Sessions on photodynamic therapy techniques, field treatment protocols, the usual. The second night, I went out with my colleagues from the States. A restaurant someone recommended. Everyone wore sleeveless dresses to dinner — the European thing, the casual thing. I kept my cardigan on. The colleague next to me noticed. "You okay? Aren't you warm?" I laughed it off. Said the AC was too strong. The AC wasn't too strong. I had actinic keratosis patches covering both forearms I'd been hiding from my own colleagues for three years. The next morning I ran into a Swiss photoaging researcher in the hotel lobby. Dr. Richter. We'd been in the same breakout session. He noticed my covered arms — at a conference where half the European attendees were in short sleeves — and said, very directly the way Swiss people do, "You have it too, don't you?" I didn't pretend. He was a researcher. He could see it in the way I dressed — the long sleeves, the deliberate coverage. "Yes. Three years. Coming back every quarter for freeze sessions. Applying diclofenac every morning." He nodded slowly. "Any progress?" "The photos look stable. But new patches keep appearing between visits." He looked at me. "You know what percentage of your diclofenac actually reaches the field generating those patches?" I'm a dermatologist. I have a degree. I've treated thousands of patients. But I still didn't know the exact number. I said something vague about topical absorption rates. He waited politely. "Less than 4 percent," he said. "Your diclofenac sits on the outside of the stratum corneum — a dense lipid barrier that was specifically designed to keep water-based compounds out. Less than 4 percent gets through. And underneath, deep in the dermis, the subclinical field has been generating unchecked — producing patch after patch while the surface is treated and called stable." I knew this technically. But I had never once thought about what it meant for my own skin. "No amount of water-based topical application reaches that field," he continued. "Diclofenac manages the surface inflammation. The field lives underneath, in the deep dermis, in an environment the water-based formula has never entered. So the patches keep generating. And the standard protocol keeps freezing them." I sat there in a hotel lobby in Zurich feeling ashamed. A dermatologist. With her own actinic keratosis. Being told something about her own specialty that she was never taught in her own training. --- I landed in Boston at 11:30 PM. Got home and immediately opened my laptop. I wasn't looking for anything specific. I just couldn't let the question go. "Subclinical AK field treatment failure water-based compounds" "Stratum corneum penetration botanical oil actinic keratosis" "Oil-soluble vitamin C deep dermis UV-damaged keratinocytes" At 1 AM I found it. Study after study confirming what Dr. Richter had said. Less than 4% topical penetration through the stratum corneum. Subclinical field generation running unchecked in the deep dermis for years while the surface is treated and called "stable." And then the research on lipid-based dermal penetration. Cold-pressed camellia and sea buckthorn oil — lipid-soluble carriers. They travel through the stratum corneum. Reach the dermis from the inside — where the water-based barrier doesn't block them. The subclinical field is driven by UV-induced oxidative cascade. Oil-soluble vitamin C at clinical concentration neutralizes it at the source. Bakuchiol supports normal keratinocyte cycling from the dermis out. But the carrier has to be cold-pressed. Heat extraction degrades the active compounds. And the vitamin C has to be oil-soluble — ascorbyl tetraisopalmitate, not ascorbic acid. Most water-based serums have less than 4% chance of reaching the dermis at all. Nobody taught us this. American dermatology education is built on two pillars. Topical management and procedural intervention. That's what four years of training teaches. Nobody teaches us to think about the subclinical field as a treatment target. Nobody teaches us that the diclofenac we're prescribing has a 96% failure rate at the stratum corneum barrier before it ever reaches the generating field. So we graduate knowing how to freeze. How to photograph. How to refer for field chemotherapy. We don't graduate knowing that the patches we're photographing are being driven by a field the diclofenac was never going to reach. --- I sat there at 1:30 AM in my kitchen. Feeling guilty and angry at the same time. I found Dermiqua. Cold-pressed camellia and sea buckthorn oil as the lipid carrier. Oil-soluble vitamin C at clinical concentration. Bakuchiol for natural cellular turnover. Sixteen botanicals. Zero water. Zero filler — verified on the label. Applied morning and evening. I called my pharmacist the next morning — I'm on a blood pressure medication. No concerns. Two minutes. I ordered it that night. $44.95 a bottle. When it arrived I started immediately. Week 1: Nothing obvious. I kept going. Week 2: The rough sandpaper texture between my patches — the texture I'd been ignoring because I assumed it was just part of the condition — softened. The skin between my visible patches was smoother for the first time in three years. Week 4: The raised edges on my largest patch on my right forearm started flattening. I pressed my forearm flat against the bathroom counter. No catching. No rough edges dragging. I'm a dermatologist. I know what meaningful texture change looks like. I know what it means when raised edges start flattening. I told myself not to read into it. Patches don't flatten that fast from surface treatment. But this wasn't from the surface. This was from the dermis. Week 8: I took a photo. Compared it to one I'd taken the morning I started. The difference was visible. Three patches visibly flatter at the edges. Surface texture improved across both forearms. Week 12: I sat in my own chair and had my assistant photograph my arms without telling her what I'd been doing. She compared the new images to the ones from three years of my own chart. She looked up. "Your patches improved." "I know," I said. "What did you do?" I told her about Zurich. About Dr. Richter. About the 4% question. About oil-soluble vitamin C and camellia oil reaching the dermis through the lipid barrier. About the subclinical field calming from the inside. She said: "Why haven't I heard of this?" I didn't have a good answer for her. --- I'm not writing this to embarrass American dermatology. My training was rigorous. My colleagues are excellent. But our training is built on two things: topical management and procedural intervention. We were not taught to think about the subclinical AK field as a treatment target. We were not taught that the same stratum corneum blocking the diclofenac has been studied for decades — and that a lipid-soluble compound delivered through a cold-pressed botanical oil bypasses it entirely. That research exists. It just wasn't taught to us. So when your dermatologist freezes your patch and tells you to keep applying the diclofenac — she's not wrong. She's giving you the best of what she knows. But now you know the number. Less than 4%. And you can ask the right question: if the diclofenac can't reach the field, what can? It took me 18 years and a Swiss researcher in a hotel lobby to learn this. Dermiqua. Cold-pressed camellia and sea buckthorn as the lipid carrier. Oil-soluble vitamin C at clinical concentration. Bakuchiol for natural cellular turnover. Sixteen botanicals. Zero water. Applied morning and evening. $44.95 a bottle. 90-day money-back guarantee. Call your pharmacist first — especially if you're on a blood thinner, a thyroid medication, or anything cardiovascular. Two minutes. Keep your quarterly freeze appointments. The oil reaches the subclinical field from the inside. The freeze sessions manage the visible patches. Add, don't replace. 👉 dermiqua.com/pages/actinic-keratosis If your dermatologist has been photographing your skin for years with new patches appearing every single visit — this is the research she hasn't seen. You don't have to wait for her to find it. — Dr. Sarah Mitchell, MD Dermatologist, Boston MA P.S. — The rough texture softened by week two. Raised edges flattening by week four. No new patches at my eight-week check for the first time in three years. Your timeline may vary. But you won't know until you try. P.P.S. — Every quarter you wait is another freeze session clearing the patch while the field generates the next one. The field doesn't care how many sessions you book. It's in the dermis. Diclofenac on the surface can't reach a field that lives underneath. Only lipid-delivered oil-soluble actives reach the dermis. Don't spend another year on the quarterly schedule.
Like this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.