Sabrina Roger, MD Neuromuscular Specialist
 Facebook ad: “What No Neurologist Is Taught About MS”

Ran for 5 days, from August 20 to August 25, 2026, the last day Crush saw it.
Run by Sabrina Roger, MD Neuromuscular Specialist on Facebook. Crush is not the advertiser and does not verify its claims. See this ad in Meta's Ad Library(opens in a new tab)
Make your own version of this ad
Crush makes it, launches it in your own Meta ad account, scales the winners and pauses the losers.
About this ad
- Meta Ad Library ID
- 2720703901678492
- Platforms
- Facebook, Instagram and Messenger
- Relaunches
- 1
Ad text
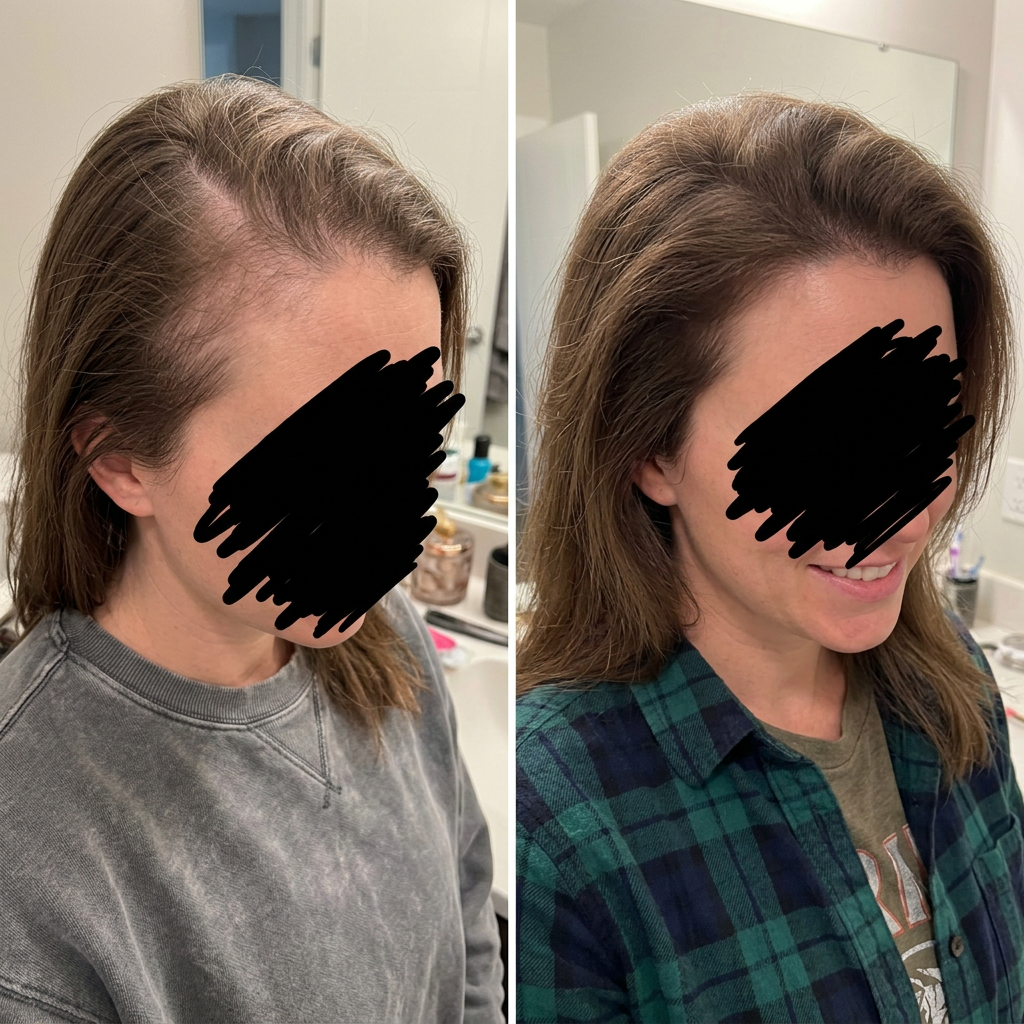
The best way to support your demyelinated nerves if you have MS is NOT more infusions, NOT more vitamin D, and definitely NOT waiting for the wheelchair. If your neurologist has mentioned worsening fatigue, declining function, or progression despite clean scans, you need to hear this. What they don't tell you is what comes next. I used to ask every patient who ended up in a wheelchair the same thing: "What did your MRIs look like before you lost the ability to walk?" After 2,000 patients and the same answer every single time, I stopped asking. It was always "no new lesions." Always clean scans. Always someone who'd stayed on their medication, taken their vitamin D, done physical therapy twice a week, and come back every six months. The people in wheelchairs aren't full of people who ignored their MS. They're full of people who trusted their “stable” scans. I'm telling you this now because I've had relapsing-remitting MS for 12 years. My MRIs always came back clean. My neurologist always said stable. Four years ago I started tripping on flat ground and losing words I'd used my entire career. And I refuse to end up in the chairs I've been prescribing for 21 years. I'm a neurologist. Twenty-one years in practice. I specialize in multiple sclerosis. Let me tell you what that actually looks like. The slow progression that no one prepares you for. First the foot starts dragging. Then you trip in your own hallway. Then you need a cane. Then a walker. Then you can't stand up without someone lifting you. Your neurologist runs an MRI. No new lesions. "You're stable." But your body is worse than it was six months ago, and nobody can tell you why. Then comes the catheter. Because the signals from your brain to your bladder degraded sometime around year eight, and nobody told you that was the disease too. Then the cognitive decline. You can't find the word. Then you can't follow the conversation. Then you can't remember what day of the week it is. Then comes the exhaustion. Not normal tiredness. The kind where you can barely lift your head off the pillow. And the hands. Buttons become impossible. Zippers. Jar lids. Your own handwriting changes until you can't read it. I've watched spouses learn to lift a grown adult from a bed to a wheelchair every morning. I've watched adult children rearrange their entire lives to become full-time caregivers. I've watched a 48-year-old woman sit across my desk and ask me if there was anything else I could do, because her dominant hand couldn't hold a pen. I've watched patients stop showing up to their appointments. I know what that means. One of my long-term patients, Linda, 57, eight years in my clinic, told me something I think about every day. She said: "I did everything they told me to do. Every infusion. Every appointment. And I still ended up here." Every. Single. One. So here's the trap most people are stuck in. Two paths. Both lead to the same place. Path one: Follow doctor's orders. Stay on your disease-modifying therapy. Take vitamin D every morning. Physical therapy twice a week. MRI every six months. Watch your body decline year after year while your scans keep coming back clean. Path two: Do nothing. The tripping gets worse. The fatigue gets heavier. The cognition gets slower. The hands get weaker. Most people with MS ignore the early progression because the MRI reads "stable." They blame the tripping on being clumsy. They blame the fatigue on poor sleep. They blame the mental fog on stress or age. It's none of those things. But there's a third path I was never taught in medical school or residency. And it's the only one I've ever seen actually reverse the decline. Four years ago I started noticing the same pattern in myself that I'd been documenting in my patients for two decades. The tripping. The fatigue. The words disappearing mid-sentence. My MRI was clean. My colleague said "stable." My timed walk: 9.2 seconds. It should be under 6. My right foot was dragging on the carpet every morning. My fatigue score was 54 out of 84. My processing speed had dropped to the 18th percentile. And here's the part that made my hands go cold. I'd been blaming every one of these on 21 years of 12-hour clinic days. The tripping on tired legs. The fatigue on the schedule. The word-finding problems on getting older. On paper, my MRI was clean. My colleague said "no new lesions, we'll monitor." But I've said those exact words to patients now sitting in my clinic in wheelchairs. I know what a clean scan looks like at the beginning. Because I've written the referrals for the wheelchairs of people whose scans were clean the entire time. I felt something I'd never felt in 21 years of neurology. Real, bone-deep terror. Not for my patients. For myself. Because I knew exactly where this ends. I've been on the other side of the desk for thousands of these conversations. So I stopped trusting the scan and started asking a different question. Not "how do I slow this down." But "why is my body losing function while my MRI is clean?" Here's what nobody explains to you. Every nerve in your body is wrapped in a coating called myelin. In MS, the immune system attacks that coating and strips it away. That's what the disease-modifying therapy is for. It reduces the immune attack. But here's what we aren't addressing: the damage already done. Every infusion, every injection, every pill your neurologist prescribes is designed to reduce the immune attack. Not one of them is designed to rebuild the myelin that's already been stripped. Your MRI measures new lesions. New areas of immune attack. When the MRI comes back clean, your neurologist says "stable." But "stable" on an MRI means no new attack. It does not mean the damage from previous attacks has been repaired. The myelin that was stripped is still stripped. The nerve it was protecting is still exposed. The signal traveling down that nerve is still degraded. That's why your foot still drags. That's why the fatigue is still there. That's why the words still won't come. Nothing you've been given repairs it. And it's not just your legs. The same stripped myelin that degrades the signal to your feet also degrades the signal to your hands. That's why buttons and zippers become difficult. It degrades the signal to your bladder. That's why you're up twice a night. It degrades the signal to your eyes. That's why your vision blurs when you're tired or warm. It disrupts the signals in your brain. That's why you can't find the word, can't follow the conversation, can't concentrate past noon. ALL of it traces back to stripped myelin that nobody is helping you rebuild. Your neurologist monitors the immune attack. The existing damage remains unrepaired. Now let me address what you're probably thinking. First: "What about my disease-modifying therapy?" Your DMT reduces the immune attack on myelin. It does not rebuild the myelin already stripped. The damage from previous attacks is still there. Your DMT is necessary. It is not sufficient. Second: "I take vitamin D every morning." Vitamin D supports your immune system. It does not provide the material, the energy, or the signal support that nerve repair requires. It's important. It doesn't address the nerve. Third: "What about physical therapy?" Physical therapy strengthens the muscles around your weakened nerves. It trains your body to compensate. But it does not rebuild the myelin on the nerve itself. You're working harder to overcome damage that's still there. All of these are part of the standard protocol. And all of them are important. But none of them address the actual repair. The myelin is still stripped. The nerve is still exposed. The signal is still degraded. And nobody has given you anything to change that. When I started reading the research, I found something that had been published for decades in Japan and Asia but barely mentioned in the United States. Neurotropic vitamins. B12, B1, and B6 in their active forms, at clinical therapeutic dosages, delivered in a way that gets them inside the nerve cell. In Japan, doctors prescribe neurotropic vitamins for nerve damage. They have for decades. Not as supplements. As medicine. The published research from that practice is extensive. Nothing about this is new. What's new is being able to get them in their active forms, at the right doses, with delivery that actually reaches the nerve cell. What I couldn't find was a large-scale American trial specifically on neurotropic vitamins for MS. The Japanese research was clear. The mechanism was established. But no one had run the American clinical trial to prove it. And nobody will. You can't patent a vitamin, and no pharmaceutical company funds a trial it can't profit from. So the research sits in foreign journals, and American neurologists never hear about it. I decided I wasn't going to wait for that to change. And every time I bring this up with someone who has MS, I get the look. Wide eyes. Raised eyebrows. That "You're talking about vitamins? Vitamins aren't medicine" face. I get it. Nobody believes a vitamin can do anything meaningful for a serious neurological disease. But the people I've told about this who come back 8 weeks later always come back with better numbers. Their timed walk improved. Their fatigue dropped. Their cognitive scores improved. Nothing in the language they'd been given allows for that. "Manage the progression." "Slow the decline." Every phrase their neurologist used was built around a disease that only moves one direction. Their faces have changed. The exhaustion is gone. They look like themselves again for the first time in years. And many of them went back to their neurologist and heard the words they never thought possible: "You're improving. Whatever you're doing, keep doing it." In 21 years of practicing neurology, not once did I come across this in my training. Not in medical school, not in residency, not in a single continuing education course. Not because anyone was hiding it. Because the pharmaceutical pipeline that trains neurologists is built around immune suppression. That's where the patent money is. That's where the drug reps go. That's what gets into the treatment guidelines. Nerve repair with neurotropic vitamins has been standard practice in Japan for decades. It never made it into American neurology training because there's no patent on a vitamin. No patent means no funding. No funding means no drug reps, no training updates, no guideline changes. That should make you angry. Not at your neurologist. At the structure that kept this from all of us, including the neurologist who spent 21 years prescribing everything except the one thing that addressed the actual damage. And I understood instantly why every neurotropic vitamin on every shelf had never worked for anyone. Three things wrong with all of them. Wrong form. The B12 in most supplements is cyanocobalamin. The form that actually works is methylcobalamin. The B1 in most supplements is thiamine HCl. The form that actually works is benfotiamine. The B6 in most supplements is pyridoxine HCl. The form that actually works is P-5-P. What's on the shelf is whatever is cheapest to produce, not what the research used. Wrong dose. A token amount of each, buried in filler. In the research, a standard low dose showed absolutely no difference in nerve recovery compared to a saline placebo. Zero. But when they used an ultra-high dose, nerve regeneration accelerated significantly. The dose on most supplement labels is the one that performed the same as salt water. Wrong delivery. A swallowed pill dissolves in your stomach, enters your bloodstream, and circulates. But your nerve cells are protected by a membrane. The vitamins in your blood have to cross that membrane to reach the inside of the cell, where myelin is actually rebuilt. Most of what you swallow never gets there. Your blood level goes up. Your doctor runs a test, and your B vitamin levels look normal on paper. But what's in your blood and what's inside your nerve cells are two different numbers. Your doctor only checks one. So even when your blood test says your B vitamins are normal, the actual amount inside the nerve cell where it's needed can still be almost nothing. I've watched patients bring B vitamin bottles to their appointments and ask me if they're helping. I look at the label. Cyanocobalamin, 100 micrograms, no B1, no B6. I know the answer before I finish reading. If you tried neurotropic vitamins before and nothing changed, you weren't wrong to try. The product was wrong. After I understood the mechanism and the delivery problem, I found something called Nuvel. All three neurotropic vitamins in their active forms. Methylcobalamin, benfotiamine, and P-5-P. Clinical therapeutic dosages, not the token amounts on every other label. Liposomal delivery, which means each vitamin is sealed inside a sphere made from the same material as your cell membranes. The sphere fuses with the nerve cell membrane and releases directly inside the cell, where myelin is actually rebuilt. No synthetic forms. No filler. Nothing to digest or absorb. One dose under the tongue daily. Third-party tested for purity and potency. That's the entire protocol. Neurotropic vitamins have been prescribed for nerve damage in Japan for decades. Doctors there use them the way American doctors use statins. One dose under the tongue before you leave the house. Five seconds. No measuring. No mixing. No taste. It's the one part of the morning that doesn't feel like managing a disease. Nothing about this is new. What's new is being able to get all three in their active forms, at the right dosages, with delivery that reaches the nerve cell. Here's what happened to me. Within two weeks the fatigue lifted. Not managed. Lifted. I worked a full shift without the usual collapse after lunch. The word-finding problems eased. I didn't trust any of it, but it was there. By week four the foot drag was gone. I walked my clinic hallway three mornings in a row to be sure. My MRI hadn't changed. My medication hadn't changed. I still check my timed walk every month. Not to see whether the vitamins are working. To see how far the repair has come. At day 60 I ran a full workup on myself. Timed walk: down from 9.2 seconds to 6.4. Fatigue score: dropped from 54 to 21. Processing speed: improved for the first time since my diagnosis. Same medication. Same MRI. Different nerves. But the thing I remember most isn't a test result. It's my own colleague looking at the workup, then looking at me, and saying: "You're improving. Whatever you're doing, keep doing it." And then walking into my clinic the next morning knowing, for the first time in four years, that I wasn't going to end up in one of my own chairs. I told Linda what I'd found. She looked at me with tears on her face and said: "Tell everyone. Don't let them end up like me." That's why I'm writing this. I don't have a clinical trial to hand you. What I have is a count. The patients I've told about this, and their families. Eighteen so far. One never started. Fourteen are still taking it. Eleven have been back for a follow-up since. Eight of them had improved timed walks and lower fatigue scores. Two showed no change and stopped, and I'd rather tell you that than not. You're in a window right now. The early progression phase, the "your MRI is clean but your body keeps getting worse" phase, is the ONLY phase where the trajectory can still change. Every patient in my clinic in a wheelchair was in that window once. Every one of them would give anything to go back to it. One side: nothing changes. The foot drags more. The fatigue gets worse. The cognition declines. The hands weaken. Year after year. Cane. Walker. Wheelchair. And one morning you're not reading about MS progression. You're being fitted for the chair. Full-time caregiver. Catheter. A life organized around what you can no longer do. The chair. The other side: One dose under the tongue. Sixty seconds. Done. Over the next few weeks the fatigue lifts. The foot stops dragging along the carpet. The words come back. The hands feel steady. And at your next neurology appointment, your doctor looks up from the chart and says something you haven't heard since your diagnosis: "You're improving. Whatever you're doing, keep doing it." The window stays open. The chair stays empty. If you go, take the 3-month option. Three bottles, which is ninety days of one dose under the tongue every morning. It does work out cheaper that way, though the price is not the reason. Ninety days is roughly what it takes to get a follow-up scheduled, which means at the end of it you're not deciding based on how you feel. You're deciding based on a number. [https://trynuvel.com/products/vitamin-b-complex-limposal](https://trynuvel.com/products/vitamin-b-complex-limposal) All three neurotropic vitamins in their active forms at clinical therapeutic dosages. Liposomal delivery. One dose under the tongue daily. Produced in small batches to keep the potency intact, which is the reason it goes out of stock as often as it does. When it's gone it's gone until the next batch is finished. Every order comes with a 90-day money-back guarantee, and the ninety days start the day the box arrives. Take it that whole time, and if you don't notice a difference, one email gets you every dollar back, and they don't ask for the empty bottles. Ninety days is long enough to get a follow-up scheduled. That's not an accident. The myelin is still stripped. The nerves are still exposed. But the window is still open. Don't let someone else tell your story with the words "I wish someone had told me sooner." I just did. If you're in the early progression phase right now, the clean scans with worsening function, the foot that drags, the fatigue that won't lift, the neurologist "monitoring" you, at least check out that page. It breaks down exactly how the neurotropic vitamins work and why the B vitamins you tried before didn't do anything. [https://trynuvel.com/products/vitamin-b-complex-limposal](https://trynuvel.com/products/vitamin-b-complex-limposal)
Where the ad sends people
trynuvel.com
What No Neurologist Is Taught About MS
Clinical-grade dosed formula proven in studies
Learn more: trynuvel.com(opens in a new tab)