
Active· since Jun 6, 2026
- 101
- days running
- 0
- relaunches
Ad copy
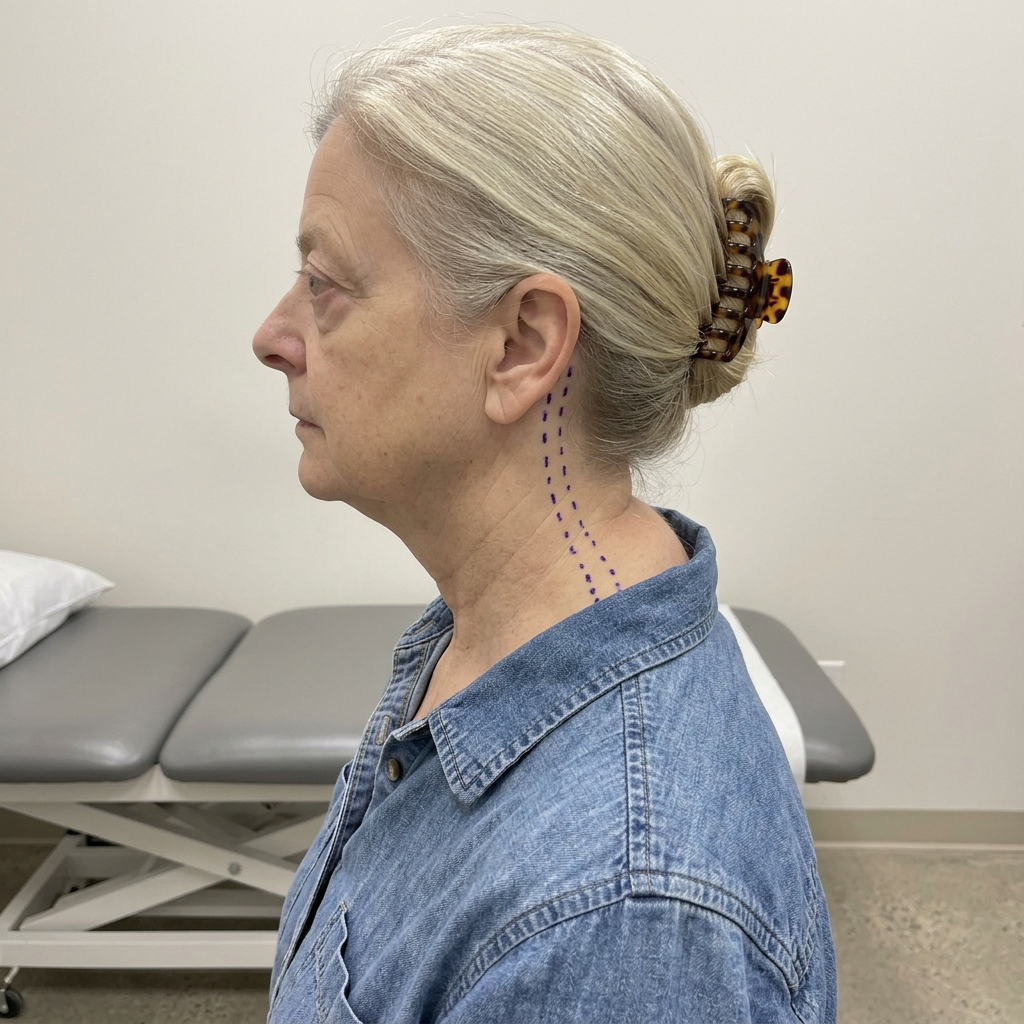
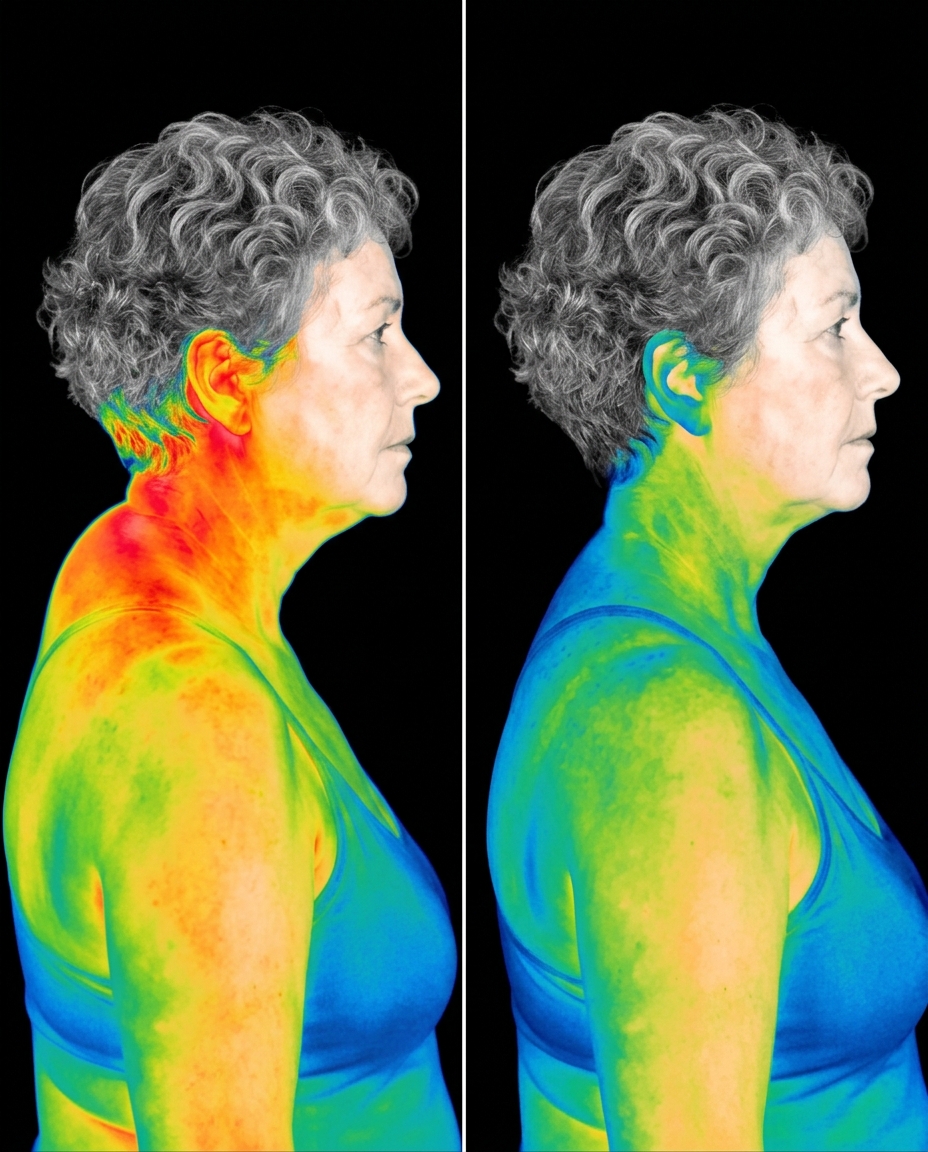
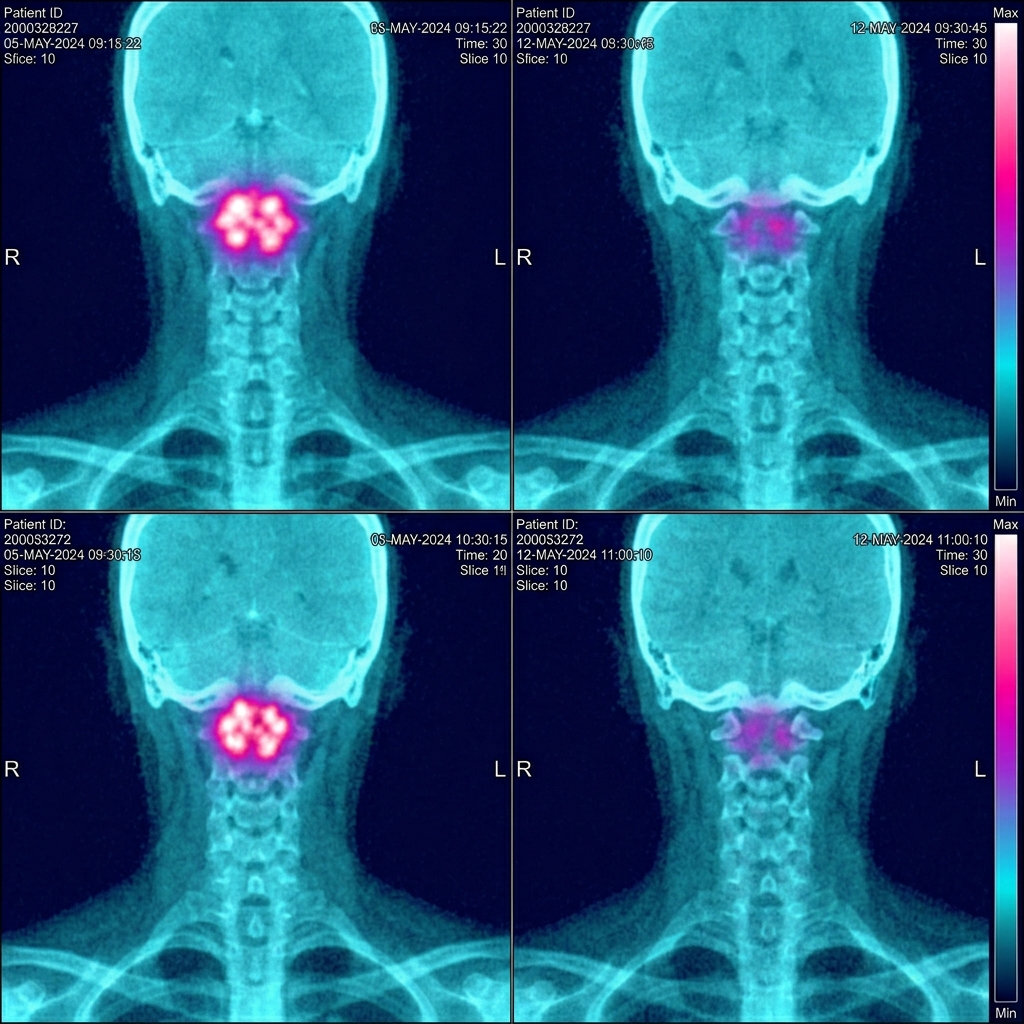
I've watched too many neck hump patients end up on indefinite management protocol to keep my mouth shut about this. If you've been told "just improve your posture" for a building neck hump, I need to tell you something your practitioner isn't telling you. My name is Linda Marsh. I've treated over 200 neck hump patients in 23 years as a manual therapist and cervical biomechanics specialist. And when a patient walks into my clinic with building tissue after their GP said "keep attending, we'll recheck in a year," I already know what their forward head translation will show 5 to 10 years later if nothing changes. Established fibrosis of the cervical structure. The same contracture dormancy driving their tissue progression is silently re-engaging their suboccipital muscles right now. And at 51, when my own forward head translation came back at 2.9cm and still climbing, I knew exactly what my practitioner was about to tell me. And exactly what she wasn't. Your building neck hump isn't a "watch and wait" problem. It's a proprioceptive receptor dormancy situation happening at the neuromuscular level. I've been treating neck hump progression for 23 years. I've seen hundreds of patients dismissed with "keep attending, adjust your posture habits, we'll recheck in a year." Most of them walked out, Googled the condition on the drive home, and stopped at the health shop on the way back. Cervical pillows. Posture braces. Foam rollers. One of those 15-feature cervical management devices. The tools every neck hump article on the internet eventually recommends. They used them for months. Some for years. Their tissue measurements barely moved. And what's worse, they thought they were doing something about the problem. Because primary care sees you once. Writes the dismissal. Sends you home. They don't see you 5 to 10 years later when you're sitting in my clinic with a forward head translation of 3.5cm and the words "established contracture" on your chart for the first time. But I do. Sandra's mother. Diagnosed with early cervical tissue progression at 49. Same advice. Attend sessions, recheck next year. Year after year. By 62 her tissue had built enough that they finally ordered a specialist referral. Established contracture. By 65 she was stepping back from every family gathering. She never returned to the front of a photograph. Her starting translation was 2.6cm. Almost exactly what mine was. Michael, 34. Came to me with a translation of 2.1cm. Normal posture history. What I'm ashamed to say I didn't recognize quickly enough was the early receptor dormancy already established despite his young age. I gave him the same "foam roller and postural awareness" protocol I'd been giving for years. He came back 18 months later with a translation of 3.1cm and tissue clearly visible at the cervicothoracic junction. Still addressable at that stage. But barely. He's the patient I think about at night. They had years. They just didn't know they had them. Because nobody had explained what their measurements were actually pointing at, or what was quietly building underneath those numbers while they waited for the next assessment. The assessments were telling them the truth from the first appointment. The tools they were using didn't change anything. They just made them feel like they were doing something. My symptoms told me I was fine. My measurements said otherwise. I felt fine. A little more aware of my profile in windows than I used to be. The morning calculation was taking longer but I told myself it was my schedule. Then a routine assessment caught it. My practitioner looked at the translation and said what she says to every patient. "Standard plan. Keep attending sessions, adjust your screen habits, recheck in six months." I knew it wouldn't work. That's not the point. I'm a manual therapist. I'd watched over 200 patients try exactly that and watched their tissue measurements stay exactly the same or continue climbing. So I ordered my own full cervical assessment. Forward head translation: 2.9cm. Tissue index: building. I asked for a detailed imaging of the suboccipital zone. Because I know what elevated tissue progression actually means. Early contracture establishment. Proprioceptive receptor dormancy at the neuromuscular level. The kind of re-engagement pattern that postural correction alone was never going to fix. My building tissue wasn't a "improve your posture" problem. It was my suboccipital receptor system being depleted of the one input it needed to fire the release signal. And another year of "monitoring" would have masked the only early warning sign I had. Here's what primary care doesn't tell you because they don't follow long-term cervical tissue outcomes. Your suboccipital contracture doesn't hurt. It doesn't swell painfully. It doesn't warn you with obvious symptoms. By the time your tissue is visibly building, the receptor dormancy has been established for years. By the time the tissue is obvious to others, the contracture has been re-engaging in silence for longer than you realize. You're not "just getting older" or "spending too much time on screens" or "carrying a little extra tension." Your suboccipital receptors are losing the input they need to fire the release signal. The same contracture re-engagement driving your tissue progression is quietly building the cervical structure underneath. Right now. Roughly 1 in 4 patients with established contracture progress to fixed structural changes within 10 years. By the time most neck hump patients are assessed properly, the dormancy is already at a level where standard management produces only temporary results. Your building tissue isn't embarrassing. It's your 5 to 10 year early warning system. And foam rollers silence that alarm while the contracture advances. So I tried what patients try. Postural habits. Screen time limits. Walking every morning. Improved my awareness a little, but translation stayed elevated. Tools. Cervical pillow. Foam roller at twice daily application. Posture brace for six hours daily. A traction device with 15 settings. 18 weeks of disciplined use. Assessment came back. Translation: 2.8cm. I lost 0.1cm. 18 weeks of doing exactly what I'd been telling 200 patients to do. Nothing was reversing the receptor dormancy driving the tissue. But I kept thinking about something that made no sense. The cervical structure is one of the few areas of the body whose receptor system can fully reactivate itself. Neck hump tissue CAN reduce. Even established contracture CAN reverse. The research proves it. So why wasn't mine reversing? And why hadn't my patients' tissue reversed either? October 8th. Late at night. I was reviewing 18 months of patient outcome data in my home office after a long clinic day. Couldn't sleep. My own translation had just come back at 2.8cm. I wasn't looking for anything specific. If I'm being honest, I was pretty desperate. I'd compiled outcomes for every patient I'd put on standard management for at least six months. Average translation change at 6 months. Average change at 12 months. Average change at 18 months. The numbers stopped me cold. Patients on standard management showed no statistically meaningful improvement in tissue index compared to patients who had stopped attending entirely. Eighteen months. 200+ patients. Almost zero meaningful difference. I sat there staring at a spreadsheet I should have run five years earlier. I was the therapist recommending standard management for 23 years. And I was wrong. Then I pulled up the small subset. The ones who'd done their homework. They'd quietly added something else on their own while I was still recommending foam rollers and posture correction. Direct suboccipital compression at C1-C2. Some had bought the cheap version after Googling. A basic pressure ball from an online health shop. Their tissue measurements barely moved either. Maybe 0.1cm, then they plateaued. That sent me down another rabbit hole. Standard pressure ball tools have a serious precision problem. The pressure is applied to the wrong address — too broad, too mobile, never staying at the exact C1-C2 suboccipital position that fires the receptor threshold. Studies put the effective input delivery at a fraction of what's required. So a standard pressure ball? The C1-C2 receptors actually receive maybe a quarter of the input threshold. That's a fraction of the clinical input dose, delivered at the wrong address. No wonder my own patients on standard tools saw nothing. But the small group who'd found exact-placement suboccipital tools with gravity-assisted sustained delivery? Those measurements told a different story. The precision placement delivers input to the exact C1-C2 address. The gravity assistance provides consistent uninterrupted force. The ten-minute hold meets the minimum threshold for the proprioceptive receptors to actually fire. Their tissue index was moving. Real movement. The kind of result I'd been hoping for in 23 years of practice but never actually seen from home tools. I'd been a manual therapist for 23 years. I'd studied cervical biomechanics my entire career. And I'd never properly understood why standard tools weren't doing the job. Management addresses the joint above the contracture and mobilises it. That's its job. But it can't give your C1-C2 receptors the sustained gravity-assisted input they need to fire the release signal independently. Cevera can. It delivers all three simultaneous inputs — exact C1-C2 placement, gravity-assisted sustained force, ten-minute minimum hold — straight to the receptor threshold. One temporarily mobilises what's restricted above. The other restores the receptor firing at the address itself. It's the same mechanism that cervical biomechanics researchers have been documenting for over a decade. They don't use broad thoracic pressure. They don't use short-duration manual force. They use exact suboccipital placement with gravity-assisted sustained delivery held for the minimum threshold duration. Same mechanism. Same address. Same threshold. The difference is duration. Acute management happens in sessions lasting minutes. Contracture dormancy takes years to establish. But the root mechanism is essentially identical. A 2024 cervical biomechanics study tested direct suboccipital compression head to head against standard adjustment and postural correction in 135 established contracture patients. Direct suboccipital compression was the only input that showed significant proprioceptive reactivation. The ONLY one. At midnight, I ordered Cevera. Two precision foam nodes at exact C1-C2 placement. Gravity-assisted delivery. Ten-minute protocol. The clinical threshold dose. Not the standard pressure ball from the health shop I'd watched patients buy and see nothing from. I didn't expect miracles. But for the first time in 23 years, the mechanism was sound. The tool arrived three days later. I started October 12th. Ten minutes before bed. Ten days in, I noticed the morning calculation wasn't there. I'd just gotten dressed after a twelve-hour clinic day and my head felt clear of the usual planning. First time in months. Three weeks in, my husband noticed before I told him. "You're not checking the mirror before we leave anymore," he said over breakfast. "What changed?" I hadn't told him I was using anything. "Different approach," I said. "Whatever you're doing, keep doing it." Eight weeks in, I got my translation rechecked and tissue index rechecked. When the numbers came up, I stared at the screen for almost one minute. Forward head translation: 1.6cm. Down from 2.9cm. Nearly 50% reduction in 8 weeks. Tissue index back in managed range. Suboccipital zone imaging: measurably reduced. The drop wasn't subtle. It was the kind of movement I'd been promising patients for 23 years and never actually seeing from home tools. My building tissue was reducing because my receptor dormancy was being reversed. I printed both assessments. Walked them down to the next clinical review meeting. Dr. Chen looked at the assessments. Looked at me. Looked back at the assessments. "Linda, what protocol did you put yourself on? Translation doesn't drop this fast on management alone." I explained the receptor dormancy. The three-input requirement. The gravity-assisted delivery. The ten-minute hold threshold versus the seconds of standard tool application. She studied the numbers for another minute. "And you said your tissue index improved too?" "Measurably. In eight weeks." She was quiet for a moment. "I need to start asking my neck hump patients about whether they've ever tried exact C1-C2 compression at threshold hold duration." I cancelled my specialist referral. But I started telling patients something primary care doesn't. I started with Sandra. 54. Three years of doing everything her practitioners told her. Eliminated all forward head positions. Attended three sessions weekly. Walked every morning. Lost weight. Used her foam roller twice daily for eight months. Tried a traction device her colleague found on a forum. Her translation when she started? 3.1cm. Her translation after three years of all of that? 2.9cm. 0.2cm. Three years. That was her reward for doing everything right. Sandra sat across from my desk and said, "I'm not going to be my mother. But nobody will tell me what to do besides adjusting my posture habits." So I told her what I'd just figured out. 10 weeks on the same protocol I'd put myself on. Cevera. Two foam nodes. Exact C1-C2 placement. Gravity-assisted delivery. Ten minutes before bed. Her translation at 10 weeks: 1.7cm. Down from 3.1cm. At her 8-week follow-up, her husband pulled me aside in the hallway. He said, "I don't know what you gave her, but she's been standing at the front of every photograph for the first time in years. Whatever you're doing, keep doing it." I'm not telling you this because I'm against standard management. Management has a place. It's a useful joint mobiliser. It might marginally slow some forms of acute restriction. But it doesn't fire the proprioceptive release signal. It doesn't address the neuromuscular mechanism causing neck hump progression. It doesn't move tissue measurements meaningfully in the patients who need it most. It temporarily mobilises the joint above the contracture while the receptor dormancy re-establishes below. Your building tissue is warning you. The same receptor dormancy driving your tissue progression is quietly re-engaging your contracture underneath. And you have two choices. Mobilise the joint above your contracture with standard management while the dormancy re-establishes below. Or fire the receptor threshold at the exact address and let your cervical structure reduce. I think about what I almost did. I almost wasted years the way my own patients had wasted theirs. I almost let my own translation climb on a management protocol I'd already proven didn't produce lasting change. I almost became the patient I see in my clinic 5 to 10 years later, wishing someone had told them their building tissue isn't the full picture. Because once your tissue has established at a fixed structural level, your options narrow. Once the structural changes are fixed, the tissue doesn't reverse easily. Once you need specialist-level intervention, your daily life changes permanently. Cevera has been in cervical biomechanics research for over a decade. It's about $50 for the tool. And it addresses the receptor dormancy before the structural changes become fixed. You don't get a second warning. Your building tissue is your first warning. The only warning you can still act on. Your building tissue is your check engine light. Foam rollers are electrical tape over the warning indicator. The contracture is still re-engaging. You just don't see the light anymore. But I see it every day in 200 patients' assessments. Every single one of them says the same thing. "I wish someone had told me building tissue was actually addressable." Someone just told you. You can't unhear it. The choice is yours. Fire your proprioceptive threshold at the exact address, and you potentially reverse your tissue before it becomes fixed structural change. Or mobilise the joint above your contracture with standard management, and risk everything underneath. I'm a manual therapist. I understand proprioceptive receptor mechanics at a clinical level. And I chose to address my own receptor dormancy before it progressed to fixed structural change. That's all I'm asking you to consider. Give your cervical structure a chance to reduce before you accept "monitoring" or commit to indefinite management protocol. Your building tissue is giving you years of advance warning. Use them. Eight weeks. That's all it took my forward head translation to drop from 2.9cm to 1.6cm and start reversing early tissue accumulation. Eight weeks of firing the receptor threshold instead of mobilising the joint above it. This is the tool I used: https://trycevera.com/pages/adv-womens-wellness-report P.S. The protocol I used is Cevera. Two precision foam nodes. Exact C1-C2 anatomical placement. Gravity-assisted sustained delivery through your own head weight. Ten-minute hold — the minimum threshold for proprioceptive receptor activation. Not the 3-minute standard tool application that most patients are using at the wrong address. If you've been told "just work on your posture" for a building neck hump, and you've been using foam rollers or posture braces, and you have any family history of cervical progression or have been building tissue for more than 12 months, get a baseline forward head translation measurement. Use Cevera at threshold hold duration for 8 to 12 weeks. Get follow-up assessment. Compare your measurements. Cevera backs the protocol with a 90-day money-back guarantee. If your measurements don't move on the 90-day protocol, you get every dollar back. No questions. The only issue is Cevera is a smaller company. They've been getting a lot of attention lately — probably because therapists and patients keep telling each other about it — and they sometimes can't keep up with demand. I'd suggest checking availability now. If you're calculating every morning. If you've tried standard management and it isn't holding. If your practitioner is suggesting escalated protocol and you're not ready to commit indefinitely. If you've tried other cervical tools and got nothing. I went from a 2.9cm translation to 1.6cm in eight weeks. I'm not following my patients' path of years wasted on the wrong approach. If there's even a chance this could work for you, it's worth trying. 👉 https://trycevera.com/pages/adv-womens-wellness-report
Like this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.