Inactive· since Sep 22, 2026
- 1
- days it ran
- 0
- relaunches
- 3,911
- EU reach
Ad copy
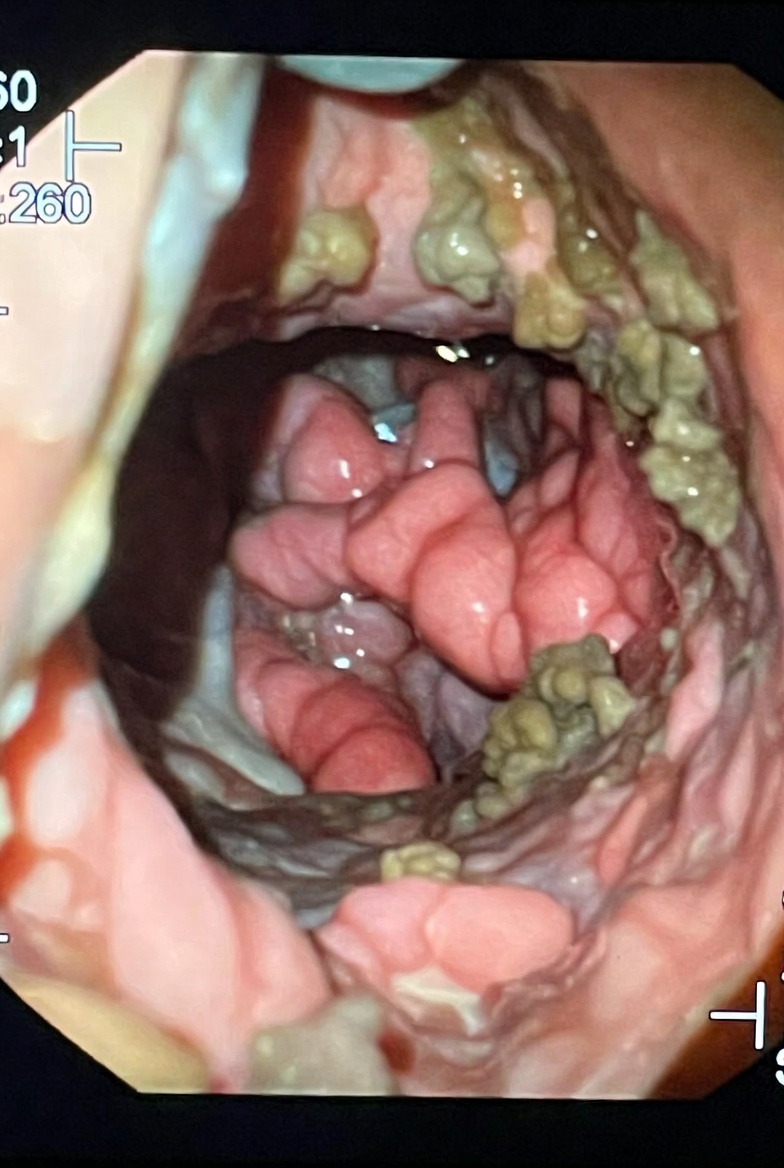
What do you think will happen when your body stops responding to MiraLAX one day? My body didn't stop responding to Miralax all at once. First, one capful stopped being enough. Then two. Then I added magnesium at night and Dulcolax on the bad weeks. Eventually there were no good weeks—only less-bad ones. Every failed dose made me wonder whether seven years of laxatives had slowly trained my colon not to answer at all. By 55, I believed I knew what came next. More laxatives. Then stronger ones. Then possibly surgery. A motility specialist told me that the future I had imagined was based on the wrong explanation. If your usual dose works less reliably than it used to, I need you to hear what she told me before another bad morning answers this question for you. My name is Diane. I'm 55 years old. I work in HR for a regional bank in central Connecticut. I've been married to my husband Tom for 30 years. From the outside, my life looks like the life I always wanted. But for the last seven years, the most important fact of my life has been the white bottle of Miralax on the second shelf of my bathroom cabinet. Before I tell you what the specialist found, I need to show you how one capful became seven years of waiting for my body to stop answering. It started seven years earlier. I turned 48 in the summer of 2018. My periods stopped that fall. A few months after that, I noticed I wasn't going to the bathroom every day anymore. Then every other day. Then twice a week. I went to my GP — a man who'd been my doctor since I was 28. He said, and I'm quoting him: "Try a capful of Miralax in your morning coffee. It's totally safe. Doesn't cause any issues. You can take it as long as you need to." I trusted him. I went home and started taking it. I was 48 years old. For about a year, it worked. A capful in the morning, by ten o'clock my body would do what it was supposed to do, and I'd forget about it for the rest of the day. Then it stopped being enough. I went to two capfuls. Then I added magnesium powder at night, mixed in water. Then on the bad weeks I started taking Dulcolax. Then there weren't really good weeks anymore, just less-bad ones. By the summer I turned 54, I was on Miralax in the morning, magnesium at night, and Dulcolax three or four times a week. I was also passing gas all day, every day. Some afternoons it hurt badly enough to fold me in half. I stopped sitting through long meetings without knowing where the bathroom was. I started feeling a hard pressure low in my abdomen that never seemed to move. Sometimes what finally came out was a handful of dry pellets. Sometimes it was a hard packed clump that dropped into the bowl with a clunk. And even after straining, I never felt empty. I tried adding more fiber because that was what everyone told me to do. It only made the gas worse. I drank more water. The pressure stayed there. The more I tried to fix the output, the more my life became organized around whether the next dose would work. That summer was when the fear started. Up until then I'd been telling myself a story. The story was: this is a problem I'm managing, like blood pressure, like cholesterol. I take my pills, my body works, life continues. That story stopped being available to me in July of last year, and I want to tell you exactly when it broke. I was sitting up in bed at 2 AM. Tom was asleep next to me. I had taken my normal evening doses six hours earlier. Nothing had happened. I had been bloated all day. My stomach felt hard and full low on the left side. I'd taken an extra Dulcolax at 11 PM out of panic. Still nothing. I was sitting there in the dark on my phone, and I had just Googled the words "cathartic colon." If you don't know what cathartic colon is, don't Google it tonight. Read the rest of this first. Because what I read at 2 AM that night was the beginning of the worst twelve months of my life. Cathartic colon, in the way it gets described online, in old medical literature, on the threads I'd read, is what happens when your colon has been chemically pushed for so long that it stops answering. The muscles stop contracting. The colon goes dead. And the only treatment, the women writing online said, was surgery. A partial colectomy. They take the dead section out and reconnect what's left. Some women in those threads had had this done at 60. Some at 55. Some at 48. I sat in bed and read every single thread I could find, and then the page after that, and then the page after that. I read women describing recoveries. I read women describing complications. I read one woman — and I will not forget this for the rest of my life — describing what it's like to live with a permanent colostomy bag at 52. I closed my phone at 4:30 AM. I did not sleep. That night didn't really leave me for the next twelve months. Every dose I took, I thought about it. Every time the dose didn't work, I thought about it harder. I started checking my abdomen in the mirror obsessively, looking for distortion, looking for hardness, looking for the shape of something that had stopped working. Once, that fall, I tried to stop. Cold turkey. I made it three days before I had gained six pounds of water weight and could not button a single pair of pants I owned. I went back on the Miralax. I never tried again. I made an appointment with my GP, the one who'd put me on Miralax seven years before. I told him I was scared I'd damaged myself. He looked at my chart. He said: "Your bloodwork looks fine. You had a colonoscopy at 50, that was clean. You're okay. Just keep doing what you're doing. We don't really have great options for chronic constipation." I drove home from that appointment crying. Not because he'd been mean. Because he hadn't. He'd been kind, and he'd told me there was nothing else. He'd basically told me this was just my life now. The Miralax. The bottle in the cabinet. All of it. Forever. I want to skip ahead now, to the day everything changed. It was a Wednesday in May. I had taken my full evening stack Monday night — magnesium powder, two Dulcolax — and woken up Tuesday morning to nothing. I'd added another capful of Miralax Tuesday morning. Nothing. By Tuesday evening I was so bloated I couldn't button my work pants. The gas was trapped and painful. I took an extra Dulcolax Tuesday night. Nothing. Wednesday morning I woke up at 5:30 and lay in bed with my hand on my stomach, and I could feel it. It was hard. It was distended. It felt like a packed lump low on the left side. It had not moved in four days despite everything I had thrown at it. And the thought that came into my head, lying there in the dark, was: this is it. This is the day my body finally stopped responding. I have killed it. I told Tom I needed to go to urgent care. He offered to come with me. I told him no — I didn't want him to see what was about to happen. I drove myself to the urgent care on Farmington Avenue. I sat in the waiting room for an hour and a half. When the doctor saw me — a woman maybe in her forties, in scrubs, tired — I told her I thought I had an obstruction. I told her about the seven years. I told her about the doses. I told her about the gas, the dry stool, the pressure, and the fact that I never felt empty. I told her I had not had a bowel movement in four days despite every laxative I owned. She sent me for an abdominal X-ray. I waited another forty minutes. She came back into the exam room with the result on a tablet. She turned the screen toward me. She said, "There's no acute obstruction. You have a significant amount of stool throughout your colon, but no obstruction. Your colon is just being sluggish today. I'd recommend a stronger dose tonight. Maybe try an enema if it's not moving by tomorrow." I sat on the exam table and stared at her. I had been preparing, for an hour and a half in the waiting room, for her to tell me my colon was dead. I had been preparing for surgery. I had been preparing for the worst. What she'd told me was almost worse. She had told me nothing was wrong. That what I was experiencing — the bloat, the gas, the hard pressure, the not-going, the four days of nothing — was just a normal Wednesday for me now. That I should take more. I drove from the urgent care to an empty parking lot and sat in my car for forty-five minutes and cried. This is what I want every woman reading this to understand. I was not crying because I was sick. I was crying because no one in medicine was going to help me. I had been to my GP, who told me I was fine. I had been to an urgent care, who told me to take more. I had had a colonoscopy at 50 that came back clean. I had had bloodwork that came back clean. The system had nothing else to offer me. And I was certain, in a way I'd been certain for almost a year, that I had broken something inside me that was not going to come back, and I was going to have to live with it. I went home. I told Tom what had happened. He sat down on the couch next to me and held my hand and said: "There has to be a doctor somewhere who treats this. There has to be a specialist. Let's find one." So we started searching. What I learned in the days that followed is that most gastroenterologists treat structural problems, Crohn's disease, ulcerative colitis, polyps, cancer screening, hemorrhoids. There's a smaller subspecialty within gastroenterology called motility. Motility doctors focus on how the gut moves, rather than what it looks like. Most major university hospitals have one or two motility specialists on staff. Most regional hospitals have none. The one Tom found was Dr. Karen Mitchell. She had completed her gastroenterology training at the Cleveland Clinic in the 1990s and stayed there for the first decade of her career doing research on the bacterial ecology of the human colon. She moved to Connecticut in 2012 to build the motility program at the university hospital here. Her clinic was eight weeks out for new patients. She did not advertise. She took referrals only from primary care physicians or other gastroenterologists. Tom got my GP to write the referral letter the day after I came home from urgent care. The reason we found her at all was that a woman in Tom's office had a sister-in-law who'd been her patient three years earlier and would not stop talking about her. That is how rare this kind of doctor is. The eight weeks of waiting were ordinary — I did what I had been doing for seven years. I want to take you to the morning of the appointment. It was a Tuesday in July. I had myself fully prepared for what Dr. Mitchell was going to tell me. I had Googled "cathartic colon" probably a hundred more times in the eight-week wait. I was convinced she was going to look at my chart, run a test, and tell me my colon was structurally damaged. That maybe I'd need surgery in five years. That I had done this to myself and now I had to live with it. I went in expecting the death sentence I had been preparing for since the previous July. The waiting room had a poster about colon cancer awareness on one wall and a fake plant in the corner. When she walked into the exam room, the first thing I noticed was that she was about my age. Late fifties. Short gray hair. Wire-rimmed glasses. She sat down on the rolling stool, opened her laptop, and read my chart in silence for almost two full minutes. Then she looked up at me and asked: "When was the last time you had a bowel movement without taking anything?" I sat there trying to count back. I couldn't. The honest answer was I genuinely could not remember the last time my body had done that on its own. She watched me try to count, and then she said, very quietly: "It's okay. I want you to know that I see this pattern every single week, multiple times a week. Women your age. Women younger than you. You are not unusual. And you are not broken in the way you think you are." I started crying right there in the exam room. I had spent a year preparing for the opposite sentence. She handed me a tissue and she waited. Then she said: "I want to run two tests on you, one to confirm severity and one to check the pattern I suspect. But I want you to understand something before I do. I have already heard enough from you to know the pattern we are looking at. The tests will show me how severe the slowing is and whether methane is involved. They will tell me which parts of the pattern we can confirm." She ordered a sitz marker test. You swallow a capsule containing 24 small radio-opaque markers, and they take X-rays at 24, 48, and 72 hours to see how many have moved through your system. She also ordered a methane breath test because the gas, the hard packed stool, the severe slow transit, and the way my symptoms had worsened after menopause pointed to a methane-producing overgrowth that the marker test could not measure. The breath test came back methane-positive. She said that result supported methane involvement, while the sitz study would show what the movement problem was doing. "Come back in three weeks. We'll go over the result." Three weeks later I was back. She came in with a folder and sat down and said, "I want to walk you through what's been happening to you. And I'm going to take some time with this. Because nobody has probably explained it to you this way before." Here is what she told me. I'm going to do my best to reproduce it the way she said it, because I have replayed this conversation in my head a hundred times since. She started by drawing a circle on a notepad. "This is your colon." She drew a wavy line across the inside of the circle. "Inside your colon, you have an entire ecosystem. Trillions of bacteria, fungi, and archaea. Most of them are beneficial. They digest your food, regulate your immune system, produce vitamins, and help tell your colon muscles when to contract." She paused. "Your whole life, the beneficial bacteria have kept the inside of your gut slightly sour. Slightly acidic. On purpose." She drew a thicker line around the inside of the circle. "That acidity is not incidental chemistry. It is a protective wall. It helps keep the wrong organisms from taking over." I thought about the way my periods had stopped and the constipation had followed. She said, "When you went through menopause and your estrogen fell, two things happened at the same time. Your gut slowed down. And the beneficial bacteria that maintained that acidic environment began to thin out." I asked her if that was why the gas had become so constant. She nodded, but told me the gas was only the part I could notice. "When the acidic wall weakens, a methane-producing organism called Methanobrevibacter can expand in an environment that used to hold it in check. It produces methane around the clock." She looked at me. "Methane is not just the gas you have been ashamed of. It is part of what is stopping the movement." I had spent years thinking the smell was embarrassing evidence that my body was dirty or old. She was telling me it was part of the mechanism. Then she said the sentence I had needed someone to say for seven years. "Your colon was never lazy. It was being chemically held still." She made a fist and held it closed. "The muscle is not necessarily dead. It is being chemically frozen by an invisible gas. The contractions are being held back." I asked her to explain what that looked like inside me. "Think of your colon as a slow, turning drum," she said. "When it turns, stool moves through while it is still soft." "But methane freezes the drum." "The stool stops moving and just sits there." "Your colon is built to absorb water from stool as it passes through." "But when the drum stops turning, the stool stays there far longer than it should." "So your colon keeps pulling water out of that same trapped stool." "So the stool gets drier." "And drier." "What should have passed easily dries out and packs down into cement." "That's your rabbit pellets." I thought about the pellets. The hard clumps. The lump I could feel. The way I stood up from the toilet feeling exactly as full as when I sat down. She said, "That is your dry stool. That is the low abdominal pressure. That is why you never feel empty." I told her more fiber had made the gas worse. She said, "More fiber can add bulk behind an existing motility jam. It gives the frozen drum more material to move, without removing the freeze." I told her I had been drinking more water. She said, "More water cannot simply reverse material that has already dried and packed down like cement." She pulled the folder closer. "Your sitz marker test showed you retained 21 of 24 markers at 72 hours. That puts you in the severe slow-transit category. The methane-positive breath result supports the separate methane involvement. The two tests are telling us different parts of the same story." Hearing 21 of 24 made me feel sick. But hearing that the marker test did not measure methane made me trust her more. She was not pretending one test proved everything. Then she explained the part that made my years of dose-stacking make sense. "Every time you've taken a stimulant laxative — your Dulcolax — it can force a contraction and give you an event. But it does not remove the methane environment that is holding the drum still." She paused. "Every time you've taken Miralax, you've drawn water into the colon and forced material through. You may get through today. But the chemical brake can still be there tomorrow." She tapped the bottle name in my chart. "And every round of magnesium you've taken can create another temporary push without rebuilding the environment. That is why you keep reaching for the bottle again the next morning." I asked her what the cycle was doing over time. She said, "Every laxative forced one more flush and left the door open behind it." The phrase made me angry because it explained why I had been working so hard and getting nowhere. She continued. "You force temporary output. The methane-producing environment remains. The movement slows again. The material sits longer and dries further. Then you need a bigger dose or another product to force the next event." I asked her whether that meant I was headed for an obstruction. She said, "The cycle can end in obstipation, when nothing passes, not stool and not even gas. That can progress to obstruction. But your urgent-care X-ray did not show an acute obstruction that day. It showed a colon full of retained material and no emergency blockage." She looked directly at me. "I am explaining the endpoint this cycle can reach. I am not saying you already had it." I sat there with my hands in my lap. For the first time, the clean colonoscopy and the hard symptoms could exist in the same story. The walls could look normal while movement was being chemically held back. I asked her why no one else had seen it. She gave me a tired smile. "Because mainstream gastroenterology is trained to look first at structure. Your colonoscopy looked at the walls, and the walls were normal. It did not explain whether the rhythm was moving properly or whether methane was contributing to the slow transit. Most doctors were never trained to think about chronic constipation as a movement problem connected to a changed bacterial environment." Then she said the thing I want every woman reading this to hear. I want you to read it twice if you have to. She said: "What you have is real. It is diagnosable. And it is reversible. You have not destroyed your colon. Your colon was never lazy. It was being chemically held still." I am not going to pretend I didn't sob. I had spent a year in a private hell of believing I had broken something inside my body that couldn't be repaired. A year of 2 AM Googling. A year of looking at my abdomen in the mirror and seeing a body I had ruined. A year of preparing for surgery. And in one sentence, a doctor I had met only twice had taken all of it back. Then she said: "But I have to tell you the rest of it. Because the part you haven't heard yet is the most important." She said: "Three things have to happen. And they have to work as one sequence." She held up one finger. "First, you have to quiet the methane. You do that by feeding the beneficial bacteria again, until they can rebuild the environment that holds the methane producers in check. As methane pressure falls, the chemical brake weakens. The muscle has an opportunity to thaw. Then the contractions can come back on their own." Second finger. "Second, you have to rebuild the protective acidic wall. The beneficial populations you lost, including Bifidobacteria and Faecalibacterium prausnitzii, need to be fed. They consume particular plant pigments. As they return, they produce a short-chain fatty acid called butyrate." She paused so I could follow. "Butyrate's first job here is helping restore the acidic environment. An acidic environment is less hospitable to methane dominance and helps reduce the chance of the same overgrowth returning." Third finger. "Third, that same butyrate does another job. It is a primary fuel used by the cells lining your colon. For years, that lining has not had enough of the fuel it needs. Feed it again, and the wall has energy to support normal function. That is different from forcing one bowel movement this morning." She looked at me and said the sentence that stayed in my head. "Quiet the methane. Rebuild the wall. Wake the muscle." She said the three parts had to be done together. Not another stimulant event. Not another scoop that only moved water. Not a probiotic capsule thrown onto ground that had not been fed. The bacteria had to be fed. The wall had to be rebuilt. The muscle had to be given a chance to move without being forced. Then she explained the food category that could supply the relevant dark plant pigments. She said, "There is one everyday food category I want you to understand. Hibiscus." But she immediately held up her hand. "Not hibiscus flavor. Not a red tea bag. Not pale powder in a cheap blend." She said the active argument was about anthocyanins, the deep plant pigments that give certain flowers their dark red and purple color. "The dark ruby color is not decoration. It is the food the good bacteria have been missing." She must have seen the doubt on my face, because she smiled. She said: "I know how this sounds. Believe me, I know how this sounds. I'm a board-certified gastroenterologist. I spent twenty years prescribing prokinetics. I would have laughed at this in 2012." She said the difference was the literature. She named research on methane and slow transit, hibiscus anthocyanins, microbiome diversity, beneficial bacteria, and butyrate production. I did not understand every study she mentioned. I am not going to pretend I did. What I understood was the part I could not stop repeating in my head. Every scoop and every pill had been helping me force today's load. None of them had rebuilt the environment that was supposed to make tomorrow's rhythm work. Seven years of forcing today. Seven years of never rebuilding tomorrow. She said anthocyanins were fragile. Heat, air, age, rough processing, crushing, blending, and tea dust could weaken the pigment before I ever drank it. "You want whole flowers because the intact form better protects the pigment. Careful drying matters because the color has to stay deep. High-altitude growing and hand-picking matter because the flower has to be selected and handled in a way that preserves the payload." She said the pigment had to survive preparation and digestion long enough to reach the lower colon where the bacteria lived. That was the part I kept replaying. It was not enough for a cup to look red. The form had to carry the pigment through the process. She said a food-based ritual was also gentler for someone whose mornings had been made fearful by years of stimulant urgency. I asked her what kind I should buy. She said she did not want me to think in terms of a brand. She wanted me to look for true whole hibiscus flowers. Deep ruby pigment. Careful growing. Careful picking. Careful drying. An intact form. One deep ruby serving in the morning and one after dinner. And no abrupt withdrawal from my current regimen. I asked her if I had to stop the Miralax. This is the part I want every woman reading this to underline. Because I know this fear. I know it because the thought of stopping cold turkey was, in some ways, more terrifying than anything she had said up to this point. I had tried the previous fall, and I had made it three days. She said: "You keep taking your MiraLAX. We do not change anything in your current protocol on day one." She said I should continue everything as normal at first and pay attention to response. As my own motility returned, I could reduce the other products gradually. We would not taper on a rigid schedule. We would taper on observed function. I started crying again. I had not realized, until that moment, how badly I needed somebody to tell me I did not have to choose between the laxatives I feared and the terror of withdrawing from them. That I could keep my safety net. That my body could be the one to tell me when to put it down. She walked me out. It was a sunny Tuesday in July. I sat in my car in the parking garage for almost forty minutes before I drove home. I had walked into that office with a year of fear sitting in my chest. I walked out with a different sentence in my head than the one I'd been carrying since the previous July. But I want to be honest about something I did wrong first. Because this is the part that almost made me think the whole thing was nonsense. The next morning, I went to the grocery store. The tea aisle had three kinds of hibiscus. A red box with a flower on it. A blended herbal tea. The store brand. I bought the familiar red box because it was $3.79 and it said hibiscus on the front. I started drinking it the way she told me to: two cups a day. One in the morning. One after dinner. Week one on the grocery tea: still taking my usual morning Miralax. Still sitting there too long. Still passing gas by mid-morning. Still no morning rhythm. Week three on the grocery tea: the same cramping. The same hard pressure low on my left side. The same dry, incomplete feeling after I went. The same careful calculations before dinner out with Tom. Something had to be wrong. Six weeks later, I was sitting at the kitchen table with the empty box beside me. I turned it over and read the ingredients again. Hibiscus. Rosehips. Lemongrass. Peppermint. Natural flavor. That was the part I couldn't ignore. I had bought a tea that happened to contain hibiscus. I had not bought the thing Dr. Mitchell had actually described. She had described whole flowers carrying deep pigment. I had bought a blend in a paper tea bag. That night, I pulled up the notes from her office again. I wanted to know exactly what kind of hibiscus she had told me to look for. That's when I saw the words I had skipped past. Whole flower. Deep pigment. Carefully grown. Hand-picked. Carefully dried. The anthocyanins were the point. Not flavor. Not a pretty red tea bag. Not red water. The intact flowers had to carry enough of the dark pigment to survive the trip to the lower colon. Then I understood the delivery problem. Most grocery-store hibiscus was broken petals and dust. Blended with other herbs. Crushed into tea bags and left on shelves because it made a cheap, red cup of tea. Heat, air, and time had more opportunity to weaken what was left. It wasn't that hibiscus didn't work. It was that I had bought the version with none of the qualities Dr. Mitchell had told me to look for. High-altitude growing mattered because the flowers had to develop strong protective pigment. Hand-picking mattered because the deepest-red flowers could be chosen at their peak instead of stripped for volume. Careful drying mattered because the color had to stay deep. The form was the difference I had missed when I grabbed the $3.79 box. I searched for an organic whole-flower hibiscus tea that matched every one of those specifications. That is how I found PiPi Tea. Organic whole hibiscus flowers. High-altitude grown. Hand-picked. Deep ruby flowers, not dusty fragments swept into a tea bag. I read the reviews. Women describing exactly what I was going through. Years of Miralax that never restored their rhythm. Then, within weeks, mornings when they could finally go on their own. I ordered a bag at 3:15 AM. When it arrived, I started immediately. I want to tell you what happened next, but I want to be honest with you about the first three weeks. Because this is the part where people give up. Week one on PiPi Tea: nothing dramatic. I felt about the same. I drank two servings of PiPi Tea every day — one in the morning, one after dinner. I kept the Miralax. I waited. The only thing I noticed in week one was that my bathroom trips were maybe — maybe — slightly less effortful. The gas did not disappear overnight. Week two: I woke up one morning and my stomach was flat. Not bikini-flat. Normal-flat. The way mine used to be when I was 47. I stood in front of the mirror and stared at it. Then I did something I hadn't done in seven years. I went downstairs, made coffee, and didn't add the Miralax to it. I just wanted to see what would happen. At 9:15 AM, on my own, with no chemical assistance, I had a real bowel movement. It was softer. It felt more complete. I sat there afterwards and cried for ten minutes. I texted Tom. I just said, "I went on my own." He wrote back, "Honey." That's the whole text. Just: honey. Week three: I had three unassisted bowel movements that week. The gas was noticeably down by mid-afternoon. The pressure was not as hard. I cut the Miralax to half a capful in the morning, just as a hedge. Week four: I started forgetting my magnesium. By the time I'd remember, it was 10 PM and I'd think, well, let's see what happens if I don't take it. By the end of that week, I had skipped it once. The next morning, on my own, I went. Around week five something happened that I didn't connect to any of this until later. I head up HR at the bank. For the last three or four years I'd been quiet in meetings. I'd told myself I was just letting the younger people lead. The truth was I'd stopped being able to follow conversations in real time. There was always a sort of fog around my thinking. A delay. A feeling like I was watching everyone else from behind a window. I'd been foggy for so long I'd assumed that was just my brain at 55. That Tuesday, in a quarterly review, somebody made a point I disagreed with. I argued my position for maybe ninety seconds. I made the room laugh in the middle of it. When I sat back down I realized I hadn't done that in years. I hadn't even known I'd stopped. Week six: I had not taken Miralax in nine days. I had not taken magnesium in eleven days. I had not taken Dulcolax in over a month. Week eight: Tom said the thing I will not forget for the rest of my life. We were getting ready for bed. I was brushing my teeth and he was sitting on the edge of the bed pulling off his socks. He looked up at me and said: "You're here." I said, "What?" He said: "I don't know how to explain it. You feel here. Like you actually showed up. I didn't realize you'd been gone." I am 55 years old. I have been married to that man for 30 years. And until that night, I did not understand that he had spent the last seven years of our marriage living next to a woman who wasn't fully in the room. Month six: I went back to see Dr. Mitchell for a follow-up sitz marker. I retained 4 of 24 markers at 72 hours. Down from 21. She showed me the comparison on her laptop and shook her head slowly and said, "This is what your colon looks like when you let it work." If you've stayed with me through all of this, you're probably the woman I was writing this for. There are a few things I want to say to you specifically. If you have spent a single night in the last year Googling "cathartic colon" or "laxative dependence" or "is my colon permanently damaged," I want you to know that there is a very good chance the answer is no. There is a very good chance what you have is what I had. A colon that is still intact, but has been chemically held still by methane after the protective environment weakened. The thing that helped me, PiPi Tea's whole hibiscus flowers, is not a miracle pill. It was the first thing I'd tried that was aimed at the environment and the rhythm instead of the emergency. It is a simple daily tea made from organic whole hibiscus flowers, high-altitude grown, hand-picked, and naturally deep ruby from the anthocyanins Dr. Mitchell told me to look for. Not the grocery-store red box I bought first. That box said hibiscus, but it was blended tea-bag hibiscus, not whole flowers. I am 55 years old. I work in HR. I don't trust easy answers and I don't trust supplements. I trusted this one because my motility specialist sat in a chair and walked me through the mechanism, and I went home and verified what I could. PiPi Tea offers a 90-day money-back guarantee. If it isn't right for you, send it back within 90 days for your money back. I am not affiliated with them in any way other than as a customer. I'm writing this because I read essays like this one when I was at my lowest, and they kept me alive in a quiet way. I want to be one of them for somebody else. You can keep your Miralax for now. You don't have to stop anything. You just have to start one thing. And see what your body does over the next 90 days. You can look into PiPi Tea here: https://shop.pipitea.com/hbt/kd/c/sp-nm Seven years ago a doctor told me I could take Miralax as long as I needed to. I lost seven years to that one sentence. A year ago I told myself, every night at 2 AM, that I had destroyed my colon and would have to live with the consequences forever. I lost a year of my life to that one belief. Both of those things turned out to be wrong. Yours might be wrong too. Click below to try PiPi Tea. https://shop.pipitea.com/hbt/kd/c/sp-nm
Natural Relief in Weeks
LEARN MORELike this ad? Make it yours.
Crush rebuilds this exact creative around your product — your brand, your colors, your offer — in about a minute.